Evaluating Renal Resistive Index Responsiveness to MAP Targets in Early Septic Shock: Clinical Implications and Physiologic Insights
Highlight
Guidelines currently recommend a mean arterial pressure (MAP) ≥65 mm Hg in septic shock, but individualized MAP targets are advocated to optimize renal outcomes.
The renal resistive index (RRI), assessed via Doppler ultrasound, reflects renal vascular resistance and is linked with acute kidney injury risk.
This prospective randomized study tested whether early RRI responsiveness to transient MAP elevation could identify patients who benefit from higher MAP targets regarding renal function.
Patients exhibiting a decrease in RRI with increased MAP did not experience improved kidney outcomes at higher MAP targets, whereas nonresponders showed increased urine output with high MAP, suggesting distinct hemodynamic-renal coupling phenotypes.
Study Background
Septic shock remains a critical cause of acute kidney injury (AKI) and associated mortality in intensive care units (ICUs). Current international guidelines recommend maintaining MAP above 65 mm Hg to ensure adequate organ perfusion. However, the optimal MAP threshold may vary by patient, influenced by individual cardiovascular and renal autoregulatory responses. Excessive vasopressor use aimed at raising MAP may induce adverse effects without renal benefit, highlighting the urgent need for bedside tools to individualize hemodynamic targets.
The renal resistive index (RRI), derived from Doppler ultrasound waveforms of intrarenal arteries, quantifies renal arterial resistance and has emerged as a noninvasive marker correlating with AKI and renal outcomes in critically ill patients. Prior observational data suggest that increasing MAP can reduce RRI, possibly reflecting improved renal perfusion pressure and vasodilation. Yet, it remains unclear if RRI changes under transient MAP challenges can guide therapeutic MAP targets to prevent AKI.
Study Design
This was a prospective, randomized physiological study conducted in a university hospital medical ICU. Participants were adult patients with early septic shock, defined by norepinephrine requirements ≥0.05 µg/kg/min within nine hours of initiation, some with lactate >2 mmol/L, excluding those with chronic kidney disease or immediate renal replacement therapy needs.
All patients underwent a standardized 2-hour MAP test: first maintaining MAP 65–70 mm Hg, then increasing to 80–85 mm Hg, with repeated RRI measurements. Patients were categorized as RRI responders if their RRI decreased by ≥0.05 during the MAP elevation. Subsequently, patients were randomized to a “low” (65–70 mm Hg) or “high” (80–85 mm Hg) MAP target for five days, stratified by RRI response status. The primary renal outcomes evaluated included urine output, Kidney Disease: Improving Global Outcomes (KDIGO) stage, serum creatinine trajectory, and need for renal replacement therapy.
Key Findings
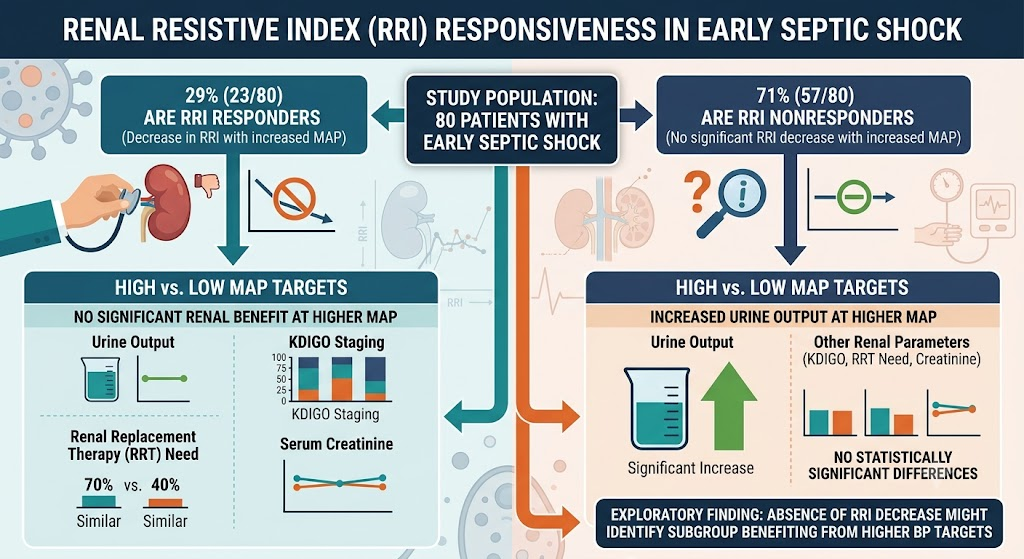
Eighty patients were enrolled; 29% (23/80) were RRI responders. Among responders, increasing MAP did not confer significant benefits in renal outcomes: urine output, KDIGO staging, necessity for renal replacement therapy, or serum creatinine levels remained similar between low and high MAP targets.
Conversely, in RRI nonresponders, patients randomized to the higher MAP target exhibited an increase in urine output compared to those with lower MAP, although other renal parameters did not show statistically significant differences. This exploratory finding suggests that absence of RRI decrease under MAP elevation might identify a subgroup potentially benefiting from higher blood pressure targets.
The study found no evidence supporting routine use of RRI responsiveness as a robust bedside tool to guide MAP target individualization for renal protection in early septic shock. However, the divergent physiological responses hint at heterogeneity in renal perfusion dynamics and vasopressor effects in septic shock.
Expert Commentary
The study addresses a clinically relevant question in critical care nephrology: how to individualize MAP targets to optimize renal outcomes in septic shock. Despite intuitive appeal, RRI responsiveness to transient MAP changes was not a reliable predictor for benefit from higher MAP targets. This aligns with previous large trials that found no universal advantage for aggressive MAP elevation beyond 65 mm Hg, although some patient subgroups (e.g., chronic hypertension) might benefit.
Physiologically, RRI combines influences from renal vascular resistance, systemic hemodynamics, and intrarenal compliance, complicating its interpretation. Furthermore, vasopressors may have direct and indirect renal vascular effects independent of perfusion pressure changes.
Limitations include sample size, single-center design, and the short duration of the MAP test, possibly insufficient to capture dynamic renal adaptations. Additionally, urine output changes in nonresponders under high MAP warrant further mechanistic and outcome validation.
Current expert consensus still emphasizes a MAP target ≥65 mm Hg for most patients, with individualization guided by clinical context, comorbidities, and organ function rather than sole reliance on RRI.
Conclusion
This physiological study reveals that RRI decrease during transient MAP elevation does not identify patients who will benefit from a higher MAP target to improve renal function in early septic shock. However, lack of RRI decrease may signal patients whose urine output improves with higher MAP, suggesting the complexity of renal hemodynamic responses. Further research is needed to refine bedside tools for personalized hemodynamic targets in sepsis-related AKI.
Funding and ClinicalTrials.gov
The study was conducted at the medical ICU of a university hospital and was supported by institutional research funding. Specific grant details and ClinicalTrials.gov registration number were not disclosed in the source abstract.
References
Asfar P, et al. High versus low blood-pressure target in patients with septic shock. N Engl J Med. 2014;370(17):1583-1593.
Beloncle F, et al. Renal resistive index: a marker of renal perfusion and outcome in AKI? Intensive Care Med. 2018;44(7):1034-1036.
James MT, et al. Acute kidney injury and chronic kidney disease: location of interplay. Nat Rev Nephrol. 2015;11(4):187-200.
Kashani K, et al. Creatinine kinetics and the definition of acute kidney injury. Crit Care. 2017;21(1):68.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.