Highlight
1. Transcatheter tricuspid-valve repair combined with medical therapy significantly improves clinical outcomes in patients with symptomatic severe tricuspid regurgitation.
2. The intervention reduces the composite risk of death from any cause or hospitalization for heart failure up to three years.
3. Quality of life measures are notably enhanced post-procedure.
4. The procedure has an acceptable safety profile with a low rate of major adverse events within 30 days.
Study Background
Severe tricuspid regurgitation (TR) is a prevalent valvular heart condition that frequently complicates the clinical course of patients with heart failure, leading to worsening symptoms, recurrent hospitalizations, and increased mortality. Traditionally, medical therapy alone has been the cornerstone of management for patients ineligible or high risk for surgical intervention. However, surgical correction of TR has often been limited due to the invasiveness and poor risk-benefit profile, especially in elderly patients. Consequently, minimally invasive transcatheter tricuspid-valve repair has emerged as a promising alternative, aiming to reduce regurgitant volume, improve cardiac function, and ultimately impact meaningful clinical outcomes. Despite observational data suggesting potential benefits, definitive evidence from randomized controlled trials had been lacking prior to the TRIC-I-HF study.
Study Design
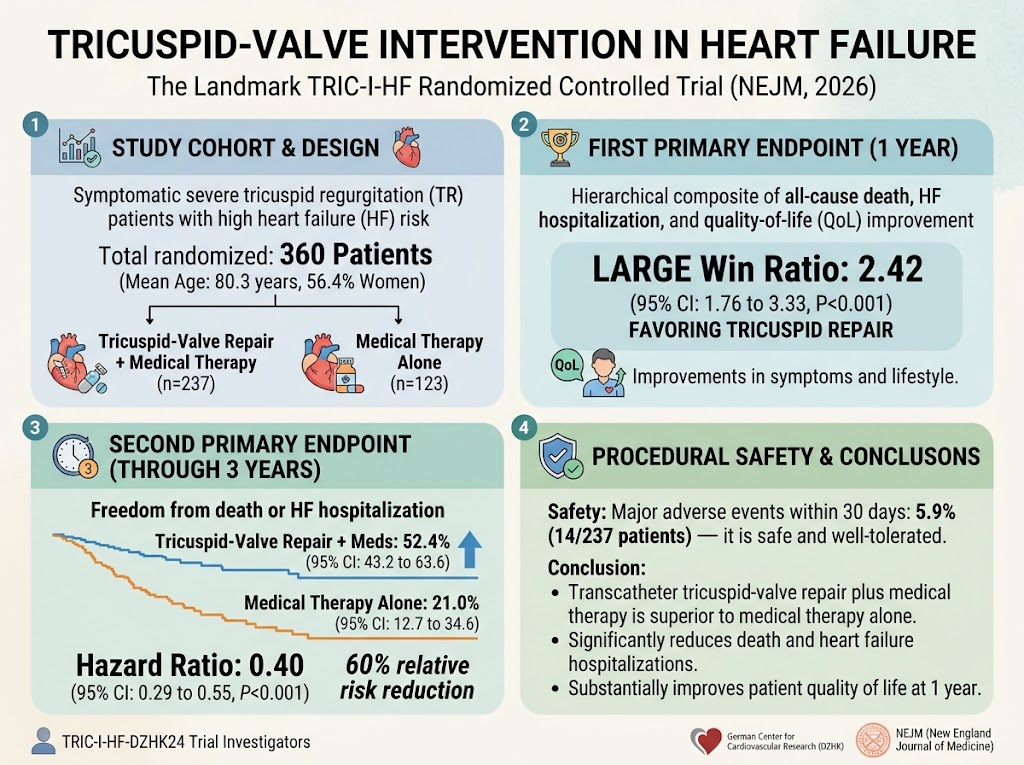
The TRIC-I-HF trial was a prospective, randomized, controlled study designed to evaluate the efficacy and safety of transcatheter tricuspid-valve repair added to guideline-directed medical therapy compared with medical therapy alone in patients with symptomatic severe TR at high risk for heart-failure events. A total of 360 patients were randomized in a 2:1 ratio: 237 patients underwent transcatheter tricuspid-valve repair with continued medical therapy (tricuspid-repair group), while 123 received medical therapy alone (medical-therapy group). The mean age was 80.3 years, with a slight majority being women (56.4%).
Primary outcomes encompassed a hierarchical composite endpoint evaluated at one year, integrating death from any cause, hospitalization for heart failure, and improvement in quality of life measured using validated assessment tools, analyzed by the win ratio methodology. Upon demonstration of statistical significance, a second primary endpoint comprising a composite of death from any cause or heart failure hospitalization through three years was assessed.
Key Findings
The study demonstrated a clear superiority of transcatheter tricuspid-valve repair plus medical therapy over medical therapy alone. The win ratio for the first primary endpoint was 2.42 (95% CI, 1.76 to 3.33; P<0.001), indicating that the odds of a better clinical outcome in the intervention group were more than double compared to controls. This composite assessed the avoidance of death and heart failure hospitalization and improvement in quality of life, all translating to a composite clinical benefit at one year.
Longitudinal follow-up over three years reinforced the durability of benefit. The Kaplan-Meier analysis revealed a 52.4% freedom from the combined endpoint of death or heart failure hospitalization in the tricuspid-repair group versus just 21.0% in the medical-therapy group (hazard ratio [HR] 0.40; 95% CI, 0.29 to 0.55; P<0.001), equating to a 60% relative risk reduction. This robust risk reduction underscores the sustained effectiveness of the intervention in improving survival and reducing morbidity.
Regarding safety, the procedure exhibited an acceptable safety profile, with major adverse events occurring in 5.9% of patients within 30 days post-procedure. Considering the advanced age and comorbidities in the patient population, this reflects a favorable risk-benefit ratio.
Expert Commentary
The TRIC-I-HF trial provides the highest level evidence supporting the integration of transcatheter tricuspid-valve repair into the management algorithm for severe TR patients with heart failure symptoms. The multidimensional hierarchical endpoint design, which incorporates mortality, heart failure hospitalizations, and quality-of-life improvements, offers a comprehensive assessment that aligns with patient-centered outcomes valued in clinical practice.
Nonetheless, certain considerations must be acknowledged. The study population was elderly with considerable comorbidities, which supports external validity to everyday clinical populations but may limit generalizability to younger, lower-risk cohorts. Additionally, while procedural safety was acceptable, the long-term durability of valve repair merits further surveillance beyond three years.
Mechanistically, reducing the volume overload on the right heart by mitigating tricuspid regurgitation enhances right ventricular efficiency and reduces systemic venous congestion, thereby interrupting the vicious cycle exacerbating heart failure symptoms. Improvements in patient-reported outcomes further emphasize the quality-of-life benefits that complement survival advantages.
Conclusion
The TRIC-I-HF trial establishes that transcatheter tricuspid-valve repair, when added to optimized medical therapy, significantly improves survival, reduces heart failure hospitalizations, and enhances patient quality of life among individuals with symptomatic severe tricuspid regurgitation. This minimally invasive strategy represents a transformative advance in the management of a condition historically associated with poor prognosis and limited therapeutic options. Future research should focus on refining patient selection criteria, exploring combination therapies, and assessing long-term durability and cost-effectiveness.
Funding and Registration
This investigator-initiated study was funded by the German Center for Cardiovascular Research and various collaborators. The clinical trial was registered under ClinicalTrials.gov number NCT04634266.
References
- Hausleiter J, Stocker TJ, Geisler T, et al. Tricuspid-Valve Intervention in Heart Failure. N Engl J Med. 2026;395(14):1363-1373. PMID: 42670975.