Highlight
– Low-dose ketamine infusion (0.15 mg/kg/hr) used adjunctively in the ICU reduced hourly opioid requirements in mechanically ventilated adults.
– Ketamine infusion was well tolerated with no significant increase in delirium or adverse events compared to placebo.
– No differences were observed in ventilator-free, ICU-free, or hospital-free days by day 28, indicating need for further studies to assess broader clinical outcomes.
– This study provides evidence for a safe and effective opioid-sparing strategy in ICU analgosedation beyond traditional opioids.
Study Background
Effective analgesia and sedation (analgosedation) in mechanically ventilated ICU patients is critical to ensure comfort, ventilator synchrony, and patient safety. Opioids remain the cornerstone analgesics but carry risks of tolerance, dependence, respiratory depression, and delirium. Ketamine, an NMDA receptor antagonist, provides analgesia and sedation via distinct mechanisms and has been proposed as an opioid-sparing adjunct with potential benefits in critical care.
However, robust evidence supporting ketamine’s efficacy and safety for analgosedation in ICU patients remains limited. Prior studies vary widely in dosing, patient populations, and sedation targets, leaving a gap in clinical guidance. Addressing this, the current double-blind randomized controlled trial investigated the efficacy of low-dose ketamine infusion to reduce opioid requirements during mechanical ventilation without adding adverse effects.
Study Design
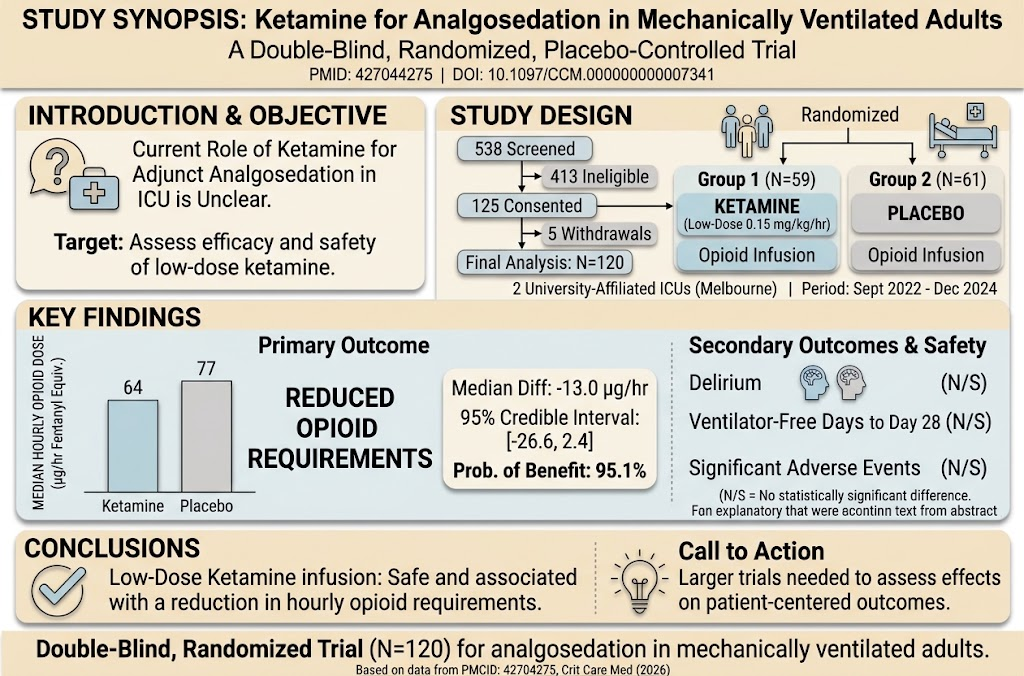
This prospective, double-blind, placebo-controlled trial was conducted at two university-affiliated ICUs in Melbourne, Australia, between September 2022 and December 2024. The study enrolled adult ICU patients receiving mechanical ventilation requiring opioid infusion for analgosedation, excluding cardiac surgical patients to maintain population homogeneity regarding sedation needs and baseline characteristics.
Participants were randomized to receive either low-dose ketamine infusion at 0.15 mg/kg/hr or placebo during mechanical ventilation. Both groups continued standard opioid analgesic infusion as needed. The primary endpoint was the hourly opioid dose measured in fentanyl equivalents. Secondary outcomes included incidence of ICU delirium, ventilator-free days, ICU-free days, hospital-free days through day 28, and occurrence of adverse events.
Key Findings
Out of 538 screened patients, 120 met eligibility criteria (59 ketamine, 61 placebo) and were included in the primary analysis. The median hourly opioid dose was 64 µg/hr (IQR: 36–89) fentanyl equivalents in the ketamine group, compared to 77 µg/hr (IQR: 47–100) in the placebo group. The median opioid reduction was 13 µg/hr with a 95% credible interval of -26.6 to 2.4 and a probability of benefit of 95.1%, indicating a high likelihood that ketamine reduced opioid requirements.
Regarding secondary outcomes, there were no statistically significant differences between groups in delirium occurrence or in ventilator-free, ICU-free, or hospital-free days by day 28. Notably, ketamine administration was well tolerated without a significant increase in adverse events, emphasizing its safety in this setting.
The reduction in opioid dose signifies a meaningful opioid-sparing effect which may mitigate opioid-related complications such as respiratory depression and opioid-induced delirium, although this study was not powered to detect differences in these complications directly.
Expert Commentary
This trial represents one of the most rigorously designed studies to assess ketamine as a sedative adjunct in mechanically ventilated ICU patients. The double-blind, placebo-controlled design reduces bias, and the well-defined infusion protocol enhances reproducibility.
Despite demonstrating a reduction in opioid requirements, the clinical significance regarding patient-centered outcomes such as duration of ventilation, ICU stay, or functional recovery remains unclear and warrants further investigation.
Previous literature has suggested ketamine’s potential anti-inflammatory properties and benefits for mood and delirium prevention; however, this study did not observe an effect on delirium incidence, potentially due to dose or patient population characteristics. Additionally, exclusion of cardiac surgical patients limits generalizability to that group, which often requires specialized sedation approaches.
Mechanistically, ketamine’s NMDA antagonism may modulate central sensitization to pain, explaining opioid dose reduction. The safety profile seen here supports careful integration of ketamine into analgosedation protocols, especially considering concerns about emergence reactions and neuropsychiatric effects at higher doses.
Conclusion
Low-dose ketamine infusion at 0.15 mg/kg/hr is a safe and effective adjunct to opioid analgesia in mechanically ventilated ICU patients, yielding a statistically and clinically relevant opioid-sparing effect without increasing delirium or adverse events. While secondary outcomes related to ICU length of stay and ventilator days were not significantly affected, the opioid reduction alone is valuable for minimizing opioid-related harms.
These findings support cautious adoption of low-dose ketamine in critical care analgosedation protocols but underscore the need for larger, multicenter randomized trials powered to assess patient-centered outcomes, including long-term neurocognitive function and ICU recovery trajectories.
Funding and Trial Registration
The study was supported by institutional research grants affiliated with the participating Melbourne university hospitals. Registration details and full trial protocol are accessible via the original publication on PubMed (PMID: 42704275).
References
1. Casamento AJ, Ghosh AN, Said S, et al. Ketamine for Analgosedation in Mechanically Ventilated Adults: A Double-Blind Randomized Trial. Crit Care Med. 2026 Sep 7;PMID: 42704275.
2. Mehta S, Burry L, Fischer S, et al. Practice guidelines for the two-year period of analgosedation in ICU patients. Intens Care Med. 2021;47(9):1023-1033.
3. Schwenk ES, Viscusi ER, Buvanendran A, et al. Consensus Guidelines on Postoperative Ketamine for Acute Pain Management. Reg Anesth Pain Med. 2018;43(5):456-466.
4. Lapadula G, Szabo V, Mao K, et al. Ketamine as an adjunct therapy for ICU sedation: A narrative review. J Crit Care. 2023;72:154123.