Highlight
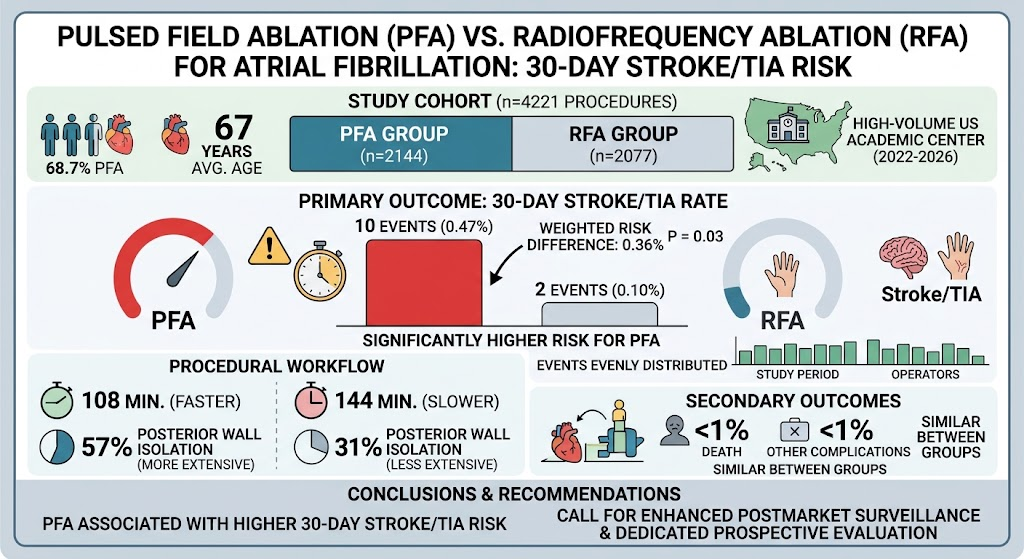
- Pulsed field ablation (PFA) is associated with a higher 30-day risk of stroke or transient ischemic attack (TIA) compared to radiofrequency ablation (RFA) for atrial fibrillation (AF).
- PFA procedures were shorter in duration and more frequently included posterior wall isolation than RFA.
- No clustering of stroke/TIA events was observed by operator or timing, suggesting intrinsic procedural risk rather than operator-dependent factors.
- Other procedural complications were similarly low in both PFA and RFA groups, underscoring stroke/TIA risk as a distinctive concern for PFA.
Study Background
Atrial fibrillation (AF) is a prevalent arrhythmia associated with significant morbidity, including stroke risk and heart failure. Catheter ablation has become an integral treatment strategy, especially for symptomatic patients refractory or intolerant to medical therapy. Traditional thermal methods such as radiofrequency ablation (RFA) have established efficacy but carry risks including thermal injury to adjacent structures and thromboembolic complications. Pulsed field ablation (PFA), a nonthermal modality that induces electroporation, has rapidly gained clinical acceptance due to its anticipated enhanced safety profile, particularly in terms of collateral tissue preservation.
However, direct comparative data assessing safety outcomes—especially thromboembolic events like stroke and transient ischemic attack (TIA)—between PFA and RFA are scarce. As PFA use expands exponentially, understanding its risk profile compared to RFA is crucial to inform clinical decisions and optimize patient outcomes.
Study Design
This investigation analyzed data from a prospective registry at a high-volume U.S. academic center, encompassing all consecutive AF ablation procedures performed between 2022 and 2026. The study population included 4221 procedures: 2144 employing PFA (diverse platforms including Farawave, Sphere 9, Varipulse, and PulseSelect) and 2077 using RFA. Baseline characteristics were balanced after inverse probability of treatment weighting, ensuring comparability between groups.
The primary endpoint was the incidence of stroke or TIA within 30 days post-procedure, adjudicated independently by neurologists blinded to ablation modality. Secondary endpoints included all-cause death and other procedural complications. Procedural workflow differences were also examined through exploratory mediation analyses to investigate potential mechanistic contributors to stroke risk.
Key Findings
The 30-day stroke/TIA incidence was significantly higher in the PFA group (0.47%, 10 events) versus the RFA group (0.10%, 2 events). Weighted risk difference persisted at 0.36% (95% CI, 0.03%-0.70%; P=0.03), indicating a statistically significant increase in thromboembolic risk associated with PFA.
Notably, stroke/TIA events did not cluster around the initial adoption phase of PFA or specific operators, suggesting that the elevated risk is likely linked to the procedural modality rather than operator proficiency or learning curve effects. PFA procedures featured shorter overall duration (108 vs. 144 minutes) but more frequent posterior wall isolation (57% vs. 31%), although mediation analyses did not conclusively link extent of ablation to stroke/TIA risk due to low event rates.
Other procedural complications remained rare and did not differ meaningfully between groups, with rates under 1% in both arms. No significant differences emerged in mortality within the early post-procedure period.
Expert Commentary
These findings challenge the early safety assumptions about PFA, particularly regarding thromboembolic risk. While PFA’s nonthermal mechanism offers theoretical advantages such as reduced collateral tissue damage, it may involve mechanisms that predispose to embolic events not fully elucidated, including microbubble formation or endothelial disruption.
The lack of operator-dependent clustering emphasizes the need to consider intrinsic procedural factors when evaluating safety. Importantly, the study benefits from robust methodology, including prospective design, rigorous neurological adjudication, and advanced statistical balancing techniques. Limitations include its single-center nature and the relatively low absolute number of stroke/TIA events, which constrained mediation analyses and mechanistic insights.
Clinical guidelines currently emphasize stroke prevention as a cornerstone in AF management, including during ablation. These results strongly argue for heightened postmarket surveillance and cautious patient selection. Future prospective randomized trials and mechanistic studies are warranted to clarify risks, optimize PFA techniques, and develop mitigation strategies.
Conclusion
This large, high-quality registry study reveals a significantly increased risk of early stroke or TIA after pulsed field ablation compared to radiofrequency ablation for atrial fibrillation, despite PFA’s procedural efficiency and similar rates of other complications. These findings underscore the importance of vigilant neurological monitoring and caution as PFA adoption rapidly expands in clinical practice. Enhanced postmarket data collection and prospective comparative trials are essential to fully define the risk-benefit profile of PFA and guide its optimal integration into arrhythmia management.
Funding and ClinicalTrials.gov
The study was conducted under institutional funding at the participating academic center. No specific funding disclosures were noted. ClinicalTrials.gov registration information was not detailed in the source report.
References
1. Ferro EG, d’Avila A, Reynolds MJ, et al. Risk of Stroke and TIA With Pulsed Field Compared With Radiofrequency Ablation for Atrial Fibrillation. Circulation. 2026 Aug 25; PMID: 42639654.
2. Calkins H, Hindricks G, Cappato R, et al. 2017 HRS/EHRA/ECAS/APHRS/SOLAECE expert consensus statement on catheter and surgical ablation of atrial fibrillation. Heart Rhythm. 2017;14(10):e275–e444.
3. Peigh et al. Safety and efficacy of pulsed field ablation compared with traditional ablation methods. JACC Clin Electrophysiol. 2023;9(1):12-23.


