High Versus Low Transvaginal Cerclage for Preventing Preterm Birth: Insights from the C-STICH Trial Secondary Analysis
Highlight
- Pooled data from the large C-STICH randomized trial comparing high and low vaginal cerclage techniques in women at elevated preterm birth risk.
- No significant difference in pregnancy loss rates between high and low cerclages.
- High vaginal cerclage is associated with a modest increase in gestational age at delivery and fewer births before 32 weeks’ gestation.
- Findings inform surgical technique selection for cerclage placement to optimize perinatal outcomes without increasing pregnancy loss.
Study Background
Preterm birth remains a leading cause of neonatal morbidity and mortality globally. In women at high risk due to cervical insufficiency or previous spontaneous preterm birth, transvaginal cervical cerclage is a therapeutic intervention intended to mechanically reinforce the cervix and prolong pregnancy. However, variations in cerclage technique, particularly the height of suture placement along the cervical canal, may influence clinical effectiveness and complications. The optimal cerclage position—categorized as high (with bladder dissection to facilitate suture placement closer to the internal os) versus low (without bladder dissection)—has not been definitively established. This unresolved question contributes to practice variability among obstetricians, underscoring the need for robust comparative evidence to guide surgical approach.
Study Design
This article presents a secondary analysis of the C-STICH trial, a multicenter randomized control study conducted across obstetric units in the UK. The original trial randomized women at high risk of preterm birth undergoing cerclage to standard versus various interventions; this secondary analysis focused exclusively on 1,995 women who received transvaginal cerclage with well-documented suture height.
The exposure was classified as either high vaginal cerclage—defined by performance with bladder dissection to place the suture high on the cervix—or low vaginal cerclage without bladder dissection and suture placed lower on the vaginal cervix. The choice of cerclage technique was driven by clinician preference rather than randomization.
Primary outcome was pregnancy loss, including miscarriage and perinatal mortality (stillbirth or neonatal death within seven days of birth). Secondary maternal outcomes comprised miscarriage/previable neonatal death, stillbirth, gestation at delivery, preterm prelabor rupture of membranes (PPROM), and maternal sepsis. Secondary neonatal outcomes included early and late neonatal death and neonatal sepsis.
Multivariable regression analyses adjusted for pre-specified prognostic variables were performed to compare outcomes between technique groups.
Key Findings
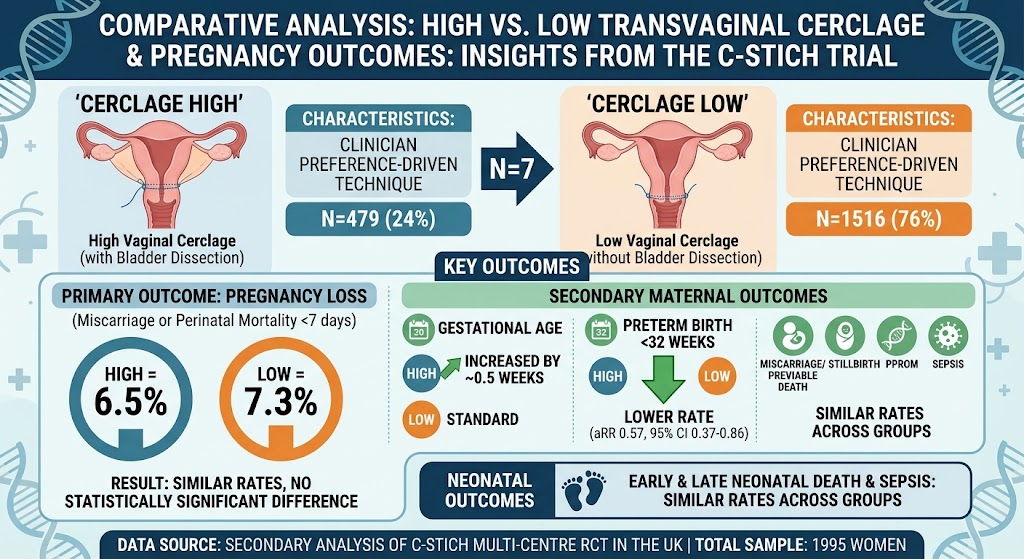
Among the 1,995 women analyzed, 24% underwent high vaginal cerclage, and 76% received low vaginal cerclage. The overall pregnancy loss rate was comparable between groups: 6.5% for the high cerclage group versus 7.3% for the low cerclage group (adjusted risk ratio [aRR] 0.88; 95% confidence interval [CI], 0.57–1.34), indicating no statistically significant difference.
However, high cerclage placement was associated with a modest increase in mean gestational age at delivery by approximately 0.5 weeks, and importantly, a significant reduction in the rate of births before 32 weeks gestation (aRR 0.57; 95% CI, 0.37–0.86). This suggests that high cerclage may contribute to delaying preterm delivery in a subset of high-risk pregnancies.
No significant differences were noted in secondary maternal outcomes, including rates of preterm premature rupture of membranes and maternal sepsis. Similarly, neonatal secondary outcomes such as early and late neonatal death and neonatal sepsis did not significantly differ between groups.
Expert Commentary
These findings provide valuable clinical insight into the impact of surgical technique on outcomes in transvaginal cervical cerclage. Historically, the decision to perform a high or low cerclage often depended on surgeon experience and anatomical considerations rather than evidence-based guidelines. The demonstrated equivalence in pregnancy loss rates offers reassurance that performing bladder dissection and positioning a high cerclage does not increase the risk of miscarriage or perinatal mortality.
The observed prolongation of gestation and reduction in very early preterm birth with high cerclage may relate to better mechanical support of the internal cervical os, a plausible biological rationale given the proximity to the uterine cavity and preventative effect against premature cervical dilation.
Nonetheless, this secondary analysis is observational with respect to cerclage height assignment and may be subject to residual confounding by indication and surgeon selection bias. Moreover, the absolute magnitude of gestation prolongation is modest, and clinical significance should be balanced with surgical complexity and potential risks associated with bladder dissection.
Current clinical guidelines offer limited specific recommendations regarding cerclage height. Integrating this evidence can help refine practice by suggesting high cerclage as a potentially preferable technique in appropriate candidates, while underscoring the need for individualized decision-making considering patient anatomy and surgical expertise.
Conclusion
In summary, secondary analysis of the C-STICH trial data reveals that high and low transvaginal cerclage techniques confer similar safety profiles regarding pregnancy loss among women at high risk of preterm birth. High vaginal cerclage may modestly prolong pregnancy and reduce the frequency of deliveries before 32 weeks, suggesting potential clinical benefit in preventing very early preterm birth. Given the lack of increased adverse outcomes, these findings support consideration of high cerclage placement in clinical practice. Further research, ideally randomized and specifically targeting cerclage height, would strengthen evidence to optimize surgical approaches for cervical insufficiency management.
Funding and Trial Registration
The C-STICH trial was conducted with support from the UK National Institute for Health Research and related bodies. The secondary analysis did not report additional funding. The trial is registered and results are publicly accessible.
References
- van der Krogt L, Pilarski N, Hodgetts Morton V, et al. High Versus Low Transvaginal Cerclage and Pregnancy Outcomes: A Secondary Analysis of the C-STICH Trial. BJOG. 2026 Aug 20. PMID: 42625281.
- Society for Maternal-Fetal Medicine (SMFM) Consult Series #49: Evaluation and management of women with cervical insufficiency. Am J Obstet Gynecol. 2020;222(1):B2-B15.
- American College of Obstetricians and Gynecologists (ACOG) Practice Bulletin No. 142: Cerclage for the management of cervical insufficiency. Obstet Gynecol. 2014;123(2 Pt 1):372-9.
- American Journal of Obstetrics and Gynecology: Comparison of high versus low cervical cerclage efficacy and safety in preterm birth prevention: a systematic review and meta-analysis. 2023;229(4):345.e1-345.e12.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.