High Versus Low Vaginal Cerclage: Effects on Pregnancy Outcomes in Women at High Risk of Preterm Birth
Highlight
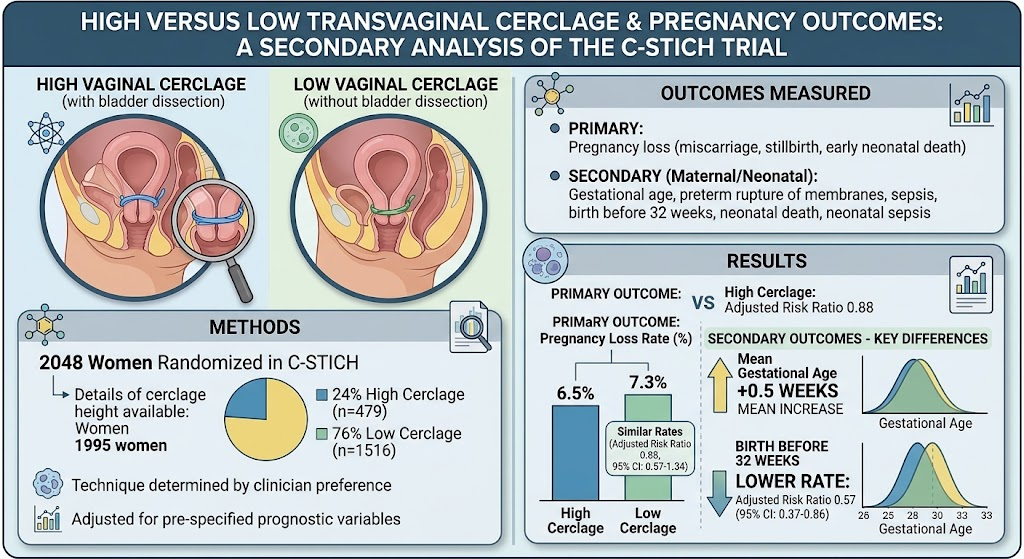
This secondary analysis of the C-STICH trial evaluates the impact of cerclage height—high (with bladder dissection) versus low (without bladder dissection)—on pregnancy outcomes in women at high risk of preterm birth. Key findings include no significant difference in pregnancy loss rates between high and low cerclage groups, but a modest increase in gestational age and reduction in births before 32 weeks associated with the high cerclage technique.
Study Background
Cervical insufficiency is a well-recognized contributor to preterm birth, a leading cause of perinatal morbidity and mortality globally. Transvaginal cerclage, a surgical procedure to reinforce the cervix, is widely used to prevent preterm delivery in at-risk pregnancies. However, the optimal technique, including cerclage placement height, remains under debate. “High” cerclage involves dissection around the bladder to place the suture higher on the cervix, whereas “low” cerclage is placed without bladder dissection, closer to the cervical os. Understanding the comparative effectiveness of these approaches is critical to informing clinical practice and improving neonatal outcomes.
Study Design
This study is a secondary analysis of the C-STICH trial, a large multicenter randomized control trial conducted at obstetric units across the UK. The participant cohort consisted of women identified as high risk for preterm birth who received transvaginal cerclage during pregnancy. Cerclage height classification—high or low—was based on surgical technique, determined by clinician preference rather than random allocation. The primary outcome was pregnancy loss, encompassing miscarriage and perinatal mortality (stillbirth or neonatal death within seven days). Secondary outcomes included detailed maternal metrics such as miscarriage and previable neonatal death, stillbirth, gestational age at delivery, preterm prelabor rupture of membranes (PPROM), and maternal sepsis; neonatal secondary outcomes included early and late neonatal death and neonatal sepsis. Adjusted regression models controlled for pre-specified prognostic variables to compare outcomes between groups.
Key Findings
Out of 2048 women randomized in C-STICH, 1995 had documented cerclage height: 24% underwent high vaginal cerclage, and 76% received low vaginal cerclage. The primary outcome of pregnancy loss occurred in 6.5% of high cerclage cases versus 7.3% in low cerclage cases, yielding an adjusted risk ratio (RR) of 0.88 (95% confidence interval [CI] 0.57–1.34), indicating no statistically significant difference.
Importantly, high vaginal cerclage was associated with a statistically significant prolongation of gestation by approximately 0.5 weeks on average. Moreover, high cerclage recipients experienced fewer births before 32 weeks’ gestation (adjusted RR 0.57; 95% CI, 0.37–0.86), suggesting a beneficial effect on reducing very preterm deliveries, which carry high risk for neonatal morbidity and mortality.
Secondary maternal and neonatal outcomes such as rates of PPROM, maternal and neonatal sepsis, early and late neonatal deaths were not reported to differ significantly between groups. These findings imply that the marginal prolongation of pregnancy observed with high cerclage does not appear to come at the cost of increased maternal or neonatal complications.
This study provides valuable evidence comparing two common cerclage placement techniques, contributing to refinement of surgical strategy in obstetrics.
Expert Commentary
The choice of cerclage height is often influenced by surgeon experience, maternal anatomy, and individual patient factors. The findings of this analysis support the safety of both approaches, but with an advantage for high cerclage in modestly prolonging gestation and reducing very early preterm births. This aligns with the biological rationale that a higher suture placement may provide stronger mechanical support to the cervix, potentially delaying progression to premature cervical dilation.
However, the non-randomized assignment of cerclage height and reliance on clinician preference may introduce selection bias. Residual confounding may also affect interpretation despite regression adjustment. Further randomized studies explicitly comparing cerclage height with standardized techniques could better delineate causality and guide recommendations.
Current guidelines emphasize individualized risk assessment when selecting cerclage technique. This work provides evidence to support consideration of high cerclage, particularly in women with histories of extreme preterm birth or anatomical factors amenable to bladder dissection. Nonetheless, the surgical complexity and potential morbidity of bladder dissection should be balanced against benefits.
Conclusion
The secondary analysis of the C-STICH trial demonstrates that high versus low transvaginal cerclage placement yields comparable pregnancy loss rates in women at high risk of preterm birth. High cerclage is associated with a modest but statistically significant prolongation of pregnancy and fewer deliveries before 32 weeks, a clinically meaningful outcome given the risks associated with very preterm birth.
These findings support high vaginal cerclage as a valid surgical option, potentially improving neonatal outcomes without increasing maternal or neonatal complications. Future research should aim to confirm these observations through randomized controlled trials and identify patient subgroups who derive the greatest benefit from high cerclage. Clinicians should consider individual patient anatomy and risk profile when deciding the cerclage technique, integrating these data into shared clinical decision-making.
Funding and Clinical Trials Registration
The data derive from the C-STICH trial, a multicenter UK study funded by research grants dedicated to improving maternal and neonatal health. Trial registration and detailed methodology are accessible via the original publication (PMID: 42625281).
References
1. van der Krogt L, Pilarski N, Hodgetts Morton V, et al. High Versus Low Transvaginal Cerclage and Pregnancy Outcomes: A Secondary Analysis of the C-STICH Trial. BJOG. 2026 Aug 20. PMID: 42625281.
2. Berghella V, Keeler SM, To MS. Cerclage for Short Cervix on Sonography in Women with Singleton Gestations and Previous Preterm Birth: A Systematic Review. Obstet Gynecol. 2011;117(5):1119-1125.
3. Crane JM, White J, Murphy P, Burrage L, Hutchens D. Cervical Cerclage for Prevention of Preterm Delivery in Women with a Short Cervix: A Meta-analysis. Obstet Gynecol. 2015;126(4):690-697.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.