Highlight
– Iatrogenic cerebral amyloid angiopathy (iCAA) manifests after a long latency averaging nearly four decades post-exposure to amyloid-beta via medical procedures.
– Patients with iCAA face a substantial annual risk (~20%) of symptomatic intracerebral hemorrhage (ICH), especially those initially presenting with ICH or exposed by brain surgery.
– Cognitive impairment affects over half of patients within two years following diagnosis.
– Mortality remains low despite the high hemorrhagic burden, indicating a complex disease trajectory distinct from sporadic forms.
Study Background
Cerebral amyloid angiopathy (CAA) is characterized by amyloid-beta protein deposition in the cerebral vasculature, predisposing patients to intracerebral hemorrhages and cognitive decline. A novel subtype, iatrogenic CAA (iCAA), has recently gained recognition. This rare disorder likely results from inadvertent transmission of amyloid-beta aggregates during neurosurgical or other medical interventions involving central nervous system structures. With global case numbers on the rise, understanding the clinical course and prognosis of iCAA is critical to optimizing patient care and informing surveillance strategies. Given the protracted latency between exposure and clinical manifestation, long-term data have been limited. The present multinational European study addresses this gap by analyzing progression and outcomes of iCAA based on a cohort of 82 patients.
Study Design
This observational cohort study selected patients from Austria, Italy, The Netherlands, and the United Kingdom who fulfilled modified Queen Square criteria for possible or probable iCAA. Inclusion required a history of prior neurosurgical or related procedures with suspected amyloid-beta transmission and clinical diagnosis confirmed by radiological and/or pathological criteria. The study aggregated data from the largest case series available (minimum n=5 per series).
Clinical endpoints focused on symptomatic intracerebral hemorrhage (ICH), convexity subarachnoid hemorrhage (cSAH), cognitive status at last follow-up, and mortality. Statistical analyses, including Cox regression models, identified clinical variables associated with outcome events. Follow-up extended up to 5.9 years, encompassing a total of 385 patient-years.
Key Findings
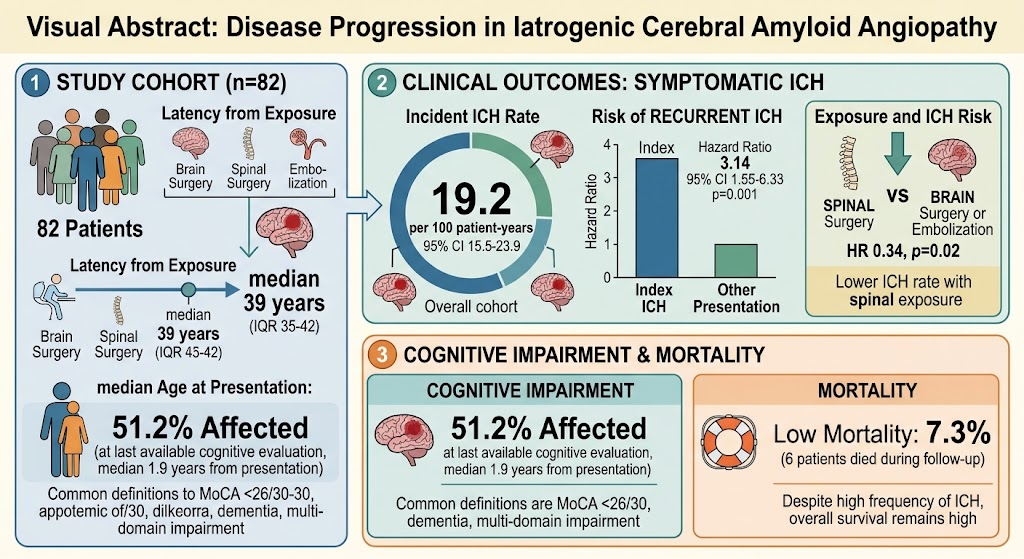
The cohort included 82 patients (median age 50 years, 59.8% male) diagnosed with iCAA approximately 39 years after presumed exposure. Initial presentations were intracerebral hemorrhage in 50% and cSAH/transient focal neurologic episodes in 32.9%.
During the follow-up period, 74 symptomatic ICH events occurred, yielding an incidence rate of 19.2 per 100 patient-years post-presentation—a notably high hemorrhagic burden when compared to sporadic CAA populations.
Recurrence risk was not uniform. Those presenting with ICH initially had a significantly increased hazard of subsequent ICH (hazard ratio [HR] 3.14; 95% confidence interval [CI] 1.55–6.33; p=0.001), with a recurrence rate of 24.6 per 100 patient-years. In contrast, presenting with cSAH linked to a lower hemorrhage recurrence rate.
Exposure type influenced outcomes as well. Patients exposed via spinal surgery (n=24) exhibited a substantially reduced risk of ICH compared with those exposed by brain surgery or endovascular embolization (HR 0.34; 95% CI 0.13–0.87; p=0.02), suggesting that the anatomical site and procedure type may modulate transmission dynamics and disease severity.
Cognitive impairment was frequent, affecting 51.2% of patients at a median of 1.9 years after initial presentation, highlighting the neurodegenerative consequences beyond vascular events.
Mortality was low, with only six deaths (7.3%) over the follow-up period, split evenly between patients initially presenting with ICH and those with cSAH.
Expert Commentary
This study provides pivotal long-term insight into iCAA, a condition likely underrecognized due to its decades-long incubation period. The high rate of recurrent symptomatic ICH, especially among patients with initial hemorrhage and those exposed via brain surgeries, underscores the need for vigilant clinical monitoring.
The relatively low mortality rate despite frequent hemorrhagic events suggests iCAA has a distinct clinical trajectory compared to sporadic CAA—possibly reflecting younger patient age and differing pathological mechanisms.
The association between type of surgical exposure and hemorrhage risk offers important clues about disease pathophysiology. Procedures involving direct brain manipulation may facilitate more extensive amyloid-beta seeding and vascular deposition than spinal exposure alone.
A limitation is the retrospective nature and heterogeneity of case ascertainment across centers. Nevertheless, these findings warrant inclusion in clinical guidelines for patients with a history of neurosurgical interventions who present with hemorrhagic stroke or cognitive decline.
Conclusion
Iatrogenic cerebral amyloid angiopathy manifests after a protracted latency with a high risk of symptomatic intracerebral hemorrhage and frequent cognitive impairment. Presentation with ICH and exposure via brain surgery portend worse hemorrhagic outcomes. Mortality remains low, differentiating iCAA’s clinical course from other forms of CAA.
This study highlights the importance of recognizing iCAA in patients with compatible clinical and exposure histories, emphasizing long-term surveillance to mitigate hemorrhagic and cognitive complications. Future research should elucidate mechanistic pathways and explore therapeutic strategies to prevent disease progression post-exposure.
Funding and Clinicaltrials.gov
The original study was supported by European collaborative networks across Austria, Italy, The Netherlands, and the United Kingdom. There were no registered clinical trials associated with this cohort analysis.
References
1. Fandler-Höfler S, Storti B, Kaushik K, et al. Disease Progression in Iatrogenic Cerebral Amyloid Angiopathy. Neurology. 2026 Sep 29;107(8):e218511. PMID: 42809801.
2. Greenberg SM, Charidimou A. Diagnosis of cerebral amyloid angiopathy: Evolution of the Boston criteria. Stroke. 2018;49(2):491-497.
3. Banerjee G, Werring DJ. Cerebral amyloid angiopathy: Pathophysiology and clinical implications. Lancet Neurol. 2016;15(6):684-698.
4. Jucker M, Walker LC. Propagation and spread of pathogenic protein assemblies in neurodegenerative diseases. Nat Neurosci. 2018;21(10):1341-1349.