Robotic Whole-Graft Liver Transplantation: Insights from 45 Cases and Benchmark Outcome Analysis
Highlight
– Robotic whole-graft liver transplantation (RLT) is technically feasible and safe in highly specialized centers.
– In a cohort of 44 patients, overall mortality was low (2.3%), with perioperative and early post-transplant outcomes meeting established benchmarks.
– Operative time was initially prolonged but progressively improved, reflecting the learning curve associated with robotic liver transplantation.
– Conversion to open surgery was infrequent (9.1%) and did not lead to adverse outcomes.
Study Background
Liver transplantation (LT) remains the definitive therapy for selected patients with end-stage liver disease and hepatocellular carcinoma (HCC). Traditional open LT, while routinely successful, involves extensive laparotomy with significant surgical trauma and prolonged recovery. Recent advances in minimally invasive surgery have fostered interest in robotic-assisted approaches to liver transplantation, potentially offering reduced surgical trauma, improved visualization, and better ergonomics. However, the complexity of whole-graft liver transplantation using robotic systems poses technical challenges that require specialized expertise.
Since early feasibility reports, robust clinical data benchmarking perioperative and post-transplant outcomes of robotic whole-graft LT against conventional approaches have been scarce. The burden of liver disease including cirrhosis and portal hypertension underscores the need for safe novel surgical techniques that can maintain or improve patient outcomes. This study addresses this gap by analyzing the lessons learned and clinical outcomes from 45 consecutive cases of robotic whole-graft LT performed at two European tertiary centers.
Study Design
This retrospective multicenter cohort study included all consecutive adult patients undergoing robotic whole-graft liver transplantation (RLT) at two European centers between February 2024 and October 2025. Patients with unsuccessful docking leading to conversion prior to robotic surgery were excluded. Detailed preoperative, perioperative, and post-transplant follow-up data were extracted from prospectively maintained institutional databases. The primary outcome measure was the achievement of established benchmark criteria for liver transplantation outcomes, including mortality, morbidity, intensive care unit (ICU) and hospital stay, and operative parameters.
Recipient demographics, disease etiology, and surgical details such as operative time and ischemia durations were analyzed. The cohort’s median Model for End-Stage Liver Disease (MELD) score, prevalence of portal hypertension, and indications for transplantation (notably hepatocellular carcinoma) were described. Follow-up included early post-transplant morbidity and mortality assessment to benchmark safety and efficacy.
Key Findings
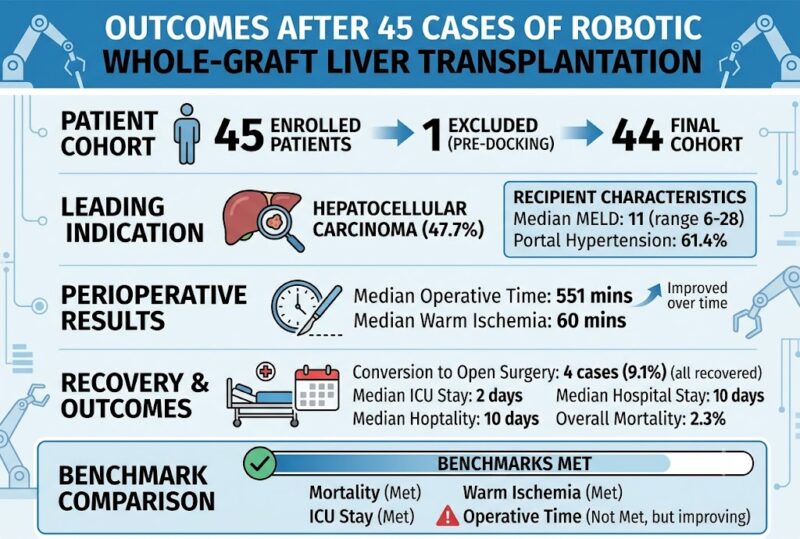
Out of 45 patients, 44 underwent successful robotic whole-graft liver transplantation, with one excluded due to conversion before robotic docking. The leading indication was hepatocellular carcinoma (47.7%), with a median MELD score of 11 (range 6 to 28), reflecting moderate disease severity. Approximately 61.4% had clinically significant portal hypertension, posing additional surgical challenges.
The median operative time was 551 minutes, considerably longer than typical open LT times but showed significant improvement over the study period, highlighting procedural learning curve effects. Median warm ischemia time was 60 minutes, consistent with acceptable transplant practices. Conversion to open surgery occurred in 4 patients (9.1%), successfully managed without perioperative complications, underscoring the importance of patient selection and surgical contingency planning.
Postoperative recovery included median ICU stay of 2 days and hospital length of stay of 10 days, which are comparable to published benchmarks for open transplantation. Overall early post-transplant mortality was low at 2.3%, indicating favorable short-term safety. All predefined benchmark outcome criteria were met except for operative time in early cases, which improved significantly through accrued experience.
Expert Commentary
The clinical implementation of robotic whole-graft liver transplantation, as demonstrated in this multicenter cohort, represents a significant advancement in transplant surgery. The ability to achieve benchmark outcomes in complex hepato-biliary procedures with robotic assistance confirms that with appropriate expertise, this technique is a safe and reproducible alternative to open surgery.
Notably, the initially prolonged operative time reflects the substantial learning curve intrinsic to adopting robotic platforms for transplantation, consistent with experiences in other complex robotic surgeries. The progressive reduction in surgery duration with experience suggests that operative efficiency will improve further with increased procedural volumes and refined techniques.
While the mortality and complication rates were low, long-term follow-up is essential to assess graft survival, rejection rates, and functional outcomes compared to traditional open transplantation. Furthermore, the cost-effectiveness and resource allocation involved in robotic transplantation require additional evaluation.
These findings encourage the cautious expansion of RLT programs in high-volume transplant centers equipped with advanced robotic hepatobiliary surgery expertise. Collaborative multicenter registries and prospective studies will be critical to validate these early results and optimize patient selection criteria.
Conclusion
Robotic whole-graft liver transplantation is a feasible, safe, and efficacious surgical modality that can achieve benchmark perioperative and early post-transplant outcomes comparable to conventional open surgery. Despite initial challenges like extended operative times, improvements associated with the learning curve suggest increasing clinical viability. When performed in specialized centers with multidisciplinary expertise and robotic hepatobiliary skills, RLT offers a promising evolution in liver transplantation surgery. Further research should focus on long-term outcomes, cost-benefit analyses, and the development of standardized protocols to guide broader clinical adoption.
Funding and ClinicalTrials.gov
This study did not specify funding sources or clinical trial registration.
References
1. Di Benedetto F, Magistri P, Coelho JS, et al. Robotic Whole-graft Liver Transplant: Lesson Learned And Outcomes After 45 Cases. Ann Surg. 2026 Aug 6; PMID: 42557614.
2. Sapisochin G, Gagliano A, Rotellar F, et al. Minimally invasive liver transplantation: a systematic review. World J Gastroenterol. 2020;26(21):2876-2885.
3. D’Alessandro AM, Frongillo F, Anselmo A, et al. Robotic Surgery in Liver Transplantation: Current Status and Perspectives. Transplant Proc. 2023;55(5):1383-1390.
4. European Liver Transplant Registry. Annual Report 2024.
5. Belli G, Lanari J, Conti S, et al. Robotic liver resection and transplantation: state of the art and future perspectives. World J Hepatol. 2022;14(7):896-908.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.