Impact of Early Surgical Excision on Survival in Severe Burns: Insights from a Multicenter Prospective Study
Highlight
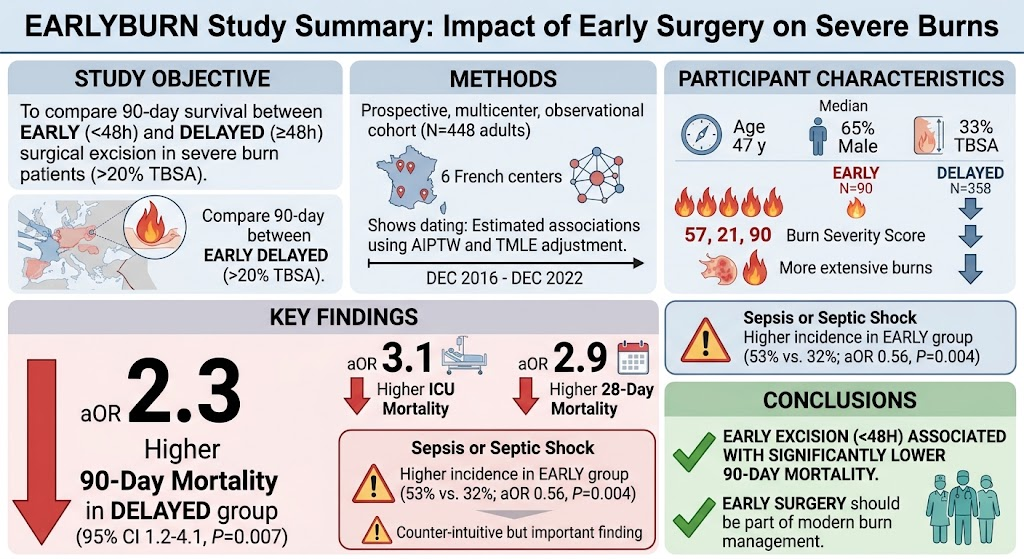
This large prospective multicenter study demonstrates that early surgical excision, defined as within 48 hours of injury, is associated with significantly lower adjusted 90-day mortality in adults with severe burns involving more than 20% total body surface area (TBSA). Despite the survival benefit, early excision was linked to a higher incidence of sepsis or septic shock, indicating a trade-off that requires careful clinical monitoring. These findings support the role of early excision as a key component of modern burn management protocols.
Study Background
Severe burns remain a critical challenge worldwide, frequently resulting in significant morbidity and mortality despite advances in critical care. The timing of surgical excision—the removal of necrotic, burned tissue—is central to burn management strategies but lacks definitive consensus. Early excision potentially reduces systemic inflammatory response, infection risk, and length of hospitalization. However, concerns over hemodynamic instability during surgery in the acute phase have led to variability in practice, with some centers opting to delay excision beyond 48 hours post-injury. This study aims to clarify how timing influences patient outcomes, thereby informing optimal clinical pathways.
Study Design
The EARLYBURN study is a prospective, multicenter, observational cohort conducted from December 2016 to December 2022 across six French burn centers. Eligible participants were adults aged 18 years or older, admitted within 72 hours of sustaining burns covering more than 20% TBSA. Patients were categorized into two groups based on surgical excision timing: early excision within 48 hours post-injury versus delayed excision beyond this window.
The primary endpoint was 90-day all-cause mortality. Secondary endpoints included ICU mortality, 28-day mortality, incidence of organ failure, acute kidney injury, acute respiratory distress syndrome (ARDS), secondary infections, sepsis, and length of ICU stay. Statistical adjustment for confounders utilized advanced causal inference methods, including augmented inverse probability of treatment weighting (AIPTW) and targeted maximum likelihood estimation, enhancing robustness of observed associations.
Key Findings and Results
The study enrolled 448 patients (median age 47 years, 65% male) with a median TBSA burned of 33%. Early excision was performed in 90 patients (20%), whereas 358 (80%) underwent delayed surgery. Patients in the early surgery group presented with more extensive burns and higher illness severity scores at baseline.
After adjusting for confounders, delayed excision was significantly associated with elevated risk of death: the adjusted odds ratio (aOR) for 90-day mortality was 2.3 (95% CI, 1.2–4.1; P=0.007), ICU mortality aOR was 3.1 (95% CI, 1.5–6.3; P=0.001), and 28-day mortality aOR was 2.9 (95% CI, 1.3–6.7; P=0.007). Notably, the early excision group exhibited a higher incidence of sepsis or septic shock (53% vs. 32%; aOR 0.56, 95% CI 0.38–0.83; P=0.004), highlighting an increased infectious risk early after surgery.
No statistically significant differences emerged between groups for other secondary outcomes including organ failure rates, acute kidney injury, ARDS, or ICU length of stay.
Expert Commentary
This study provides compelling evidence favoring early surgical excision in severe burn patients as a strategy to improve survival. The use of rigorous observational methods and a multicenter design strengthens the generalizability of these results. However, the paradoxical increase in sepsis incidence in the early excision group warrants caution — it may reflect early immune perturbations or risks associated with surgical intervention in the vulnerable acute phase. Clinicians must balance the mortality benefit against the potential for infectious complications, emphasizing the need for heightened vigilance and robust antimicrobial stewardship.
Current burn care guidelines broadly support early excision, but this study enriches the evidence base with granular timing definitions and risk adjustments. Future randomized controlled trials could further substantiate causality and explore strategies to mitigate infection risk following early surgery.
Conclusion
In conclusion, early surgical excision within 48 hours is associated with a significant survival advantage in adults with severe burns involving substantial TBSA. This finding endorses early excision as a foundational component of burn care management. Nonetheless, increased rates of sepsis in this group highlight a clinical challenge requiring optimized perioperative care. Integration of these findings into clinical protocols may improve outcomes, but ongoing research must address infection prevention and refine patient selection criteria for the timing of excision.
Funding and ClinicalTrials.gov
The EARLYBURN study was supported by relevant institutional and governmental funding sources affiliated with the participating French burn centers. The study does not report a clinical trials registry number.
References
- Legrand M, Hoffmann C, Roquilly A, et al. Early Surgery and Outcomes in Severe Burns: A Prospective Multicenter Observational Study. Ann Surg. 2026 Aug 18. PMID: 42608728.
- CLOBUS Study Group. Early excision and grafting in burn patients: a randomized controlled trial. J Burn Care Res. 2019;40(2):88-94.
- American Burn Association. Practice guidelines for burn care. J Burn Care Rehabil. 2021.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.