Introduction: The Evolving Landscape of Genetic Cardiomyopathy
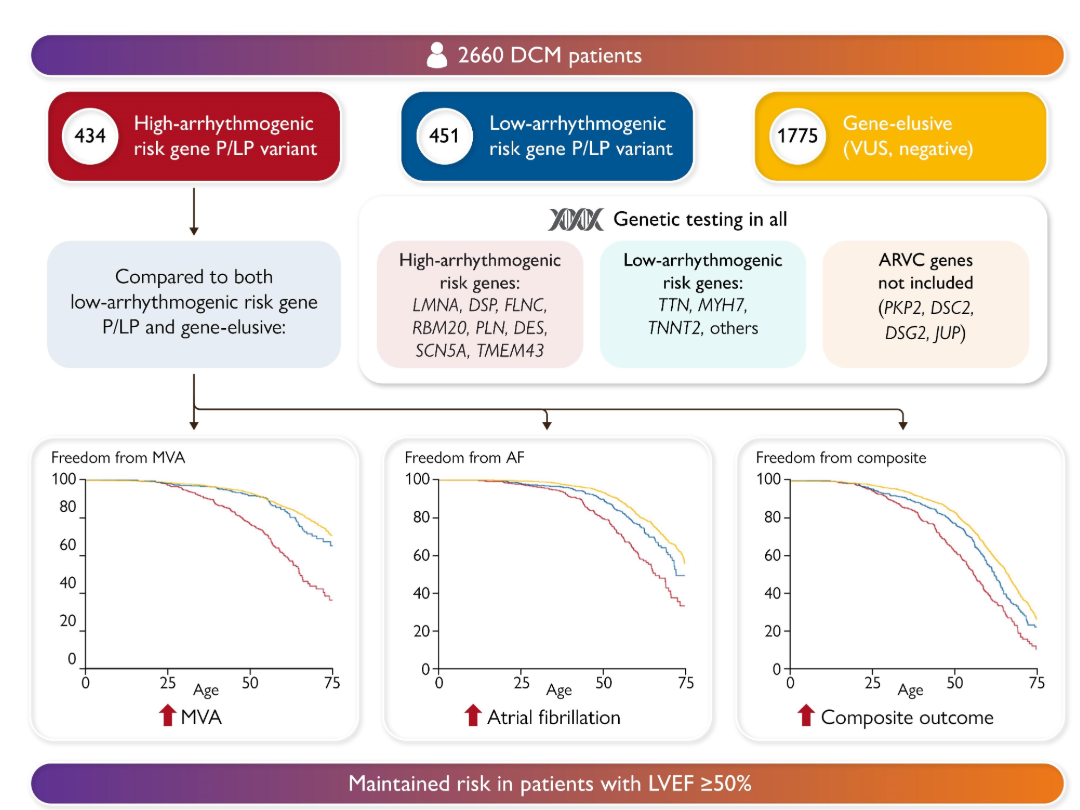
The clinical management of dilated cardiomyopathy (DCM) has undergone a profound transformation over the last decade. Once viewed as a monolithic condition characterized by left ventricular dilation and systolic dysfunction of unknown or varied etiology, DCM is now increasingly understood through the lens of precision medicine. Genetic testing has emerged as a cornerstone of diagnosis, revealing that up to 40% of cases have an identifiable genetic basis. Traditionally, certain genotypes—such as those involving LMNA, FLNC, and desmosomal genes—have been labeled as ‘arrhythmic’ due to their strong association with sudden cardiac death (SCD) and malignant ventricular arrhythmias (MVA). However, a critical question remained: do these genetic variants also predispose patients to more aggressive ‘pump failure’ or advanced heart failure (AHF)?
A Shift in Prognostic Focus
Recent data, most notably from a large-scale multicenter study in Spain, suggest that the distinction between ‘arrhythmic’ and ‘mechanical’ genotypes may be less rigid than previously thought. The study by Mora-Ayestarán and colleagues provide compelling evidence that high-risk arrhythmic genotypes are not only predictors of electrical instability but also primary drivers of progressive myocardial failure requiring advanced interventions like heart transplantation or ventricular assist device (VAD) implantation.
Highlights of the Research
The findings from this extensive cohort study provide several key insights for the modern clinician:
Dual Risk Profile
Patients harboring high-risk arrhythmic genotypes (LMNA, FLNC, desmosomal genes, PLN, TMEM43, RBM20) face a nearly twofold increase in the risk of advanced heart failure events compared to those with other genotypes or genotype-negative DCM.
Independent Predictors
Genotype emerged as the most significant independent predictor of AHF, even when accounting for traditional clinical markers such as left ventricular ejection fraction (LVEF) and New York Heart Association (NYHA) functional class.
Synergy with Imaging
The presence of late gadolinium enhancement (LGE) on cardiac MRI, combined with a high-risk genotype, provides the most robust risk stratification for malignant ventricular arrhythmias, underscoring the importance of multimodal assessment.
Study Design and Methodology
The study involved a comprehensive analysis of 1,203 genotyped DCM patients across 19 specialized centers in Spain. This represents one of the largest and most geographically diverse cohorts dedicated to understanding the intersection of genetics and heart failure progression.
Patient Classification
To provide granular data, researchers categorized patients into four distinct groups:
1. High-Risk Arrhythmic Genotypes
This group included variants in LMNA, FLNC (truncating), desmosomal genes (PKP2, DSP, DSG2, DSC2), PLN, TMEM43, and RBM20. These genes are historically associated with high rates of SCD.
2. Titin (TTN) Variants
Truncating variants in TTN are the most common genetic cause of DCM, typically associated with a more favorable response to medical therapy but a persistent risk of remodeling.
3. Other Genes
Variants in less common or lower-penetrance genes.
4. Genotype Negative (Gen-)
Patients with no identifiable pathogenic or likely pathogenic variants.
Endpoints
The primary endpoint was a composite of advanced heart failure (AHF) events: heart transplant, VAD implantation, and AHF-related mortality. The secondary endpoint focused on malignant ventricular arrhythmias (MVA), including sustained ventricular tachycardia, ventricular fibrillation, and appropriate ICD shocks.
Key Findings: The Genetic Burden of Pump Failure
The results of the study, following a median follow-up of 5.7 years, provide a stark look at the natural history of genetically defined DCM.
Advanced Heart Failure Outcomes
The incidence of AHF events was markedly higher in the high-risk arrhythmic group (24.3%) compared to the TTN group (13.0%) and the Gen- group (10.1%). The hazard ratio (HR) for high-risk arrhythmic genes was 1.85 (95% CI 1.31-2.61) when compared to all other groups combined. This suggests that the same molecular pathways leading to electrical dysfunction—such as nuclear envelope instability in LMNA or cytoskeletal disruption in FLNC—also accelerate the progression of myocardial fibrosis and contractile failure.
Malignant Ventricular Arrhythmias
Consistent with previous literature, the high-risk group also experienced significantly more MVA events (29.7%) compared to the rest of the cohort (HR 2.52; 95% CI 1.81-3.51). Interestingly, while the high-risk genotype was the strongest predictor for AHF, both the genotype and the presence of LGE on MRI were necessary to accurately predict MVA, suggesting that structural scarring is a final common pathway for arrhythmia across different genetic backgrounds.
Expert Commentary and Clinical Implications
The implications of this study for clinical practice are significant. We are moving away from a ‘one-size-fits-all’ approach to heart failure management.
Personalized Surveillance
For clinicians, identifying a high-risk arrhythmic genotype should trigger more than just a discussion about an implantable cardioverter-defibrillator (ICD). It necessitates a more aggressive surveillance strategy for heart failure progression. Patients with LMNA or RBM20 mutations, for instance, may need more frequent echocardiographic or MRI monitoring and earlier referral to advanced heart failure specialists.
Therapeutic Approaches
The study supports the idea that ‘arrhythmic’ genes are, in fact, ‘progressive cardiomyopathy’ genes. This may influence the timing of guideline-directed medical therapy (GDMT) optimization. While current guidelines prioritize LVEF <35% for many interventions, genetic data might eventually support earlier pharmacological or device-based interventions in high-risk carriers before they reach traditional thresholds of dysfunction.
Biological Plausibility
Why do these specific genes lead to worse heart failure? In the case of LMNA, the disruption of the nuclear lamina leads to increased sensitivity to mechanical stress and altered gene expression. In RBM20-related DCM, abnormal splicing of titin and other sarcomeric proteins leads to a particularly stiff and dysfunctional myocardium. These molecular mechanisms explain why the clinical course is more aggressive than that of idiopathic or titin-related DCM.
Study Limitations
While robust, the study has limitations. As an observational cohort, there is inherent selection bias, as patients referred for genetic testing at specialized centers may represent a more severe spectrum of the disease. Furthermore, while ‘high-risk’ genes were grouped, individual genes within that group (e.g., LMNA vs. PKP2) carry different phenotypic nuances that require further large-scale sub-analysis.
Conclusion: A New Chapter in DCM Management
The findings by Mora-Ayestarán et al. reinforce the necessity of genetic testing in the evaluation of dilated cardiomyopathy. By identifying patients with high-risk arrhythmic genotypes, clinicians can better predict not only the risk of sudden death but also the trajectory toward advanced heart failure. This dual-risk profile demands a comprehensive therapeutic approach that balances the prevention of arrhythmia with the proactive management of pump failure. As our understanding of genotype-phenotype correlations deepens, the integration of genetic data into routine clinical decision-making will be essential for improving long-term outcomes in this vulnerable patient population.
References
1. Mora-Ayestarán N, et al. Arrhythmic genotypes in dilated cardiomyopathy and risk of advanced heart failure. Eur Heart J. 2025;46(48):5222-5233.
2. Hershberger RE, et al. Genetic evaluation of cardiomyopathy: a clinical practice resource. Genet Med. 2018;20(9):899-909.
3. Gigli M, et al. Genetic Risk of Arrhythmic Phenotypes in Dilated Cardiomyopathy. J Am Coll Cardiol. 2019;74(11):1480-1490.