Introduction
Functional hypothalamic amenorrhea (FHA) is a condition characterized by the absence or irregularity of menstrual periods due to a disruption in the hypothalamic-pituitary-ovarian axis without underlying organic pathology. This often arises from stress, excessive exercise, or low body weight. While menstrual irregularities have long been recognized as associated with cardiovascular disease (CVD), the specific FHA phenotype has not been separately studied for its impact on cardiovascular and cardiometabolic risk profiles. This article explores the association between FHA and incident cardiovascular disease and cardiometabolic risk factors over a long-term prospective cohort study.
Background and Rationale
Menstrual cycles reflect the complex interplay of reproductive hormones and overall metabolic health. Irregularities can signal underlying dysfunction affecting systems beyond reproduction, including cardiovascular regulation. Prior studies have linked polycystic ovarian syndrome (PCOS) and other menstrual disorders with elevated risks of hypertension, dyslipidemia, diabetes, and CVD. However, FHA, differing by its etiopathogenesis—stress and energy deficiency rather than hormonal excess—requires distinct consideration.
Understanding FHA’s cardiovascular implications is critical since it predominantly affects premenopausal women, potentially indicating early cardiometabolic risk. Investigating FHA’s distinct risk profile aids clinicians in identifying at-risk individuals for timely intervention and customized preventive strategies.
Study Design and Methods
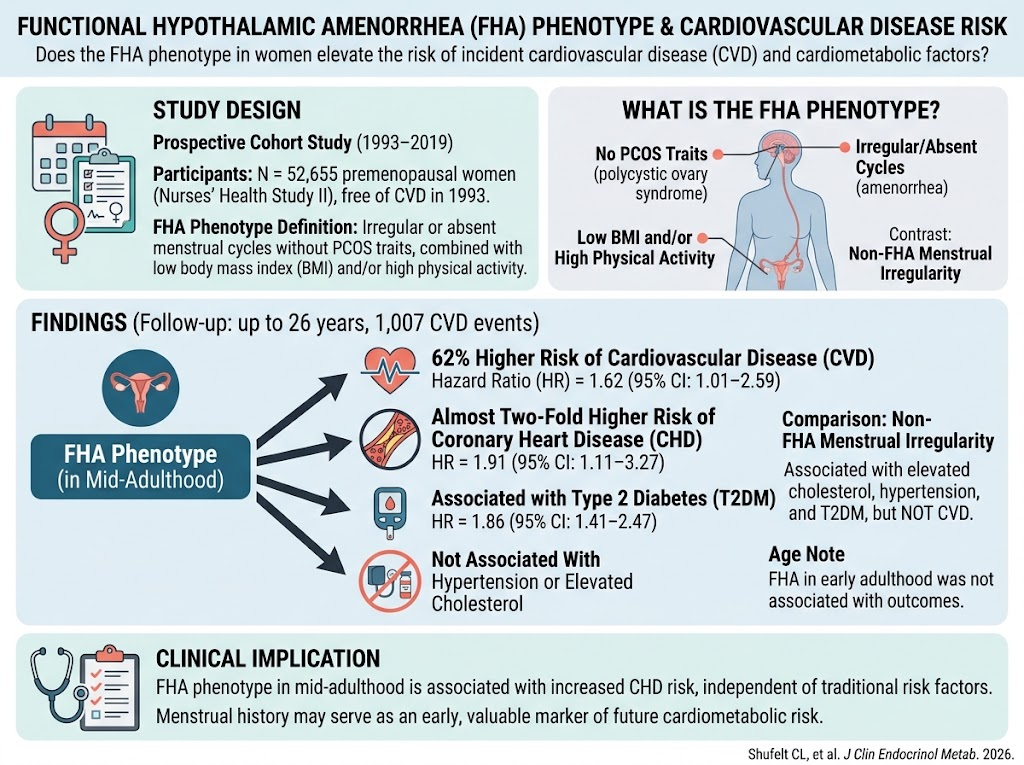
The analysis utilized data from the Nurses’ Health Study II, initiated in 1993 with biennial follow-ups through 2019, comprising 52,655 premenopausal women free of CVD at baseline. FHA phenotype classification required menstrual irregularity or absence without traits of PCOS, coupled with indicators of low body mass index (BMI) and/or high physical activity levels. This delineation helped isolate FHA from other menstrual disorders.
Incident cardiovascular events tracked included coronary heart disease (CHD), defined by myocardial infarction or coronary revascularization procedures, and stroke. Cardiometabolic outcomes assessed were the new onset of hypertension, elevated cholesterol, and type 2 diabetes mellitus (T2DM).
Key Findings
Over up to 26 years of follow-up, 1,007 cases of CVD were documented. Among women developing CVD, the median latency to first event was 17 years. Mid-adulthood FHA was linked to a 62% increased risk of total CVD compared to women with regular menstrual cycles. This association was primarily driven by an almost two-fold rise in risk of CHD (hazard ratio [HR] = 1.91).
Additionally, FHA was significantly associated with the development of T2DM (HR = 1.86) but showed no meaningful association with hypertension or elevated cholesterol. In contrast, menstrual irregularities not fulfilling FHA criteria correlated with increased risk of hypertension, elevated cholesterol, and T2DM, but not CVD. Importantly, FHA in early adulthood did not show significant associations with these outcomes.
Interpretation of Results
The findings indicate that FHA in mid-adulthood constitutes an independent cardiovascular risk phenotype, especially for CHD, distinct from other menstrual irregularities. The lack of association between FHA and traditional cardiovascular risk factors such as hypertension and elevated cholesterol suggests alternate pathogenic pathways, possibly related to neuroendocrine dysfunction, energy deficiency, or chronic stress responses.
The relationship with T2DM aligns with the metabolic sequelae seen in FHA, such as impaired glucose metabolism and insulin sensitivity alterations. These results underline the importance of menstrual history as an early, non-invasive indicator for future cardiometabolic risk screening and prevention.
Clinical Implications
Healthcare providers should consider FHA phenotype in women presenting with menstrual irregularities, especially when accompanied by low BMI and high physical activity. Recognition of FHA as a marker for long-term cardiovascular risk may prompt earlier lifestyle assessment, metabolic screening, and intervention aimed at mitigating CHD and diabetes risk.
Interventions may involve addressing underlying causes such as nutritional optimization, stress management, and balanced physical activity. In some cases, adjunctive hormonal therapies could be explored to restore menstrual function and potentially modulate cardiovascular risk factors.
Limitations and Future Directions
While the large cohort and extended follow-up enhance the study’s strengths, limitations include reliance on self-reported menstrual cycle characteristics and potential residual confounding factors such as diet and psychosocial variables. Further research is needed to elucidate the biological mechanisms linking FHA and cardiovascular outcomes and to evaluate targeted prevention strategies.
Additionally, studies exploring the impact of FHA treatment on cardiovascular risk modulation would be valuable.
Conclusion
Functional hypothalamic amenorrhea in mid-adulthood is independently associated with increased risk of coronary heart disease and type 2 diabetes, identifying it as a distinct phenotype within menstrual irregularities with important cardiometabolic implications. Incorporating menstrual history into cardiovascular risk assessment enhances early detection and prevention opportunities in premenopausal women.
This knowledge stresses the integral link between reproductive health and long-term cardiovascular wellness, advocating for multidisciplinary approaches in women’s healthcare.
Reference
Shufelt CL, Stuart JJ, Karam J, Che X, Manson JE, Miller KK, Rexrode K, Faubion S, Berga S, Bairey Merz CN, Rich-Edwards JW. Functional Hypothalamic Amenorrhea Phenotype and Cardiovascular Disease Risk. J Clin Endocrinol Metab. 2026 Oct 5:dgag405. doi: 10.1210/clinem/dgag405. Epub ahead of print. PMID: 42831273.