From Pressure Metrics to Personalized Prognosis: Transforming Risk Assessment in Advanced Chronic Liver Disease
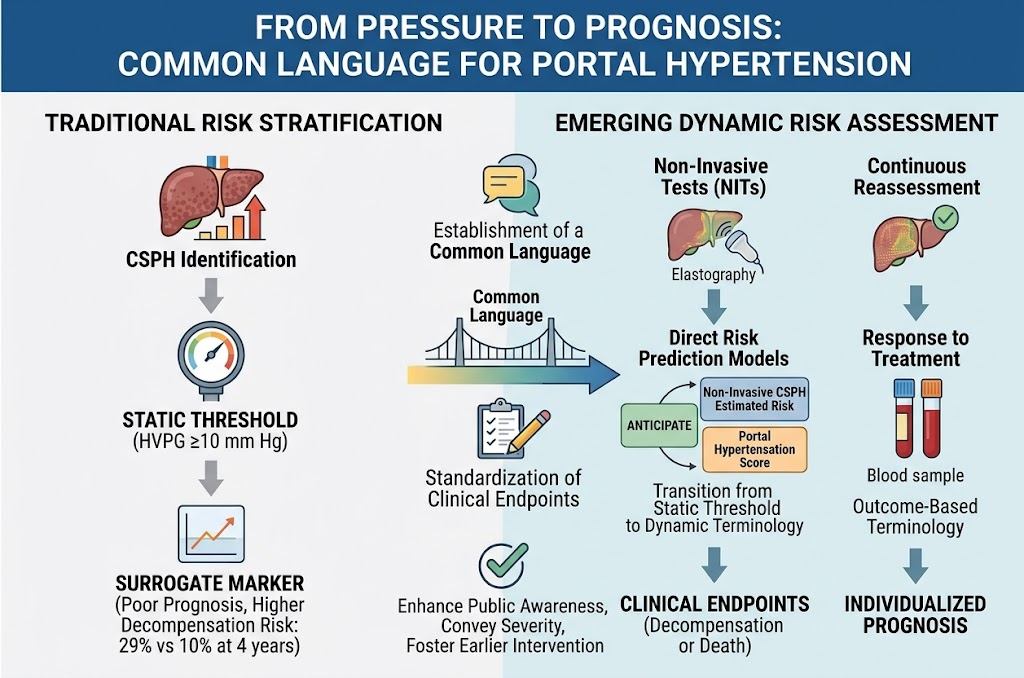
Highlight
1. Clinically significant portal hypertension (CSPH), traditionally defined by a hepatic venous pressure gradient (HVPG) ≥10 mm Hg, remains a robust predictor of decompensation risk in advanced chronic liver disease (ACLD).
2. Non-invasive tests (NITs), including elastography and validated scoring systems, now demonstrate prognostic accuracy comparable to HVPG for predicting liver-related decompensation and mortality.
3. Transitioning from static hemodynamic thresholds to dynamic, individualized risk assessment with NITs can enhance patient monitoring, guide therapeutic interventions, and tailor surveillance strategies.
4. Standardization of clinical endpoints focusing on meaningful decompensation events is essential to facilitate wider adoption of NIT-based prognostic models in clinical practice.
Background: Clinical Context and Disease Burden
Advanced chronic liver disease (ACLD) encompasses a spectrum of hepatic pathologies characterized by fibrosis progression culminating in cirrhosis, portal hypertension, and increased risk of clinical decompensation. Portal hypertension, quantified by the hepatic venous pressure gradient (HVPG), results from increased intrahepatic resistance and augmented portal blood flow, contributing significantly to morbidity and mortality in these patients. The identification of clinically significant portal hypertension (CSPH), defined by HVPG ≥10 mm Hg, has historically enabled stratification of compensated patients at higher risk of progression to decompensation, defined by ascites, variceal hemorrhage, encephalopathy, or jaundice.
However, HVPG measurement requires invasive catheterization, limiting accessibility and repeated assessments. This constraint hinders dynamic risk stratification and timely treatment adjustments. Furthermore, reliance on a single static HVPG cutoff inadequately reflects the complex and individualized course of ACLD. Hence, there is an unmet clinical need for practical, non-invasive, and longitudinal risk prediction methods that forecast patient-relevant clinical outcomes, including liver decompensation and liver-related mortality.
Study Design and Methodological Overview
The accumulating evidence reviewed by Jeffrey et al. (2026) integrates cohort data and prognostic modeling studies assessing the role of non-invasive tests (NITs) as surrogates for CSPH and direct predictors of clinically meaningful endpoints. The key NIT modalities include transient elastography measuring liver stiffness, as well as composite blood-based scores such as the Portal Hypertension Decompensation Score. Models like ANTICIPATE and the Non-Invasive CSPH Estimated Risk combine demographic, laboratory, and elastographic data to refine individual risk estimations.
Studies primarily enrolled patients with compensated ACLD of various etiologies and evaluated the predictive performance of NITs against HVPG and clinical endpoints over longitudinal follow-up periods, typically up to 4 years. The endpoints of interest included first liver decompensation events and liver-related death, with standardized definitions focusing on portal hypertension-driven complications.
Key Findings and Interpretation
The body of evidence substantiates that CSPH measured by HVPG ≥10 mm Hg predicts approximately a 29% risk of decompensation at 4 years versus 10% in those without CSPH, confirming its prognostic robustness. Significantly, non-invasive markers such as liver stiffness measurements and integrated risk scores exhibit comparable accuracy in predicting decompensation risk. For instance, the ANTICIPATE model and Portal Hypertension Decompensation Score deliver risk stratification performance metrics—such as area under the receiver operating characteristic curves (AUROC)—on par with invasive pressure measurements.
Beyond static diagnostic thresholds, NITs enable continuous and longitudinal reassessment of portal hypertension severity and response to disease-modifying therapies, such as non-selective beta-blockers, antivirals, or antifibrotic agents. This dynamic evaluation supports personalized clinical decisions and proactive management strategies, facilitating earlier interventions that may alter the trajectory of the disease.
Importantly, the adoption of clinical endpoints directly tied to patients’ outcomes—rather than surrogate markers or heterogeneous composite endpoints—helps clarify prognostic communication and enhances clinical trial design and health policy frameworks.
Expert Commentary
Jeffrey et al. advocate a paradigm shift from reliance on invasive, static hemodynamic thresholds to embracing non-invasive, outcome-driven risk models. This aligns with evolving hepatology guidelines emphasizing patient-centered approaches. Some experts highlight the need for harmonized endpoint definitions, wider validation of prognostic models across diverse populations, and integration with digital health platforms for real-time risk monitoring.
Limitations of current NITs include false positives influenced by inflammation or cholestasis and varying performance across liver disease etiologies. Despite these challenges, the biological plausibility underpinning elastography’s reflection of fibrosis and portal pressure supports their clinical utility.
Conclusion
Transitioning portal hypertension assessment from invasive pressure metrics to non-invasive, personalized prognostic models represents a major advance in managing patients with advanced chronic liver disease. Non-invasive tests enable dynamic risk stratification predictive of clinically meaningful decompensation and mortality endpoints, supporting earlier and more precise clinical interventions. For widespread clinical uptake, future research must focus on standardizing outcome definitions, validating models in real-world cohorts, and aligning terminology with patient-centered outcomes to improve disease awareness and timely care. This evolving approach promises to enhance prognosis communication, optimize therapy, and ultimately improve patient outcomes in ACLD.
Funding and ClinicalTrials.gov
No specific funding or clinical trial registry details were reported in the source article.
References
1. Jeffrey AW, Tsochatzis EA, Genescà J, Adams LA, Wallace MC, Jeffrey GP, Majumdar A. From pressure to prognosis: establishing a common language for portal hypertension in advanced chronic liver disease. Gut. 2026 Aug 25. doi: 10.1136/gutjnl-2025-XXXXX. PMID: 42642217.
2. Garcia-Tsao G, Abraldes JG, Berzigotti A, Bosch J. Portal hypertensive bleeding in cirrhosis: Risk stratification, diagnosis, and management: 2016 practice guidance by the American Association for the Study of Liver Diseases. Hepatology. 2017;65(1):310-335.
3. Baveno VI Faculty. Expanding consensus in portal hypertension: Report of the Baveno VI Consensus Workshop: Stratifying risk and individualizing care for portal hypertension. J Hepatol. 2015;63(3):743-752.
4. Berzigotti A, Bosch J. Non-invasive tools for diagnosis and monitoring of portal hypertension. Clin Liver Dis (Hoboken). 2015;6(4):87-90.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.