Evolving Impact of Implantable Cardioverter-Defibrillators on Mortality Post-Myocardial Infarction: Insights from the PROFID Study
Highlight
- Primary prevention ICD therapy was initially shown to halve mortality in patients with reduced left ventricular ejection fraction (LVEF) after myocardial infarction (MI).
- The large PROFESSIONAL FIbrillation Defibrillator (PROFID) pooled cohort analysis evaluated 32,214 post-MI patients over 25 years to assess temporal trends in ICD benefit.
- Mortality reduction associated with ICD use has decreased progressively from 1995 to 2020, becoming statistically nonsignificant in the latest decade.
- This trend reflects evolving MI and heart failure management and prompts reconsideration of ICD implantation criteria in modern practice.
Study Background
The introduction of primary prevention implantable cardioverter-defibrillators (ICDs) transformed the management of patients at risk for sudden cardiac death (SCD), particularly post-myocardial infarction survivors with significantly reduced left ventricular ejection fraction (LVEF ≤35%). Multiple landmark randomized controlled trials (RCTs) conducted in the early 2000s firmly established the survival benefit of ICDs in this population by reducing arrhythmic mortality. However, substantial advances in the medical treatment of myocardial infarction and heart failure over the past two decades—including widespread statin use, modern revascularization techniques, improved heart failure pharmacotherapy (such as angiotensin receptor-neprilysin inhibitors and sodium-glucose co-transporter-2 inhibitors), and optimized device therapy—have improved overall prognoses. This evolving therapeutic landscape raises the question of whether the relative mortality benefit conferred by primary prevention ICD implantation remains as robust today as when the original trials were conducted.
Study Design
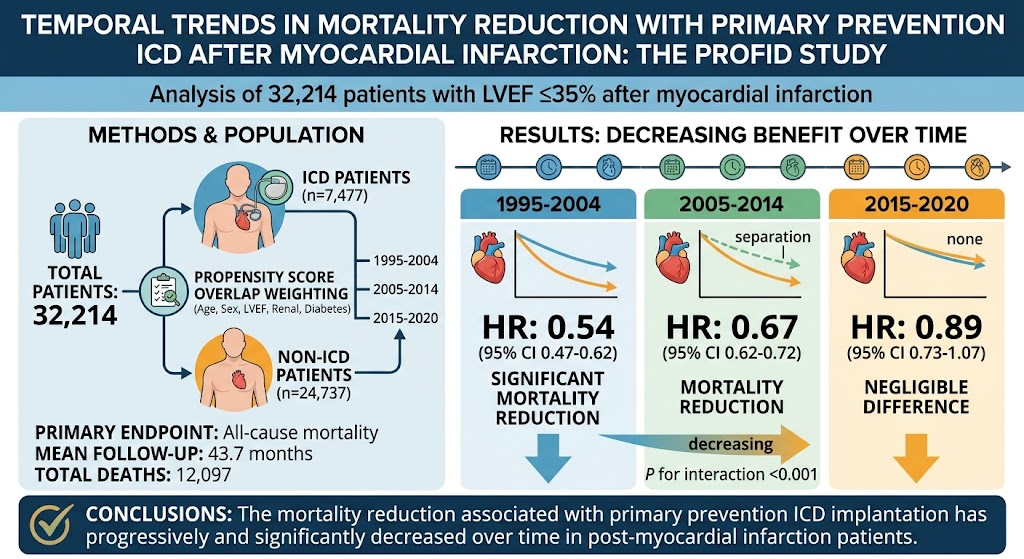
The PROFID study leveraged a large-scale, individual participant data meta-analysis combining 32,214 post-MI patients with LVEF ≤35% from multiple cohorts and registries spanning 1995 to 2020. Among these, 7,477 patients had received a primary prevention ICD, and 24,737 had not. Patients were categorized by their enrollment period into three distinct eras: 1995–2004, 2005–2014, and 2015–2020, reflecting temporal phases in cardiac care evolution.
The primary endpoint was all-cause mortality assessed during a mean follow-up of approximately 44 months. To minimize confounding by indication and imbalance, propensity scores incorporating key covariates (age, sex, LVEF, renal function, diabetes) were calculated using multivariable logistic regression. Overlap weighting was applied to achieve balanced comparison groups within each time frame. Weighted cumulative mortality curves and Cox proportional hazards models with interaction terms evaluated temporal variations in the survival benefit associated with ICD implantation.
Key Findings
Throughout the total study population, 12,097 deaths occurred. Crucially, the magnitude of mortality reduction linked to ICD therapy varied significantly by time period (P for interaction <0.001). The hazard ratios (HRs) for death comparing ICD recipients to non-ICD cohorts were:
- 1995–2004: HR 0.54 (95% CI 0.47–0.62; P <0.001), indicating a 46% relative risk reduction
- 2005–2014: HR 0.67 (95% CI 0.62–0.72; P <0.001), a 33% relative risk reduction
- 2015–2020: HR 0.89 (95% CI 0.73–1.07; P =0.221), a nonsignificant 11% relative risk reduction
Graphically, the weighted cumulative mortality curves for ICD and non-ICD patients showed considerable separation in the earliest era, diminished separation in the intermediate era, and negligible divergence in the most recent timeframe.
These findings suggest that the survival advantage provided by ICD implantation after MI has progressively attenuated over the last 25 years, paralleling improvements in overall cardiac care.
Expert Commentary
The PROFID study’s comprehensive temporal analysis underscores an important shift in the risk-benefit ratio for primary prevention ICD therapy in the contemporary era. While early trials convincingly demonstrated ICD efficacy in reducing sudden cardiac death, modern multi-faceted treatment regimens have improved baseline mortality and possibly reduced arrhythmic events that ICDs aim to prevent. Additionally, better patient selection and management of arrhythmogenic substrates may have contributed to the observed trend.
Limitations include potential residual confounding despite propensity methods, heterogeneity in cohort sources, and unmeasured variables such as medication adherence or evolving ICD technologies. Importantly, this study does not diminish the need for individualized risk stratification but advocates reconsideration of current ICD implantation criteria considering contemporary clinical realities.
Guidelines recommend ICD implantation primarily based on LVEF thresholds and time from myocardial infarction. Incorporation of new risk markers and personalized approaches might further optimize benefit-risk balances. The findings also prompt exploration of alternative preventive strategies and highlight the dynamic nature of evidence in cardiovascular device therapy.
Conclusion
In summary, the PROFID study reveals a concerning temporal decline in the mortality reduction associated with primary prevention ICD implantation after myocardial infarction in patients with reduced LVEF. This attenuation likely reflects advances in medical and interventional management that have improved overall survival and lowered arrhythmic risks. Clinicians and guideline developers should urgently consider these trends to refine ICD deployment strategies, ensuring maximal benefit in contemporary patients while avoiding unnecessary procedural risks and healthcare costs. Future research should focus on refined risk stratification, novel biomarkers, and tailored therapies to optimize sudden death prevention in this evolving landscape.
Funding and Registration
Details regarding funding sources and clinical trial registration for the pooled data were not explicitly detailed in the published summary but typically involve collaborative research networks and may be found in the original PROFID study documentation.
References
1. Sepehri Shamloo A, Chiba T, Tijssen JGP, et al. Mortality reduction with implanted defibrillator for primary prevention of sudden death after Myocardial Infarction: temporal trends in the PROFID study. Eur Heart J. 2026 Aug 28. PMID: 42663237.
2. Bardy GH, Lee KL, Mark DB, et al. Amiodarone or an implantable cardioverter-defibrillator for congestive heart failure. N Engl J Med. 2005;352(3):225-237.
3. Moss AJ, Hall WJ, Cannom DS, et al. Cardiac-Resynchronization Therapy for the Prevention of Heart-Failure Events. N Engl J Med. 2009;361(14):1329-1338.
4. Priori SG, Blomström-Lundqvist C, Mazzanti A, et al. 2015 ESC Guidelines for the management of patients with ventricular arrhythmias and the prevention of sudden cardiac death. Eur Heart J. 2015;36(41):2793-2867.
5. Zipes DP, Camm AJ, Borggrefe M, et al. ACC/AHA/ESC 2006 Guidelines for management of patients with ventricular arrhythmias and the prevention of sudden cardiac death. Circulation. 2006;114:e385–e484.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.