Patient Information
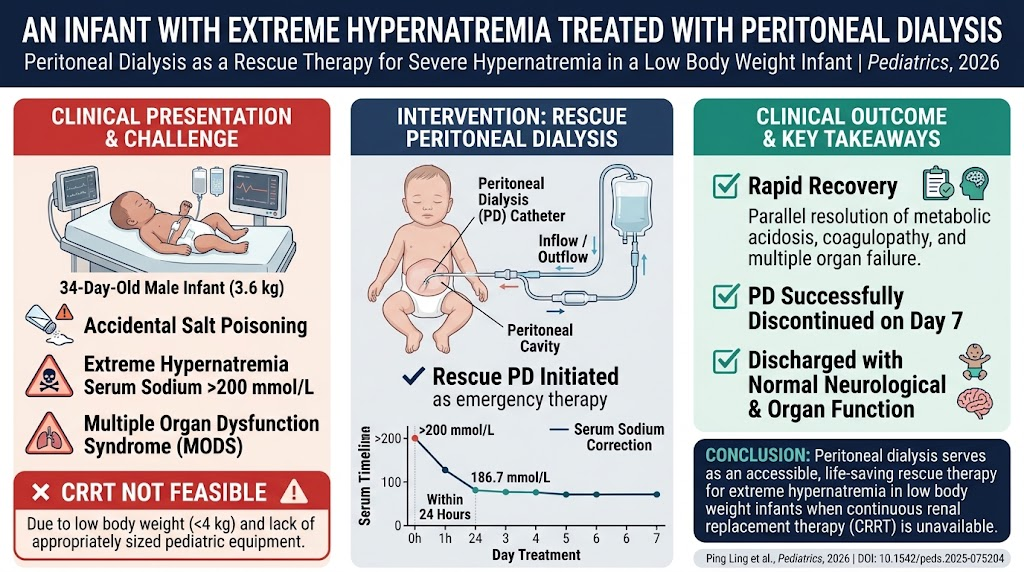
A 34-day-old male infant, weighing 3.6 kilograms, was admitted with lethargy, poor feeding, and seizures. The infant had no significant prenatal or perinatal complications, and was exclusively breastfed up to admission. There was no prior illness reported. According to family history, the infant had accidental ingestion of a hyperosmolar sodium-containing substance (suspected salt poisoning) at home.
Diagnosis
Initial laboratory investigations revealed extreme hypernatremia with serum sodium levels exceeding 200 mmol/L, markedly above the normal newborn range (135–145 mmol/L). The patient also demonstrated evidence of metabolic acidosis, coagulopathy, and signs of multiple organ dysfunction syndrome (MODS), including impaired renal function and altered coagulation profiles. Given the clinical context of accidental salt ingestion and laboratory abnormalities, a diagnosis of extreme hypernatremia secondary to acute salt poisoning was established.
Differential Diagnosis
Other causes considered included:
– Dehydration due to inadequate fluid intake or diarrhea: Ruled out because of acute onset and hypernatremia severity inconsistent with typical dehydration.
– Diabetes insipidus: Unlikely due to additional signs of salt poisoning and ingestion history.
– Hypernatremic dehydration associated with sepsis: No infectious source was identified.
– Iatrogenic hypernatremia: No history of inappropriate sodium administration in hospital.
Treatment and Management
Initial management focused on stabilizing airway, breathing, and circulation, controlling seizures, and correcting fluid and electrolyte disturbances cautiously to prevent cerebral edema. Attempts to initiate continuous renal replacement therapy (CRRT) were unsuccessful due to the patient’s low body weight and the lack of appropriately sized vascular access devices and equipment.
As an alternative, peritoneal dialysis (PD) was instituted as rescue therapy to rapidly reduce serum sodium and remove excess salt, given the patient’s critical condition and logistic limitations. PD was performed using a standard protocol tailored for neonatal patients, with close monitoring of serum electrolytes, acid-base balance, fluid status, and coagulation parameters.
Within 24 hours of initiating PD, serum sodium decreased substantially to 186.7 mmol/L. Concurrently, metabolic acidosis improved, coagulation parameters normalized, and organ function stabilized. PD continued for a total of 7 days until serum sodium levels normalized and organ function fully recovered.
Supportive care included mechanical ventilation for respiratory distress, anticonvulsants for seizure control, and correction of coagulopathy with plasma transfusions as needed.
Outcome and Prognosis
The infant ultimately recovered fully without neurological deficits. At discharge, vital signs were stable, neurological examination was normal, and laboratory values had returned to within normal limits. Follow-up showed normal growth and development, and no long-term sequelae were evident up to the last outpatient visit.
Discussion
Extreme hypernatremia with serum sodium levels exceeding 200 mmol/L is rare in infants and is associated with high mortality and morbidity. Cases linked to accidental salt poisoning are reported infrequently, and the management is challenging due to high risk of cerebral edema during sodium correction and limited therapeutic options in very low body weight infants.
Continuous renal replacement therapy (CRRT) is often preferred to gently reduce sodium concentration, but CRRT modalities require specialized equipment and vascular access that may not be feasible in neonates or infants under certain weight thresholds.
This case illustrates that peritoneal dialysis (PD) can serve as a life-saving alternative therapy in extreme hypernatremia with multiorgan dysfunction in infants, especially when CRRT is unavailable. The successful use of PD resulted in safe and effective correction of hypernatremia, improvement in metabolic disturbances, and recovery of organ function without neurologic complications.
This report contributes valuable evidence supporting PD as an option in critical care settings for neonates with electrolyte emergencies and limited resources. Careful monitoring and gradual sodium correction remain crucial to minimize cerebral edema risk, and multidisciplinary care is essential.
References
1. Moritz ML, Ayus JC. Disorders of water metabolism in the pediatric patient: hyponatremia and hypernatremia. Pediatr Clin North Am. 2001;48(3):953-68.
2. Platz J, Mechtler T, Klaushofer B, et al. Severe hypernatremia in children: is rapid correction beneficial? Pediatric Nephrology. 2017;32(12):2301-2308.
3. Hymes LC, Doraiswamy S, Pandya S. Acute salt poisoning in infants. Pediatr Emerg Care. 2018;34(6):422-424.
4. Anikina E, Brunner M, et al. Neonatal peritoneal dialysis in low birth weight infants: outcomes and technical adaptations. Perit Dial Int. 2020;40(3):281-287.
(Citation for the case report: Ling P, Tang R, Chen Y, Lin Y, Wang X, Wang S, Zhou Z. An Infant With Extreme Hypernatremia Treated With Peritoneal Dialysis. Pediatrics. 2026 Oct 7. PMID: 42839675.)