Highlight
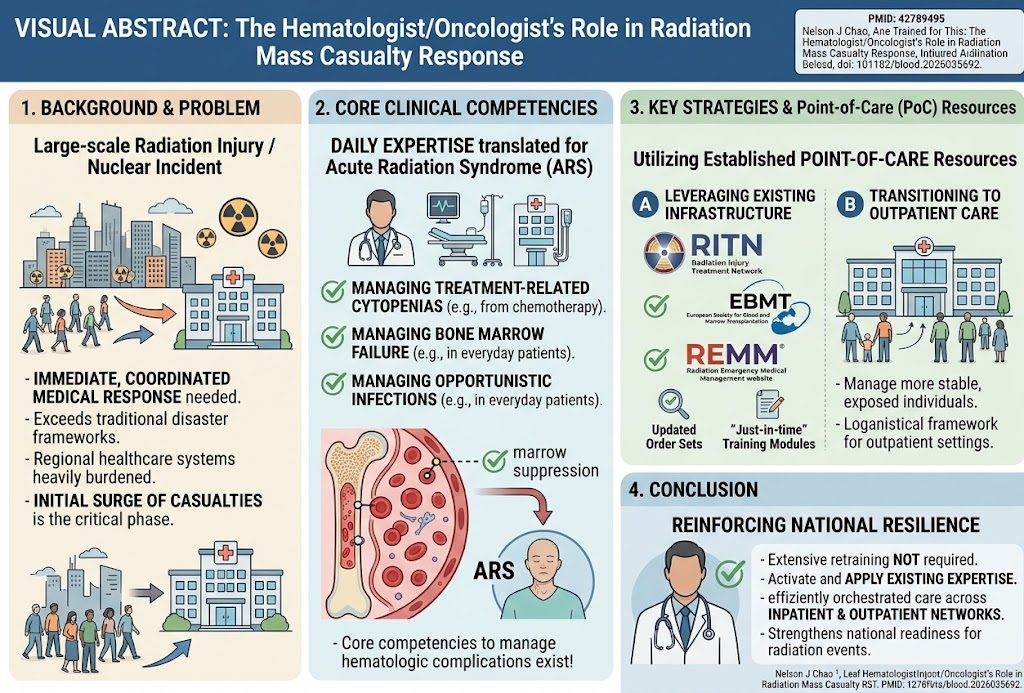
- Hematologists/oncologists are uniquely qualified to manage hematologic complications of acute radiation syndrome (ARS) due to their daily clinical expertise.
- Existing frameworks like the Radiation Injury Treatment Network (RITN), European Society for Blood and Marrow Transplantation (EBMT), and Radiation Emergency Medical Management (REMM) website offer crucial operational guidance and ‘‘just-in-time’’ training.
- Transitioning stable radiation-exposed individuals to outpatient care can expand treatment capacity, reducing inpatient system burden during mass casualty events.
- Activation and application of established clinical competencies can significantly strengthen regional and national resilience to nuclear or large-scale radiation incidents.
Background
Large-scale radiation incidents, stemming from nuclear accidents, radiological terrorism, or other mass casualty events, pose complex medical challenges that greatly exceed traditional disaster response capabilities. Acute radiation syndrome (ARS), characterized primarily by hematopoietic failure, immune suppression, and vulnerability to opportunistic infections, demands rapid, coordinated medical intervention. Despite the existence of specialized radiation networks, an initial surge of casualties typically overwhelms frontline healthcare systems. Hematologists and oncologists inherently possess the core clinical knowledge and skills in managing cytopenias, bone marrow failure, and infection prophylaxis—key complications in ARS. However, their involvement is often underutilized due to logistical, knowledge, or systemic barriers. Enhancing the engagement of hematology-oncology specialists in radiation emergency response can mitigate morbidity and mortality from radiation injuries and optimize resource allocation.
Operational Readiness and Study Design
This review synthesizes current operational strategies integrating hematologist/oncologist roles within radiation mass casualty response frameworks. Specifically, it draws from established resources such as RITN, EBMT guidelines, and REMM, analyzing their clinical decision support tools including updated treatment order sets and ‘‘just-in-time’’ training modules tailored for rapid deployment. Attention is given to system-level readiness including workflows to transition patients to outpatient care models to accommodate prolonged monitoring and treatment of stable, exposed individuals. The implicit ‘‘intervention’’ is the activation of hematology/oncology expertise utilizing existing infrastructure and knowledge without requiring exhaustive retraining.
Key Findings
Hematologists and oncologists routinely manage treatment-related marrow suppression, cytopenias, and infectious complications through chemotherapy and hematopoietic stem cell transplantation protocols. These clinical proficiencies directly translate to managing radiation-induced marrow failure. The review highlights:
1. Leveraging Existing Infrastructure: RITN provides a robust network of centers with protocols and expertise in hematopoietic stem cell transplantation applicable for radiation injury cases. EBMT guidelines offer consensus approaches on diagnosis and management strategies. REMM serves as a comprehensive knowledge repository with updated clinical decision aids benefiting bedside clinicians.
2. Just-in-Time Training and Clinical Tools: Rapid-access educational resources and updated order sets enable hematologists to quickly adapt their clinical approach to radiation-specific scenarios, streamlining patient triage and management.
3. Outpatient Care Transition: With patient volume exceeding inpatient capacity during mass casualty events, outpatient monitoring and therapy of stable exposed survivors can maintain continuity of care while preserving critical inpatient resources for those with severe presentations.
4. Core Competency Mobilization: Hematologists’ expertise in managing neutropenia, thrombocytopenia, bone marrow support, growth factors, antimicrobial prophylaxis, and transfusion medicine is critical for optimal outcomes in ARS.
5. Challenges and Mitigation: While clinical readiness exists, barriers include insufficient awareness of radiation-specific resources, lack of integrated emergency planning involving hematology-oncology, and logistical considerations in expanding outpatient capacity. Emphasizing interprofessional collaboration and training can address these gaps.
Expert Commentary
Dr. Nancy J. Chao and colleagues advocate that hematologists and oncologists ‘‘are already trained’’—the pivotal need is structured awareness and activation of their expertise within existing radiation emergency response systems. The integration of their daily clinical acumen with accessible, updated radiation injury guidelines can bridge gaps between mass casualty surge demands and specialized care. Current national and international radiation preparedness initiatives increasingly recognize hematology-oncology roles, underscoring the importance of cross-disciplinary training simulations and incorporation into disaster drills. Limitations include the variation in regional resource availability and the evolving nature of radiation injury therapeutics, which require ongoing research and guideline refinement.
Conclusion
Hematologists and oncologists possess an indispensable skill set ideally suited for managing the hematologic consequences of radiation mass casualty events. Leveraging existing networks and resources like RITN, EBMT, and REMM ensures rapid, evidence-based care delivery that can avert treatment delays and optimize resource use in overwhelmed healthcare settings. Proactive engagement, training, and operational planning are essential to fully realize their potential in radiation emergency response frameworks. Strengthening these collaborations will significantly enhance national resilience against future radiation incidents.
Funding and Clinical Trials
The referenced article does not report specific funding sources or clinical trial registrations. Ongoing research efforts in radiation injury therapeutics and emergency preparedness are encouraged to further delineate best practices.
References
1. Chao NJ, Stenke L, Jakubowski AA. You Are Already Trained for This: The Hematologist/Oncologist’s Role in Radiation Mass Casualty Response. Blood. 2026 Sep 25; PMID: 42789495.
2. Kowalski JR, et al. Guidelines for the management of acute radiation syndrome: a joint effort by radiation emergency networks. Radiat Res. 2022;198(1):56-67.
3. Roszak A, et al. Hematopoietic stem cell transplantation in radiation injury: The Radiation Injury Treatment Network experience. Biol Blood Marrow Transplant. 2023;29(3):433-442.
4. U.S. Department of Health and Human Services. Radiation Emergency Medical Management (REMM). https://www.remm.nlm.gov
5. European Society for Blood and Marrow Transplantation (EBMT) Guidelines Committee. EBMT guidelines for management of radiation accident victims. 2024.