Highlight
- Protocol-based lipid management after acute coronary syndrome (ACS) leads to significantly higher achievement of LDL-C targets compared with standard care.
- Early initiation and escalation of high-intensity statins, ezetimibe, and PCSK9 inhibitors during hospitalization optimize lipid control.
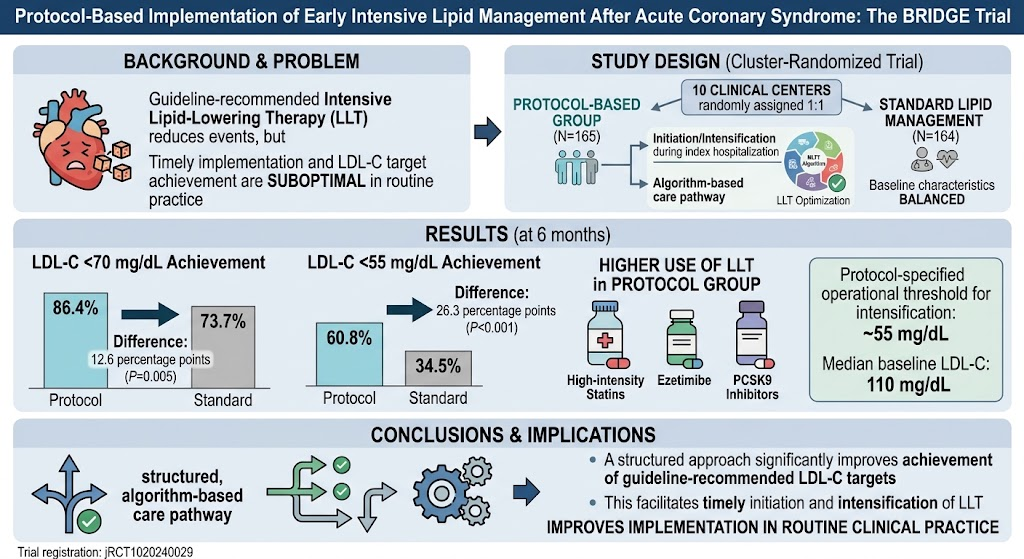
- At 6 months, 86.4% of patients in the protocol group achieved LDL-C <70 mg/dL, and 60.8% achieved the more stringent target of <55 mg/dL.
- Structured algorithms can bridge the gap between guideline recommendations and real-world lipid management post-ACS.
Study Background
Acute coronary syndrome (ACS) remains a leading cause of morbidity and mortality worldwide. Secondary prevention with intensive lipid-lowering therapy (LLT) is a cornerstone to reduce recurrent cardiovascular events post-ACS. International guidelines recommend that patients achieve low-density lipoprotein cholesterol (LDL-C) targets below 70 mg/dL, and in very high-risk individuals, even below 55 mg/dL. However, despite clear evidence supporting the benefits of early and intensive LLT, implementation in clinical practice is often delayed or insufficient, resulting in suboptimal LDL-C control and ongoing cardiovascular risk. There is a critical unmet need for systematic care pathways that can ensure rapid lipid management escalation during and after ACS hospitalization.
Study Design
The BRIDGE trial was a multicenter, cluster-randomized study conducted from November 2024 to July 2025 across 10 centers, randomized 1:1 to either a protocol-based intensive lipid management strategy or standard lipid care. Eligible patients were those hospitalized with ACS. The protocol-based group utilized a prespecified algorithm to guide early initiation or intensification of LLT, including high-intensity statins, ezetimibe, and PCSK9 inhibitors, tailored according to baseline therapy and LDL-C levels. LDL-C was reassessed at 4 weeks, with protocol-mandated intensification if LDL-C exceeded approximately 55 mg/dL. The primary endpoint was the proportion of patients achieving LDL-C <70 mg/dL at 6 months, with a key secondary endpoint of LDL-C <55 mg/dL. Both groups aimed for LDL-C <70 mg/dL as the fundamental treatment goal.
Key Findings
A total of 330 ACS patients were enrolled, with 329 included in the analysis. Baseline characteristics were balanced; the mean patient age was 69 years, with 18% female, and a median baseline LDL-C of 110 mg/dL. At the 6-month follow-up:
– LDL-C <70 mg/dL was achieved in 86.4% of patients in the protocol-based group versus 73.7% in the standard care group (difference of 12.6 percentage points; 95% CI: 3.8–21.5; P=0.005).
– Achievement of LDL-C <55 mg/dL was significantly higher in the protocol group (60.8%) compared with standard care (34.5%), corresponding to a 26.3 percentage point absolute difference (95% CI: 18.5–34.0; P<0.001).
– Sensitivity analyses at the hospital level showed trends consistent with the primary analysis.
– The protocol-based group had higher use of high-intensity statins, ezetimibe, and PCSK9 inhibitors at 6 months.
These findings illustrate that a structured, algorithm-driven approach leads to earlier and more aggressive lipid management, helping nearly 9 out of 10 patients achieve guideline LDL-C targets within half a year post-ACS.
Expert Commentary
The BRIDGE trial provides robust evidence addressing a persistent challenge in cardiovascular care: the implementation gap for guideline-based LLT after ACS. By embedding a protocol into clinical workflows, this trial highlights how early, intensified lipid management can be operationalized effectively. The stepwise intensification protocol—anchored by LDL-C reassessment at 4 weeks—ensures personalized treatment escalation, preventing treatment inertia.
The use of combination therapy, including PCSK9 inhibitors, reflects contemporary evidence that aggressive LDL-C lowering through multiple agents yields incremental benefit in high-risk patients. Although the trial was cluster-randomized at the center level, real-world adoption may require clinician education, electronic health record integration, and patient adherence support.
Limitations include the regional scope, which may affect generalizability, and the relatively short follow-up duration focusing on surrogate endpoints rather than long-term cardiovascular outcomes. Nevertheless, these LDL-C improvements are well-established surrogates predictive of risk reduction.
Conclusion
The BRIDGE trial confirms that a protocol-based approach to lipid management in ACS patients significantly improves attainment of contemporary LDL-C targets compared to usual care. This supports adoption of algorithm-driven pathways incorporating early initiation and escalation of multi-drug LLT regimens. Such strategies can bridge the persistent gap between evidence-based guidelines and clinical practice, ultimately enhancing secondary prevention efforts and reducing recurrent cardiovascular events.
Funding and Trial Registration
The trial was registered as jRCT1020240029. Funding details were not specified in the provided abstract. Detailed disclosures can be found in the original publication.
References
1. Oyama K, Takahashi J, Funaki T, et al. Protocol-Based Implementation of Early Intensive Lipid Management After Acute Coronary Syndrome: The BRIDGE Trial. J Am Coll Cardiol. 2026 Aug 31; PMID: 42671370.
2. Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC Guideline on the Management of Blood Cholesterol. Circulation. 2019;139(25):e1082-e1143.
3. Schwartz GG, Steg PG, Szarek M, et al. Alirocumab and Cardiovascular Outcomes after Acute Coronary Syndrome. N Engl J Med. 2018;379(22):2097-2107.
4. Giugliano RP, Mach F, Zavitz K, et al. Benefit of Adding Ezetimibe to Statin Therapy on Cardiovascular Outcomes. N Engl J Med. 2017;376(7):520-528.