Pregnancy Following Hemithyroidectomy: Elevated Risk of Gestational Overt Hypothyroidism Amid Favorable Obstetric Outcomes
Highlight
- Preconception hemithyroidectomy is associated with a markedly increased risk of gestational overt hypothyroidism, particularly in women treated for thyroid cancer.
- Thyroid hormone replacement during pregnancy is significantly more frequent among women with prior hemithyroidectomy compared to controls.
- A substantial surveillance gap exists, with nearly 30% of women missing first-trimester TSH screening despite increased risk.
- Despite biochemical thyroid dysfunction, adverse obstetric outcomes are not increased compared with euthyroid pregnant women with intact thyroid glands.
Study Background
Hemithyroidectomy, the surgical removal of one thyroid lobe, is commonly performed for benign thyroid nodules, follicular lesions, or small differentiated thyroid cancers. While patients generally maintain thyroid function postoperatively, the residual thyroid tissue may not always fully compensate during increased physiological demands such as pregnancy. Gestational hypothyroidism, particularly overt hypothyroidism (elevated TSH with low free T4), is linked to adverse maternal and fetal outcomes including miscarriage, preterm birth, and impaired neurodevelopment in offspring. Understanding the risk gestational hypothyroidism in women with preconception hemithyroidectomy is essential for optimizing prenatal care.
Study Design
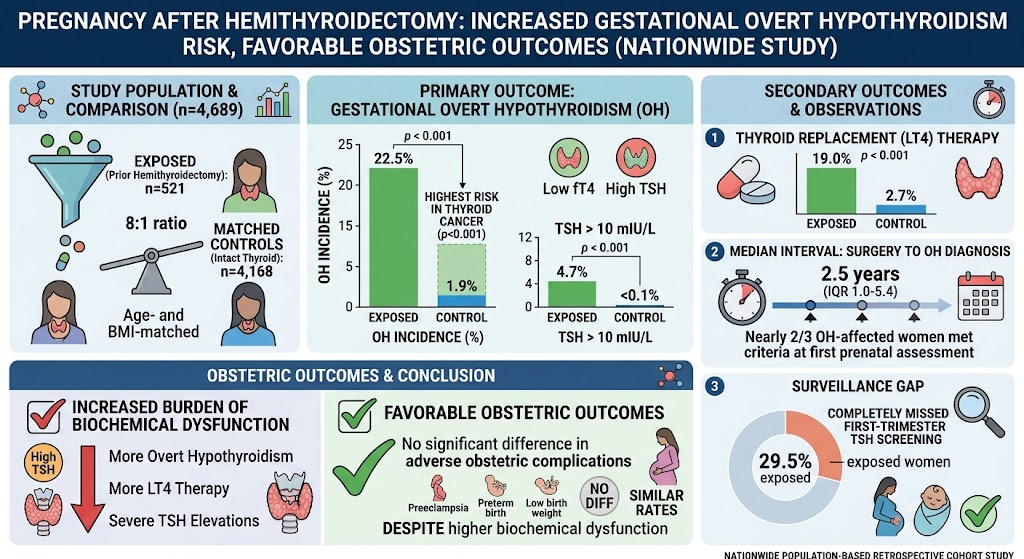
This nationwide, retrospective cohort study utilized a comprehensive integrated healthcare database to identify pregnancies in euthyroid women with prior hemithyroidectomy compared with age- and body mass index (BMI)-matched controls with intact thyroid glands, using an 81:1 matching ratio. The primary endpoint was overt gestational hypothyroidism during pregnancy, defined by elevated thyrotropin (TSH) with concomitant low free thyroxine (free T4). Secondary outcomes included the need for thyroid hormone replacement therapy during pregnancy, obstetric complications, and timing from surgery to onset of overt hypothyroidism. The cohort comprised 521 pregnancies in women with prior hemithyroidectomy and 4,168 matched controls. Subgroup analyses included stratification by hemithyroidectomy indication (e.g., thyroid cancer).
Key Findings
The incidence of overt gestational hypothyroidism was significantly higher in the hemithyroidectomy cohort compared to controls (22.5% vs. 1.9%, p < 0.001). Those who underwent surgery for thyroid cancer exhibited the highest risk within this group. Thyroid hormone replacement therapy during pregnancy was administered in 19% of women post-hemithyroidectomy versus 2.7% in controls (p < 0.001). Furthermore, 4.7% of exposed pregnancies demonstrated TSH levels exceeding 10 mIU/L, indicative of severe hypothyroidism, compared to less than 0.1% in controls (p < 0.001).
The median interval between hemithyroidectomy and gestational diagnosis of overt hypothyroidism was 2.5 years (interquartile range, 1.0–5.4 years). Remarkably, almost two-thirds of these women met biochemical criteria for hypothyroidism at their first prenatal visit, underscoring the need for early thyroid function assessment.
Despite this increased biochemical risk, the investigation reported no statistically significant differences in absolute rates of adverse obstetric outcomes such as miscarriage, preterm delivery, gestational hypertension, or low birth weight between women with and without prior hemithyroidectomy.
An alarming observation was that 29.5% of women with prior hemithyroidectomy did not undergo first-trimester TSH screening, revealing a surveillance gap that potentially delays identification and management of gestational hypothyroidism in this high-risk population.
Expert Commentary
These findings elucidate critical clinical considerations for managing pregnancies after hemithyroidectomy. The significantly elevated risk of overt hypothyroidism—especially among those operated for thyroid cancer—aligns with the biological premise that diminished thyroid reserve may be insufficient to meet increased pregnancy demands. Early and regular TSH monitoring, ideally commencing preconception or at earliest prenatal visits, is imperative to prompt initiation of levothyroxine therapy.
Current guidelines from endocrine societies recommend tighter monitoring of thyroid function in pregnant women with a history of thyroid surgery; however, the detected screening gaps highlight implementation challenges. The absence of adverse obstetric outcomes despite biochemical hypothyroidism suggests timely management mitigates risks, emphasizing the value of surveillance.
Limitations include the retrospective design and reliance on biochemical and administrative data which may not capture all clinical nuances or adherence to therapy. Additionally, generalizability may vary with healthcare system characteristics and population demographics.
Conclusion
Preconception hemithyroidectomy carries a substantially increased risk of overt gestational hypothyroidism and greater need for thyroid hormone replacement therapy, particularly following thyroid cancer surgery. Nonetheless, when hypothyroidism is detected and treated, obstetric outcomes remain comparable to those in women with intact thyroid glands. These results reinforce the importance of comprehensive thyroid function screening and close surveillance during pregnancy in this population to optimize maternal and fetal health outcomes.
Funding and ClinicalTrials.gov
The study by Yamin T et al. does not explicitly report external funding sources. ClinicalTrials.gov registration details are not provided for this retrospective cohort analysis.
References
1. Alexander EK, Pearce EN, Brent GA, et al. 2017 Guidelines of the American Thyroid Association for the diagnosis and management of thyroid disease during pregnancy and the postpartum. Thyroid. 2017;27(3):315-389.
2. Yamin T, Asias A, Osovizky Y, et al. Pregnancy after Hemithyroidectomy: Increased Risk of Gestational Overt Hypothyroidism Despite Favorable Obstetric Outcomes: A Nationwide Study. Thyroid. 2026 Aug 24; [Epub ahead of print]. doi:10.1089/thy.2026.05
3. Stagnaro-Green A, et al. Guidelines for the prevention, detection, and management of thyroid dysfunction during pregnancy and postpartum. J Clin Endocrinol Metab. 2011;96(8):2543-65.
4. Negro R, et al. Levothyroxine treatment of subclinical hypothyroidism in pregnancy: effects on obstetrical complications. J Clin Endocrinol Metab. 2006;91(7):2587–2591.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.