Highlight
1. Baseline plasma sRAGE, a biomarker of alveolar epithelial injury, detects heterogeneity in treatment effects of lung recruitment on mortality among ARDS patients.
2. Lung recruitment significantly reduces 90-day mortality in patients with high plasma sRAGE but increases mortality in those with low sRAGE.
3. Inflammatory phenotypes, defined by IL-8, sTNFr-1, and bicarbonate, predict mortality but do not identify differential responsiveness to lung recruitment.
4. sRAGE trajectories differ by baseline level and ventilation strategy, supporting its role in monitoring and personalizing ARDS treatment.
Study Background
Acute Respiratory Distress Syndrome (ARDS) remains a major cause of morbidity and mortality in critically ill patients, characterized by diffuse alveolar injury, inflammation, and impaired gas exchange. Current ventilation guidelines advise against routine use of lung recruitment maneuvers due to inconsistent benefits and potential harm. However, variability in ARDS etiology and pathophysiology suggests a need for personalized ventilatory strategies. Biomarkers reflecting epithelial injury and systemic inflammation may identify patient subgroups who might benefit from tailored interventions. The soluble receptor for advanced glycation end products (sRAGE), measurable in plasma, is a validated marker of alveolar epithelial injury. Inflammatory phenotypes classified by key cytokines (IL-8, sTNFr-1) and metabolic parameters (bicarbonate) also stratify ARDS mortality risk. This secondary analysis of the LIVE trial explores whether baseline sRAGE levels or inflammatory phenotypes modify the effect of lung recruitment on mortality in ARDS, aiming to refine patient selection for this intervention.
Study Design and Methods
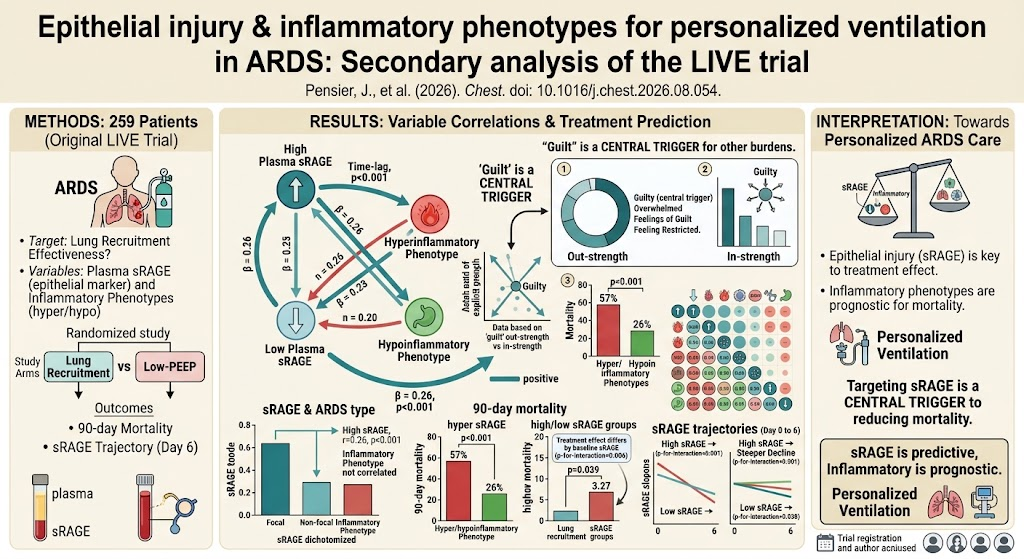
The analysis included 259 ARDS patients from the LIVE randomized controlled trial comparing lung recruitment maneuvers plus high PEEP versus low PEEP strategies, stratified by the morphology of ARDS (focal vs non-focal). Plasma sRAGE was measured at baseline and dichotomized at 2,440 pg/mL into high and low categories. Inflammatory phenotypes were identified using a validated parsimonious model incorporating interleukin-8 (IL-8), soluble tumor necrosis factor receptor 1 (sTNFr-1), and bicarbonate levels to categorize patients into hyperinflammatory or hypoinflammatory phenotypes. The primary endpoint was 90-day mortality; the secondary endpoint involved evaluating sRAGE trajectories up to day 6 post-randomization. Analytical methods included inverse probability weighting, weighted Cox proportional hazards models, and joint models for longitudinal biomarker data. Interaction terms tested for heterogeneity of treatment effect by biomarker-defined subgroups.
Key Findings
Correlation of sRAGE with ARDS Morphology: High plasma sRAGE levels correlated moderately with non-focal ARDS phenotype (correlation coefficient r=0.26, p<0.001), indicating greater epithelial injury in this subgroup. Inflammatory phenotypes showed no significant correlation with ARDS morphology.
Heterogeneity of Treatment Effect on Mortality by sRAGE: There was a statistically significant interaction between baseline sRAGE levels and treatment effect of lung recruitment on 90-day mortality (p-for-interaction=0.006). Among patients with high sRAGE, lung recruitment was associated with a marked reduction in mortality (hazard ratio [HR] 0.41; 95% confidence interval [CI] 0.18-0.93; p=0.033). Conversely, patients with low sRAGE experienced significantly increased mortality with lung recruitment (HR 3.27; 95% CI 1.06-10.1; p=0.039). This dichotomous effect supports the use of sRAGE as a predictive biomarker to guide ventilation strategies.
Inflammatory Phenotypes and Mortality Prognosis: The hyperinflammatory phenotype was strongly associated with higher 90-day mortality compared to hypoinflammatory patients (57% vs 26%, p<0.001), confirming its prognostic value. However, inflammatory phenotype status did not identify heterogeneity in response to lung recruitment (p-for-interaction=0.56), indicating limited utility for guiding personalized ventilation.
sRAGE Trajectories and Ventilation Impact: Lung recruitment influenced sRAGE longitudinal trajectories differently based on baseline sRAGE levels. In patients with high baseline sRAGE, recruitment was associated with a steeper decline in plasma sRAGE over days (p-for-interaction <0.001), suggesting reduced epithelial injury or enhanced recovery. Conversely, lung recruitment slowed sRAGE decline among low-sRAGE patients (p-for-interaction=0.038), consistent with possible injury exacerbation in this subgroup. These dynamic biomarker changes reinforce sRAGE’s clinical relevance in monitoring treatment effects.
Sensitivity Analyses: Results remained directionally consistent in analyses without inverse probability weighting, strengthening the robustness of the findings.
Expert Commentary
This secondary analysis offers compelling evidence that plasma sRAGE, an alveolar epithelial injury biomarker, can stratify ARDS patients by risk and predict differential survival benefit or harm from lung recruitment maneuvers. Unlike the inflammatory subphenotypes, sRAGE identifies a physiological mechanism—epithelial injury—that directly interfaces with mechanical ventilation’s impact. These findings highlight the potential for biomarker-guided personalized ventilation strategies to improve outcomes in ARDS, addressing heterogeneity that hampers one-size-fits-all approaches.
However, interpretation requires caution. The findings derive from a secondary analysis with moderate sample size; prospective validation is essential before clinical implementation. The cutoff of 2,440 pg/mL for sRAGE awaits broader corroboration. Furthermore, inflammatory phenotyping’s prognostic but not predictive role underscores the complexity of ARDS pathobiology and suggests that inflammatory status alone may not suffice to tailor mechanical ventilation.
Mechanistically, elevated sRAGE reflects extensive epithelial cell injury or barrier disruption, which lung recruitment might alleviate by restoring alveolar patency and reducing cyclic stretch in injured lung units. In patients with low epithelium injury, recruitment could provoke overdistension or injury, explaining the observed harm. Monitoring sRAGE trajectories could thus inform dynamic ventilatory adjustments.
Conclusion
This study provides important proof-of-concept that epithelial injury assessed via plasma sRAGE can identify ARDS patients most likely to benefit from lung recruitment strategies, while those with low injury might be harmed. Inflammatory phenotypes remain valuable prognostic markers but lack predictive power for recruitment response. Incorporating sRAGE measurements into clinical decision-making promises enhanced personalization of mechanical ventilation, potentially improving survival in ARDS. Future prospective trials should validate sRAGE-guided ventilation protocols and explore integration with other biomarkers to optimize care for this heterogeneous syndrome.
Funding and ClinicalTrials.gov
Original trial funded by French institutions with no declared direct industry support for this secondary analysis. Clinical trial registration: LIVE trial ClinicalTrials.gov NCT02439045.
References
1. Pensier J et al. Epithelial injury and inflammatory phenotypes for personalized ventilation in ARDS: Secondary analysis of the LIVE trial. Chest. 2026 Sep 23. PMID: 42777910.
2. Calfee CS, et al. Subphenotypes in acute respiratory distress syndrome: latent class analysis of data from two randomised controlled trials. Lancet Respir Med. 2014;2(8):611-20.
3. Jabaudon M, et al. Plasma sRAGE as a prognostic marker in ARDS: a multicenter study. Intensive Care Med. 2018;44(7):1049-57.
4. Fan E, et al. Clinical practice guidelines for mechanical ventilation in adults with ARDS. Am J Respir Crit Care Med. 2017;195(9):1253-63.
5. Famous KR, et al. ARDS subphenotypes and differential response to PEEP mechanical ventilation. Am J Respir Crit Care Med. 2017;195(3):331-338.