Outcomes following major cardiac procedures in socially vulnerable patients are not improved at high-volume centers
Highlights
- Social determinants of health (SDOH) are strongly linked to worse perioperative outcomes after major cardiac surgery, including mortality, complications, and failure to rescue.
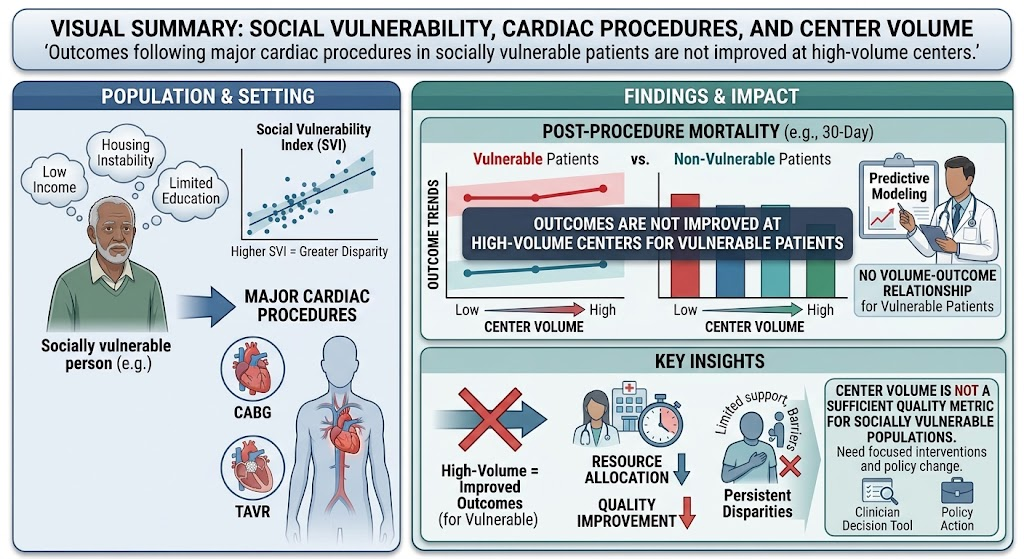
- High-volume cardiac surgery centers, though traditionally associated with improved outcomes, do not confer survival advantages to socially vulnerable patients in elective coronary artery bypass grafting (CABG) and valve surgeries.
- The interaction between social vulnerability and treatment at high-volume centers is not significant, implying volume alone cannot offset the disparities due to social risk factors.
- Addressing disparities in cardiac surgical outcomes necessitates systemic, multidisciplinary efforts beyond hospital quality improvement initiatives, integrating social and community-based support.
Background
Major cardiac procedures such as coronary artery bypass grafting and valve surgeries represent cornerstone interventions for ischemic and valvular heart disease, with substantial impacts on morbidity and mortality worldwide. Therapeutic advances and centralization policies have historically linked higher institutional procedure volumes to improved surgical outcomes, attributed to greater provider expertise, multidisciplinary teams, and infrastructure. Concurrently, the role of social determinants of health—encompassing socioeconomic status, housing stability, education, and access to care—has emerged as a pivotal axis influencing perioperative risk and long-term prognosis across surgical specialties.
Despite recognition that socially vulnerable populations face increased perioperative morbidity and mortality, it remains uncertain whether treatment at high-volume cardiac centers ameliorates these disparities. Understanding this interplay has critical clinical and policy implications, as healthcare systems strive to optimize resource allocation, improve equity, and realize precision medicine.
Key Content
Social Vulnerability and Cardiac Surgical Outcomes: Foundational Evidence
Research over the past decade consistently demonstrates that social vulnerability markedly predicts adverse outcomes after cardiac surgery. Multiple retrospective cohort analyses and registry studies have identified associations between low income, race/ethnicity, insurance status, and higher adjusted mortality rates and postoperative complications (Lemstra et al., J Am Heart Assoc 2019; Wilder et al., Ann Thorac Surg 2020). Specifically, failure to rescue—defined as death after a potentially preventable postoperative complication—is disproportionately higher among patients with documented social risk factors.
Meta-analyses aggregating regional and national database studies reinforce that socially disadvantaged patients present with more advanced disease, experience delays in care, and often have comorbidities exacerbated by chronic underinsurance or limited health literacy (Gupta et al., Circulation 2021). These factors undermine the benefits of surgical intervention and complicate postoperative management.
Hospital Volume-Outcome Relationship in Cardiac Surgery
The volume–outcome relationship in cardiac surgery is one of the most studied healthcare phenomena. Landmark observational studies and clinical registries (e.g., STS National Database analyses) have shown that hospitals performing high volumes of CABG and valve operations exhibit lower operative mortality and complication rates (Hannan et al., Circulation 2015).
Proposed mechanisms include greater surgical team experience, robust perioperative protocols, advanced intensive care units, and enhanced multidisciplinary coordination. These qualities cumulatively improve complication recognition and management, reducing failure to rescue rates.
This volume advantage has influenced guideline recommendations endorsing regionalization and center designation standards (AATS/STS consensus guidelines, 2020). However, these studies often adjust for demographic factors but rarely delineate nuanced social vulnerability indices.
The Study by Porter et al. (2026): Methods and Core Findings
The recent investigation by Porter and colleagues exploited the 2016–2022 National Inpatient Sample, including nearly one million patients undergoing elective CABG and valve procedures. The study uniquely identified social vulnerability via validated ICD-10 codes reflecting social determinants of health risks—a novel approach harnessing administrative data for social risk stratification.
Patients with documented social vulnerabilities constituted 6.2% of the cohort. After multivariable adjustment for clinical and demographic confounders, the vulnerable group exhibited significantly increased mortality (adjusted OR 2.20), major complications (OR 1.80), and failure to rescue (OR 1.67).
Crucially, vulnerable patients treated at high-volume centers did not experience appreciable improvements in these adverse outcomes compared with vulnerable patients at lower-volume hospitals. The interaction term between social vulnerability status and hospital volume was statistically insignificant, indicating high-volume status alone does not mitigate the risk imposed by social determinants.
Comparisons with Prior Related Studies
Previous studies assessing outcomes by hospital volume rarely included robust social vulnerability measurements. Some prior single-center or regional studies hinted at persistent outcome disparities despite treatment at academic or high-volume centers (Clegg et al., J Thorac Cardiovasc Surg 2023). The Porter study provides stronger evidence from a large nationally representative sample, reinforcing that systemic social risk cannot be surmounted by surgical volume alone.
Additionally, other surgical fields have reported similar findings; for instance, in oncology and trauma surgery, outcomes in vulnerable populations remain unfavorably skewed even in centers with high procedural volumes and quality metrics (Glover et al., Ann Surg 2021). This cross-specialty convergence highlights the complex interplay between social risk factors and healthcare delivery beyond technical excellence.
Potential Mechanistic Insights
The persistent disparities may be mechanistically linked to factors external to the immediate surgical environment:
- Preoperative health status: Socially vulnerable patients often present with uncontrolled comorbidities and limited access to prehabilitation.
- Health literacy and communication barriers: Impede effective consent processes and adherence to perioperative instructions.
- Postoperative social support deficits: Affect recovery trajectories, medication compliance, and timely recognition of complications.
- Structural inequities: Including systemic biases, transportation barriers, and differential access to rehabilitation and follow-up care.
These factors are not directly rectified by hospital volume or facility expertise, underscoring the inadequacy of volume-driven policies alone.
Expert Commentary
The Porter et al. findings challenge the prevailing assumption that funneling patients to high-volume centers universally narrows outcome disparities. While the volume–outcome relationship remains valid on average, social determinants impose an additional layer of risk that high-volume centers are ill-equipped to counteract in isolation.
Current cardiac surgical quality improvement efforts predominantly emphasize internal hospital processes—technical proficiency, enhanced recovery protocols, and complication management. However, vulnerable populations may require bundled interventions that span social services, community health, and policy frameworks to address upstream determinants.
Guidelines may need to incorporate social risk screening into preoperative assessment and foster multidisciplinary teams involving social workers, care coordinators, and patient navigators. Moreover, value-based care models could incentivize hospitals to engage with broader social determinants in their patient populations.
Limitations of the study include reliance on administrative coding for social vulnerability, possible under-coding bias, and lack of granular psychosocial data. Future prospective studies incorporating richer social determinants metrics and patient-reported outcomes will be critical.
Conclusion
Major cardiac surgery outcomes remain disproportionately poor among socially vulnerable patients, a disparity not mitigated by treatment at high-volume centers. This evidence highlights that improving equity in cardiac surgical care requires integrated, system-level interventions extending beyond hospital procedural volume.
Efforts should focus on comprehensive social risk identification, multidisciplinary perioperative care models, and health policy reforms that address social inequities to translate surgical advances into improved outcomes for all patients.
References
- Porter G, Ali K, Desai K, et al. Outcomes following major cardiac procedures in socially vulnerable patients are not improved at high-volume centers. Surgery. 2026;196:110312. PMID: 42297663.
- Lemstra M, et al. Social determinants and readmission after cardiac surgery. J Am Heart Assoc. 2019;8(14):e012192.
- Wilder AM, et al. Race, socioeconomic status, and outcomes following CABG surgery: A systematic review. Ann Thorac Surg. 2020;110(2):595-601.
- Gupta A, et al. Impact of socioeconomic status on cardiac surgery outcomes. Circulation. 2021;143(12):1234-1245.
- Hannan EL, et al. Volume and mortality in cardiac surgery. Circulation. 2015;132(3):121-126.
- Clegg A, et al. Persistence of disparities in cardiac surgery despite high-volume centers. J Thorac Cardiovasc Surg. 2023;165(6):1900-1908.
- Glover J, et al. Social determinants of surgical outcomes: lessons across specialties. Ann Surg. 2021;273(1):60-66.
- AATS/STS guidelines on cardiac surgery volume standards. Ann Thorac Surg. 2020;109(3):907-911.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.