Highlights
- Medicare patients with acute interstitial pneumonia (AIP) and concomitant autoimmune conditions demonstrated significantly lower 90-day mortality.
- These patients were more likely to be discharged home rather than to skilled nursing facilities, suggesting more favorable functional recovery.
- No significant differences were observed in mechanical ventilation rates, recurrence of AIP, length of hospital stay, or MarketScan claims between groups.
- Findings highlight the importance of specialty care engagement and tailored treatment strategies in the autoimmune subgroup of AIP patients.
Background
Acute interstitial pneumonia (AIP) is a rare, severe form of idiopathic interstitial lung disease characterized by diffuse alveolar damage and rapid progression to respiratory failure. Due to its rarity, substantial gaps remain in understanding factors influencing disease outcomes. Autoimmune conditions have been implicated in various interstitial lung diseases, yet their role in AIP remains poorly elucidated. Recognizing how the presence of autoimmune diseases modifies clinical outcomes in AIP could inform patient stratification, management decisions, and prognosis.
Key Content
Study Design and Patient Cohorts
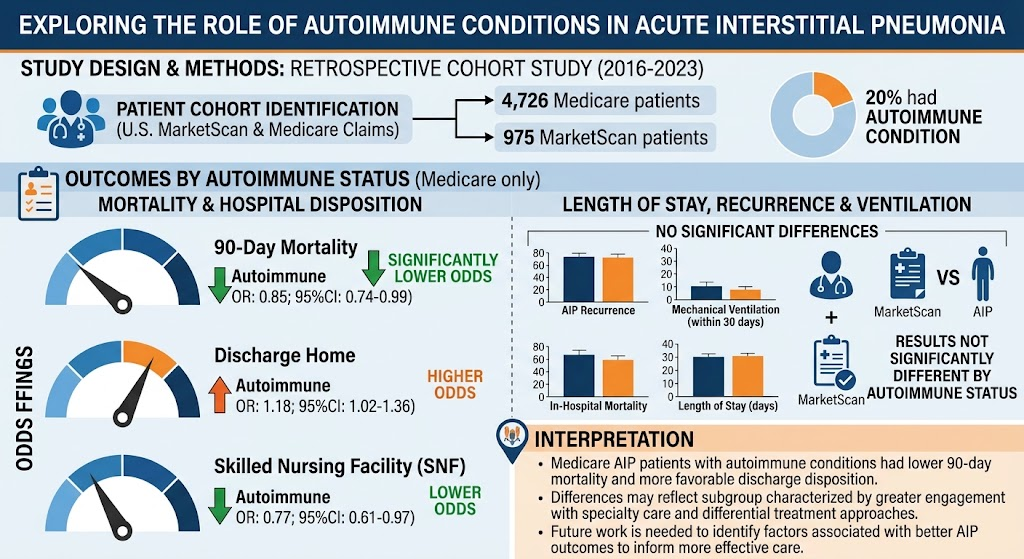
Nikahd et al. (2026) conducted a large retrospective cohort study leveraging U.S. MarketScan and Medicare claims data spanning 2016-2023, encompassing 4,726 Medicare patients and 975 MarketScan patients hospitalized for AIP. Approximately 20% of these patients were identified as having an autoimmune condition based on ICD-10 coding.
Mortality Outcomes
Among Medicare beneficiaries, patients with autoimmune conditions had a lower adjusted odds ratio (OR 0.85; 95% CI, 0.74–0.99) for 90-day mortality compared to those without. This suggests a survival advantage potentially mediated by early recognition, engagement with specialty autoimmune care, or differential therapeutic approaches including immunomodulation.
Discharge Disposition and Functional Recovery
Autoimmune AIP patients in the Medicare cohort had higher likelihood of discharge to home (OR 1.18; 95% CI, 1.02–1.36) and lower odds of discharge to skilled nursing facilities (OR 0.77; 95% CI, 0.61–0.97), indicating potentially better functional status post-hospitalization and fewer complications or comorbidities necessitating institutional care.
Other Clinical Outcomes
There was no significant difference in length of hospital stay, AIP recurrence, or use of mechanical ventilation within 30 days between autoimmune and non-autoimmune groups in either dataset. MarketScan patients did not demonstrate significant differences across measured outcomes by autoimmune status, possibly reflecting differences in population demographics, data completeness, or healthcare utilization patterns.
Contextualizing Findings with Autoimmune Pancreatitis and IgG4-Related Diseases
While the study focused on pulmonary AIP, extensive literature on autoimmune pancreatitis (AIP) and immunoglobulin G4-related disease (IgG4-RD) provides mechanistic insights into systemic autoimmune processes affecting multiple organs, including lung involvement. Advances in diagnostic modalities such as endoscopic ultrasound-guided fine-needle biopsy (EUS-FNB) have improved tissue diagnosis and subtype differentiation in AIP (BMC Gastroenterol 2026; Endoscopy 2020). The management of autoimmune conditions with glucocorticoids and steroid-sparing therapies (e.g., azathioprine, rituximab) has demonstrated favorable outcomes and relapse prevention in systemic IgG4-related diseases, which may share pathogenic pathways influencing pulmonary manifestations (Clin Rheumatol 2025; Gut 2017).
Mechanistic Considerations and Specialty Care Factors
The observed survival benefit and improved discharge disposition might reflect several factors: early diagnosis through heightened clinical suspicion, proactive immunosuppressive treatment, multidisciplinary management involving pulmonologists, rheumatologists, and immunologists, and heightened patient engagement in follow-up care. The heterogeneity of autoimmune diseases and their diverse impact on lung pathology suggest that specific autoimmune subtypes may differentially influence AIP progression and outcomes.
Expert Commentary
Nikahd and colleagues contribute valuable epidemiological data that advances understanding of AIP in the context of concurrent autoimmune diseases. Their findings underscore the necessity of a tailored clinical approach recognizing the interplay between systemic autoimmunity and acute pulmonary injury.
However, limitations inherent to claims-based analyses include potential misclassification bias due to reliance on ICD-10 codes, lack of granular clinical data (e.g., pulmonary function testing, serological markers), and inability to assess treatment heterogeneity or severity indices. The differing signals between Medicare and MarketScan data may reflect underlying population differences, including age, comorbidity burden, and healthcare access differences.
Clinicians should be attentive to the coexistence of autoimmune conditions in patients presenting with acute interstitial pneumonia, as this subgroup may have distinct prognoses and therapeutic opportunities. Integrating multidisciplinary care pathways that include early autoimmune disease evaluation and immunomodulatory treatment may improve survival and functional outcomes.
Future research should prospectively characterize autoimmune subtypes, immunological profiles, and treatments to define precise prognostic markers and therapeutic strategies. There is also a need to explore mechanistic pathways linking systemic autoimmunity with diffuse alveolar damage and lung remodeling in AIP.
Conclusion
Recent large-scale data indicate that autoimmune conditions in patients with acute interstitial pneumonia are associated with lower short-term mortality and increased likelihood of home discharge. These observations suggest a potentially distinct clinical phenotype characterized by better engagement with specialty care and possibly different therapeutic responses. While length of stay, ventilation requirements, and recurrence rates appear comparable, the autoimmune subgroup merits focused clinical and translational investigation to optimize outcomes.
Enhanced recognition of autoimmune contributions to AIP, adoption of standardized diagnostic criteria, and tailored immunomodulatory therapies constitute critical directions for improving AIP patient management. Multidisciplinary collaboration and prospective studies integrating clinical, radiologic, histopathologic, and immunologic data remain essential to unravel the complexities of autoimmune-mediated lung injury.
References
- Nikahd M, Small B, Hand BN. Exploring the role of autoimmune conditions in acute interstitial pneumonia. Chest. 2026 Aug 18; PMID: 42612903. https://pubmed.ncbi.nlm.nih.gov/42612903/
- Zen Y, et al. Comparison of 19-gauge aspiration needles versus 20-gauge forward-bevel needles for diagnosing autoimmune pancreatitis: a single-centre randomized controlled trial. BMC Gastroenterol. 2026 Apr 21;26(1):342. PMID:42014994.
- Yang MZ, et al. Clinical features, responses to therapy and prognosis of IgG4-related cholangitis: a retrospective study. BMC Gastroenterol. 2026 Jan 7;26(1):102. PMID:41495676.
- Matsubayashi H, et al. Randomised controlled trial of long-term maintenance corticosteroid therapy in patients with autoimmune pancreatitis. Gut. 2017 Mar;66(3):487-494. PMID:27543430.
- Wallace ZS, et al. Discriminative features of IgG4-related disease and associated autoimmune rheumatic diseases: Nationwide observational cohort. Clin Rheumatol. 2025 Feb;44(2):747-756. PMID:39751976.
- Masamune A, et al. Impact of EUS-guided fine-needle biopsy sampling on International Consensus Diagnostic Criteria for diagnosing autoimmune pancreatitis: a prospective multicenter study. Gastrointest Endosc. 2025 Oct;102(4):559-568.e1. PMID:40024297.