Patient Information
This retrospective case series includes eight adult patients (4 males, 4 females), ranging in age from 24 to 74 years old, who presented with severe, refractory hypoglycemia caused by malignant insulin-secreting tumors. The Eastern Cooperative Oncology Group (ECOG) performance status among patients ranged from 1 to 3 at baseline, indicating varying degrees of functional impairment. Seven patients were diagnosed with metastatic insulinoma, a rare neuroendocrine tumor that secretes insulin inappropriately, and one patient had hypoglycemia secondary to a cervical neuroendocrine carcinoma with insulin secretion.
Each patient suffered from hypoglycemic episodes refractory to conventional treatment strategies, including continuous intravenous glucose infusion and multiple antihypoglycemic medications, resulting in significant morbidity and hospital admissions. Relevant medical histories included previous tumor diagnosis and ongoing metastatic disease.
Diagnosis
The diagnosis of insulin-secreting tumors was established based on biochemical evidence of endogenous hyperinsulinemic hypoglycemia (low blood glucose accompanied by inappropriately elevated insulin levels), imaging confirming tumor presence and metastasis, and clinical presentation of recurrent spontaneous hypoglycemia.
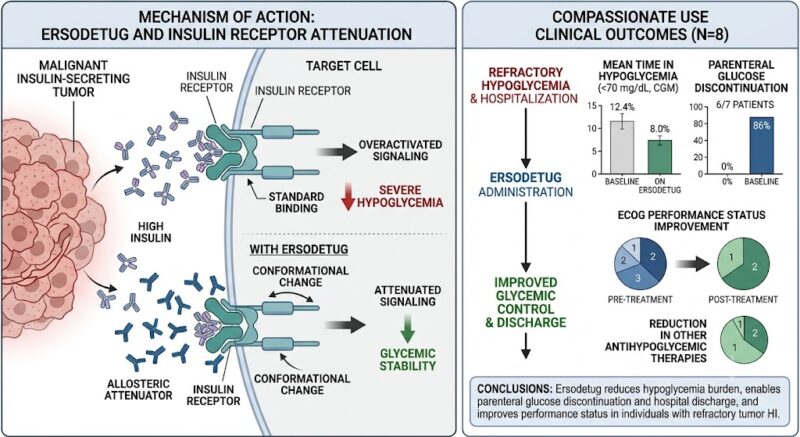
Continuous glucose monitoring (CGM) was employed to quantify hypoglycemia burden, defined as percentage time spent below 70 mg/dL glucose. Baseline CGM data showed a mean of 12.4% time in hypoglycemia across patients.
Differential Diagnosis
Differential considerations in these cases of refractory hypoglycemia included:
– Non-insulinoma pancreatogenous hypoglycemia syndrome (NIPHS)
– Exogenous insulin or sulfonylurea overdose
– Critical illnesses causing hypoglycemia (e.g., hepatic failure, adrenal insufficiency)
– Insulin autoimmune syndrome
However, these were excluded through detailed clinical assessment, laboratory testing (including medication screens), and tumor imaging.
Treatment and Management
Ersodetug, a fully human monoclonal antibody targeting the insulin receptor to allosterically attenuate insulin signaling, was used under compassionate use protocols due to lack of effective standard treatment options.
Dosing regimens involved intravenous administration at 6 or 9 mg/kg every 1 to 2 weeks initially, tailored based on clinical response, followed by maintenance dosing every 2 to 5 weeks as appropriate. This dosing schedule was individualized to maintain glycemic stability while minimizing adverse effects.
Supportive care included discontinuation or tapering of continuous intravenous glucose infusions wherever feasible, along with reduction of other antihypoglycemic therapies. Patients were closely monitored clinically and biochemically for response and toxicity.
Outcome and Prognosis
Ersodetug treatment resulted in significant clinical improvements:
– Six of seven patients dependent on parenteral glucose infusions were able to discontinue this support after a median of 4.5 days of therapy.
– CGM demonstrated a 35.6% relative reduction in time spent in hypoglycemia (from 12.4% to 8.0%; pseudo-median paired change of -3.8 percentage points, 90% CI -8.2 to -1.1; P=0.02).
– Antihypoglycemic therapy use also substantially decreased (pseudo-median change, -2.5; 90% CI -3.5 to -1.0; P=0.02).
– Functional status, as assessed by ECOG performance status, improved in several patients, enabling hospital discharge and improved quality of life.
Median treatment duration with ersodetug was 11.5 months (range 5–17 months), which roughly corresponded to patient survival in the context of metastatic disease. No serious drug-related adverse events were reported.
Discussion
Malignant insulin-secreting tumors are a rare but challenging cause of refractory hypoglycemia, often resistant to conventional therapies such as diazoxide, somatostatin analogs, and parenteral glucose supplementation. Persistent hypoglycemia can lead to neurological injury and increased mortality.
Ersodetug’s mechanism of action — selective attenuation of insulin receptor signaling — offers a novel therapeutic approach targeting the downstream effects of autonomous insulin secretion rather than insulin levels themselves. This case series demonstrates significant glycemic improvements and functional benefits, supporting its potential utility in managing tumor-induced hyperinsulinemic hypoglycemia.
The ability to reduce or discontinue continuous glucose infusions and antihypoglycemic medications not only mitigates risks associated with these supportive measures but also reduces healthcare resource utilization and improves patient autonomy.
Limitations of the current report include a small patient number and retrospective design. Future prospective trials are warranted to better define optimal dosing, long-term safety, and efficacy, as well as comparisons to existing treatments.
In conclusion, ersodetug represents a promising therapeutic advance for patients with severe, refractory hypoglycemia secondary to malignant insulin-secreting tumors. This series underscores the importance of innovative targeted therapies in rare endocrinologic malignancies.
References
1. Strosberg J, Brown SM, Shaheen S, et al. Ersodetug for Refractory Hypoglycemia Due to Malignant Insulin-Secreting Tumors. J Clin Endocrinol Metab. 2026 Aug 6; PMID: 42557582. Available from: https://pubmed.ncbi.nlm.nih.gov/42557582/
2. Service FJ. Insulinoma. Diabetes. 1995;44(11): 1234-1238.
3. Cryer PE. Hypoglycemia in diabetes: pathophysiology, prevalence, and prevention. Am J Med. 2005;118 Suppl 9A:10S-16S.
4. De Leon DD, Stanley CA. Updates on the diagnosis and management of hyperinsulinism in children. Curr Opin Pediatr. 2004;16(4):452-459.
5. Hillebrand JJ, et al. Advances in the management of insulinoma-induced hypoglycemia. Endocrinol Metab Clin North Am. 2010;39(3):519-532.