Early Exclusive Enteral Feeding in Preterm Infants: Assessing Safety and Benefits through Meta-Analysis
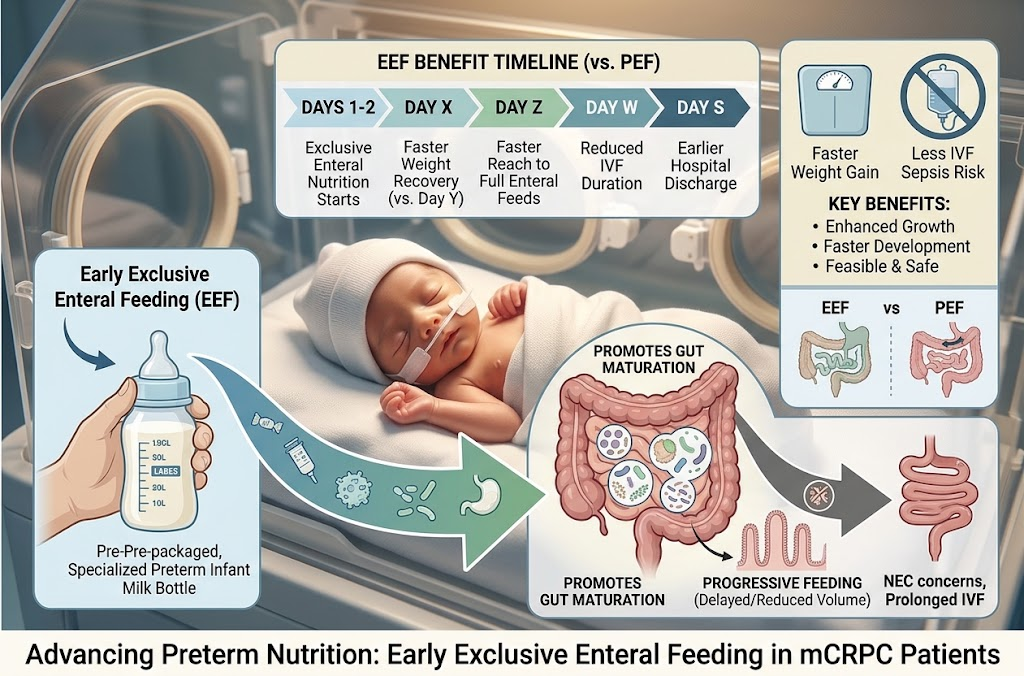
Highlight
- Early exclusive enteral feeding (EEF) in preterm infants does not increase the risk of necrotizing enterocolitis (NEC), hypoglycemia, or sepsis compared to progressive enteral feeding (PEF).
- EEF significantly shortens the time to reach full enteral feeds, reduces the duration of intravenous fluids, and enables faster weight recovery and earlier hospital discharge.
- Despite moderate to low certainty of evidence, current data supports feasibility and safety of EEF, though larger, rigorous studies are needed to confirm long-term outcomes and health economics.
Study Background
Preterm infants, defined as those born before 37 weeks’ gestation, represent a vulnerable population with unique nutritional needs essential for optimal growth and development. Enteral feeding is critical to achieve adequate nutrition but is often delayed or advanced cautiously due to concerns over feeding intolerance and the risk of necrotizing enterocolitis (NEC), a serious gastrointestinal emergency with potentially fatal consequences. Traditionally, progressive enteral feeding (PEF), involving gradual increments in feeding volume, has been standard to mitigate such risks. However, delaying or limiting enteral nutrition often necessitates prolonged intravenous fluids (IVF), which carry risks such as infection and may impede growth. Early exclusive enteral feeding (EEF), initiated within 48 hours of birth without reliance on IVF, has been proposed to improve nutritional delivery, accelerate feeding milestones, reduce hospital stay, and potentially lower healthcare costs. Nonetheless, concerns about safety, especially regarding NEC incidence, have limited widespread adoption.
Study Design
This meta-analysis systematically evaluated randomized controlled trials (RCTs) comparing EEF initiated within 48 hours of birth to the conventional PEF approach in preterm infants born between 27+0 and 36+0 weeks gestation. Data sources included MEDLINE, EMBASE, EMCARE, CINAHL, the Cochrane Library, and clinical trial registries, spanning inception through October 2025. Eleven RCTs with a combined total of 3,145 infants were analyzed. Two independent reviewers extracted clinical outcomes using standardized data collection forms to ensure reliability and minimize bias.
Primary clinical endpoints included the incidence of NEC stage 2 or greater, hypoglycemia episodes, and culture-proven sepsis. Secondary endpoints focused on time to achieve full enteral feeding, duration of IVF, time to regain birth weight, and length of hospital stay. The analysis employed pooled relative risks (RR) with 95% confidence intervals (CI) and assessed heterogeneity and evidence quality.
Key Findings
The meta-analysis revealed no statistically significant differences in safety outcomes between EEF and PEF groups:
- NEC stage 2 or greater: Pooled RR 1.00 (95% CI, 1.00–1.01; P=0.53) indicating no increased risk.
- Hypoglycemia: Pooled RR 1.00 (95% CI, 0.98–1.02; P=0.80), showing comparable risk.
- Culture-proven sepsis: Pooled RR 1.03 (95% CI, 1.00–1.07; P=0.08), suggesting no significant increase.
Regarding feeding progression and growth:
- Infants receiving EEF reached full enteral feeds significantly earlier than those on PEF.
- Duration of intravenous fluid therapy was reduced, potentially minimizing catheter-related complications.
- Faster regain of birth weight was noted, reflecting more effective nutritional support.
- Shorter hospital stays were documented, which could translate into lower healthcare resource utilization and costs.
However, the certainty of evidence varied, with moderate quality for NEC outcomes but low to very low quality for other parameters, largely due to heterogeneity across studies and the lack of blinding inherent in feeding interventions.
Expert Commentary
This meta-analysis provides compelling evidence supporting the safety and potential benefits of early exclusive enteral feeding in preterm infants. The absence of increased NEC risk allays a primary concern that has historically constrained early aggressive enteral nutrition practices. The improved feeding milestones and hospital discharge timing underscore the clinical relevance and possible economic advantages.
Nevertheless, clinicians should interpret these findings with caution. The included studies had variable gestational ages, feeding protocols, and settings that may impact generalizability. The inability to blind care providers to feeding strategy is a recognized limitation affecting bias risk. Mechanistically, early enteral nutrition may stimulate gut maturation, promote microbiota diversity, and enhance nutrient absorption, potentially explaining the observed benefits. Yet, the low evidence certainty for secondary outcomes highlights the urgent need for larger, adequately powered multicenter trials with standardized definitions and long-term neurodevelopmental follow-up.
Current neonatal nutrition guidelines are gradually incorporating more evidence supporting early parenteral nutrition reduction and cautious yet early enteral feeding advancement. This meta-analysis reinforces that judicious EEF can be safely implemented and may improve clinical outcomes. However, individualized assessments considering birth weight, gestational age, and clinical stability remain paramount.
Conclusion
Early exclusive enteral feeding in preterm infants appears feasible and safe, without increasing serious adverse events such as NEC, hypoglycemia, or culture-proven sepsis. EEF accelerates nutritional milestones, reduces reliance on intravenous support, supports faster growth, and shortens hospitalization duration. Despite promising findings, moderate to low certainty of evidence warrants cautious interpretation. Further large-scale, well-designed RCTs across diverse neonatal care environments are essential to validate safety, clarify cost-effectiveness, and assess long-term developmental outcomes before routine adoption.
Funding and Clinical Trials
Not specified in the primary meta-analysis report. The included studies varied in funding sources. Ongoing trials registered in clinical repositories should be monitored to update evolving evidence.
References
Santokh I, Fursule A, Dorasamy D, et al. Early Exclusive Enteral Feeding in Preterm Infants: A Meta-Analysis. Pediatrics. 2026. doi:10.1542/peds.2026-076045. PMID:42586559.
Additional literature consulted includes current neonatal nutrition guidelines from the American Academy of Pediatrics and Cochrane reviews on preterm feeding strategies.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.