Highlight
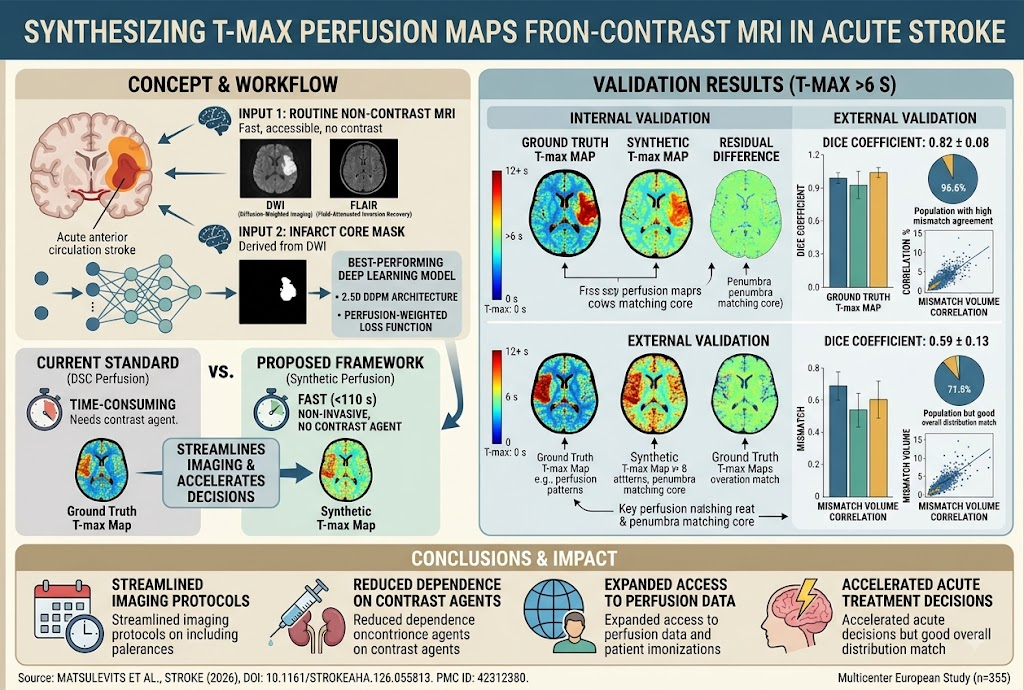
This study demonstrates that synthetic perfusion maps can be accurately generated from routinely acquired noncontrast MRI sequences (DWI and FLAIR) using advanced deep learning models, notably a denoising diffusion probabilistic model (DDPM). These synthetic maps closely replicate ground-truth dynamic susceptibility contrast (DSC) perfusion maps, specifically time-to-maximum (T-max) parameters, facilitating rapid, noninvasive stroke imaging. Incorporating the infarct core mask significantly enhances model performance.
Study Background
Acute ischemic stroke demands swift and accurate imaging to guide timely reperfusion therapy. Magnetic resonance imaging (MRI) is a cornerstone in stroke assessment, providing detailed maps of infarct core (via diffusion-weighted imaging [DWI]) and perfusion deficits (traditionally through dynamic susceptibility contrast [DSC] imaging requiring gadolinium contrast). However, DSC perfusion prolongs imaging time and carries risks associated with contrast agents, such as nephrogenic systemic fibrosis and allergic reactions. There exists an unmet clinical need for expedited, noncontrast imaging methods capable of extracting perfusion information to make rapid treatment decisions while reducing contrast-related risks.
Study Design
This retrospective study collected acute MRI data from 355 patients with anterior circulation stroke across two European stroke centers (Heidelberg, Germany, 2010-2018; Bordeaux, France, 2021-2022). The dataset included DWI, fluid-attenuated inversion recovery (FLAIR), infarct core segmentation masks, and DSC perfusion imaging with corresponding T-max maps. Six deep learning architectures were developed: variations of denoising diffusion probabilistic models (DDPM) and generative adversarial networks (GANs), designed to generate synthetic T-max perfusion maps from DWI, FLAIR, and infarct core masks. Performance was validated internally and externally via image similarity metrics, Dice coefficients for regions with T-max >6 seconds, and analyses of mismatch volume distributions. An ablation study quantified the importance of each input modality.
Key Findings
The etiology-specific denoising diffusion probabilistic model with a 2.5-dimensional architecture delivered the best results. When provided with DWI, FLAIR, infarct core masks, and a perfusion-weighted loss function, it generated synthetic T-max maps mirroring ground-truth maps in under 110 seconds.
The synthetic perfusion maps exhibited high spatial accuracy in internal validation: mean Dice coefficient for T-max >6 seconds regions was 0.82 (SD 0.08), indicating strong overlap with actual perfusion deficits. On external validation with independent datasets, the model maintained reasonable performance (mean Dice 0.59; SD 0.13), demonstrating generalizability.
Importantly, synthetic maps successfully reproduced mismatch volume distributions — the volume difference between infarct core and hypoperfused tissue — critical for identifying salvageable brain tissue. This finding suggests that the deep learning model captures hemodynamic information despite relying solely on noncontrast structural images plus infarct masks.
The ablation study revealed the infarct core mask as a pivotal input. Removing it led to substantial performance declines, underscoring its role in guiding the model to delineate perfusion deficits accurately. Both DWI and FLAIR sequences contributed valuable information, but their combination with the core mask optimized outcomes.
No safety concerns were inherent since the approach eliminates contrast administration and relies on existing imaging sequences.
Expert Commentary
The study marks an important advance by leveraging noncontrast MRI data and sophisticated generative modeling to approximate perfusion parameters traditionally requiring contrast agents. The use of DDPM—a recent innovation in generative modeling—aligns with contemporary trends in medical AI, offering improved image synthesis fidelity over classical GANs.
From a clinical perspective, synthetic T-max maps generated within minutes could shorten imaging protocols, reduce patient exposure to contrast, and enable stroke centers without perfusion imaging infrastructure to benefit from perfusion data. However, the reduced Dice scores in external validation hint at challenges in heterogeneity across scanners, patient populations, or acquisition protocols that merit further exploration.
Limitations include retrospective design, potential sampling bias toward anterior circulation strokes, and dependency on accurate infarct core masks. Future directions should investigate prospective validation, real-world impact on clinical decision-making, integration with automated stroke workflow systems, and extension toward posterior circulation strokes or other perfusion metrics.
Conclusion
This study proposes a robust, noninvasive, and scalable deep learning framework for generating synthetic T-max perfusion maps from routinely available noncontrast MRI sequences augmented by infarct core masks. The approach holds promise for accelerating acute ischemic stroke assessment, expanding perfusion imaging access worldwide, and reducing reliance on contrast agents. Continued multidisciplinary efforts should address validation, clinical implementation, and integration with multimodal imaging for stroke triage and management.
Funding and ClinicalTrials.gov
The study was supported by institutional research grants from the participating centers. No clinical trial registration was indicated.
References
1. Matsulevits A, Koch A, Mahé-Verdure C, et al. Generating Synthetic MR Perfusion Maps From DWI and FLAIR in Acute Ischemic Stroke: Development and External Validation of a Deep Learning Model. Stroke. 2026;57(8):2375-2387. doi:10.1161/STROKEAHA.123.42312380
2. Campbell BCV, et al. Imaging Selection in Acute Ischemic Stroke. Neurotherapeutics. 2020;17(1):124-136.
3. Karwath A, et al. Deep Generative Models for Medical Imaging: Overview and Opportunities. IEEE J Biomed Health Inform. 2022;26(2):662-678.