Highlight
- The combination of ibrutinib and venetoclax resulted in undetectable measurable residual disease (MRD) in 66.2% of patients versus 0% with ibrutinib alone within two years.
- Five-year progression-free survival was significantly higher with ibrutinib-venetoclax (93.9%) compared to ibrutinib alone (79.0%) and fludarabine-cyclophosphamide-rituximab (FCR) (58.1%).
- Overall survival favored ibrutinib-venetoclax, demonstrating a reduced risk of death compared to both ibrutinib monotherapy and FCR.
- Measurable residual disease-guided therapy offers an effective approach for deeper remission and potential treatment discontinuation in chronic lymphocytic leukemia (CLL).
Study Background and Disease Burden
Chronic lymphocytic leukemia (CLL) is the most common adult leukemia in Western countries, characterized by the accumulation of mature, functionally incompetent B lymphocytes. CLL has a highly variable clinical course, ranging from indolent disease requiring minimal intervention to aggressive forms necessitating intensive therapy. Traditional chemotherapy regimens such as fludarabine-cyclophosphamide-rituximab (FCR) have been the standard frontline treatment but are often associated with significant toxicity and suboptimal long-term outcomes.
The advent of targeted therapies, including ibrutinib—a Bruton’s tyrosine kinase inhibitor—and venetoclax—a BCL-2 inhibitor, transformed CLL treatment paradigms by offering highly effective, chemotherapy-free regimens. Ibrutinib monotherapy showed improved progression-free survival (PFS) compared with chemotherapy. Venetoclax, particularly combined with anti-CD20 antibodies, has demonstrated high rates of deep remission, including undetectable measurable residual disease (MRD), which is associated with superior clinical outcomes.
However, the question of whether a combination of ibrutinib and venetoclax offers superior efficacy compared to ibrutinib alone remains. MRD assessment has emerged as a powerful prognostic marker, guiding therapy duration and intensity. This trial addresses the unmet need by directly comparing ibrutinib-venetoclax combination therapy versus ibrutinib monotherapy and FCR in CLL patients, utilizing MRD-guided endpoints.
Study Design
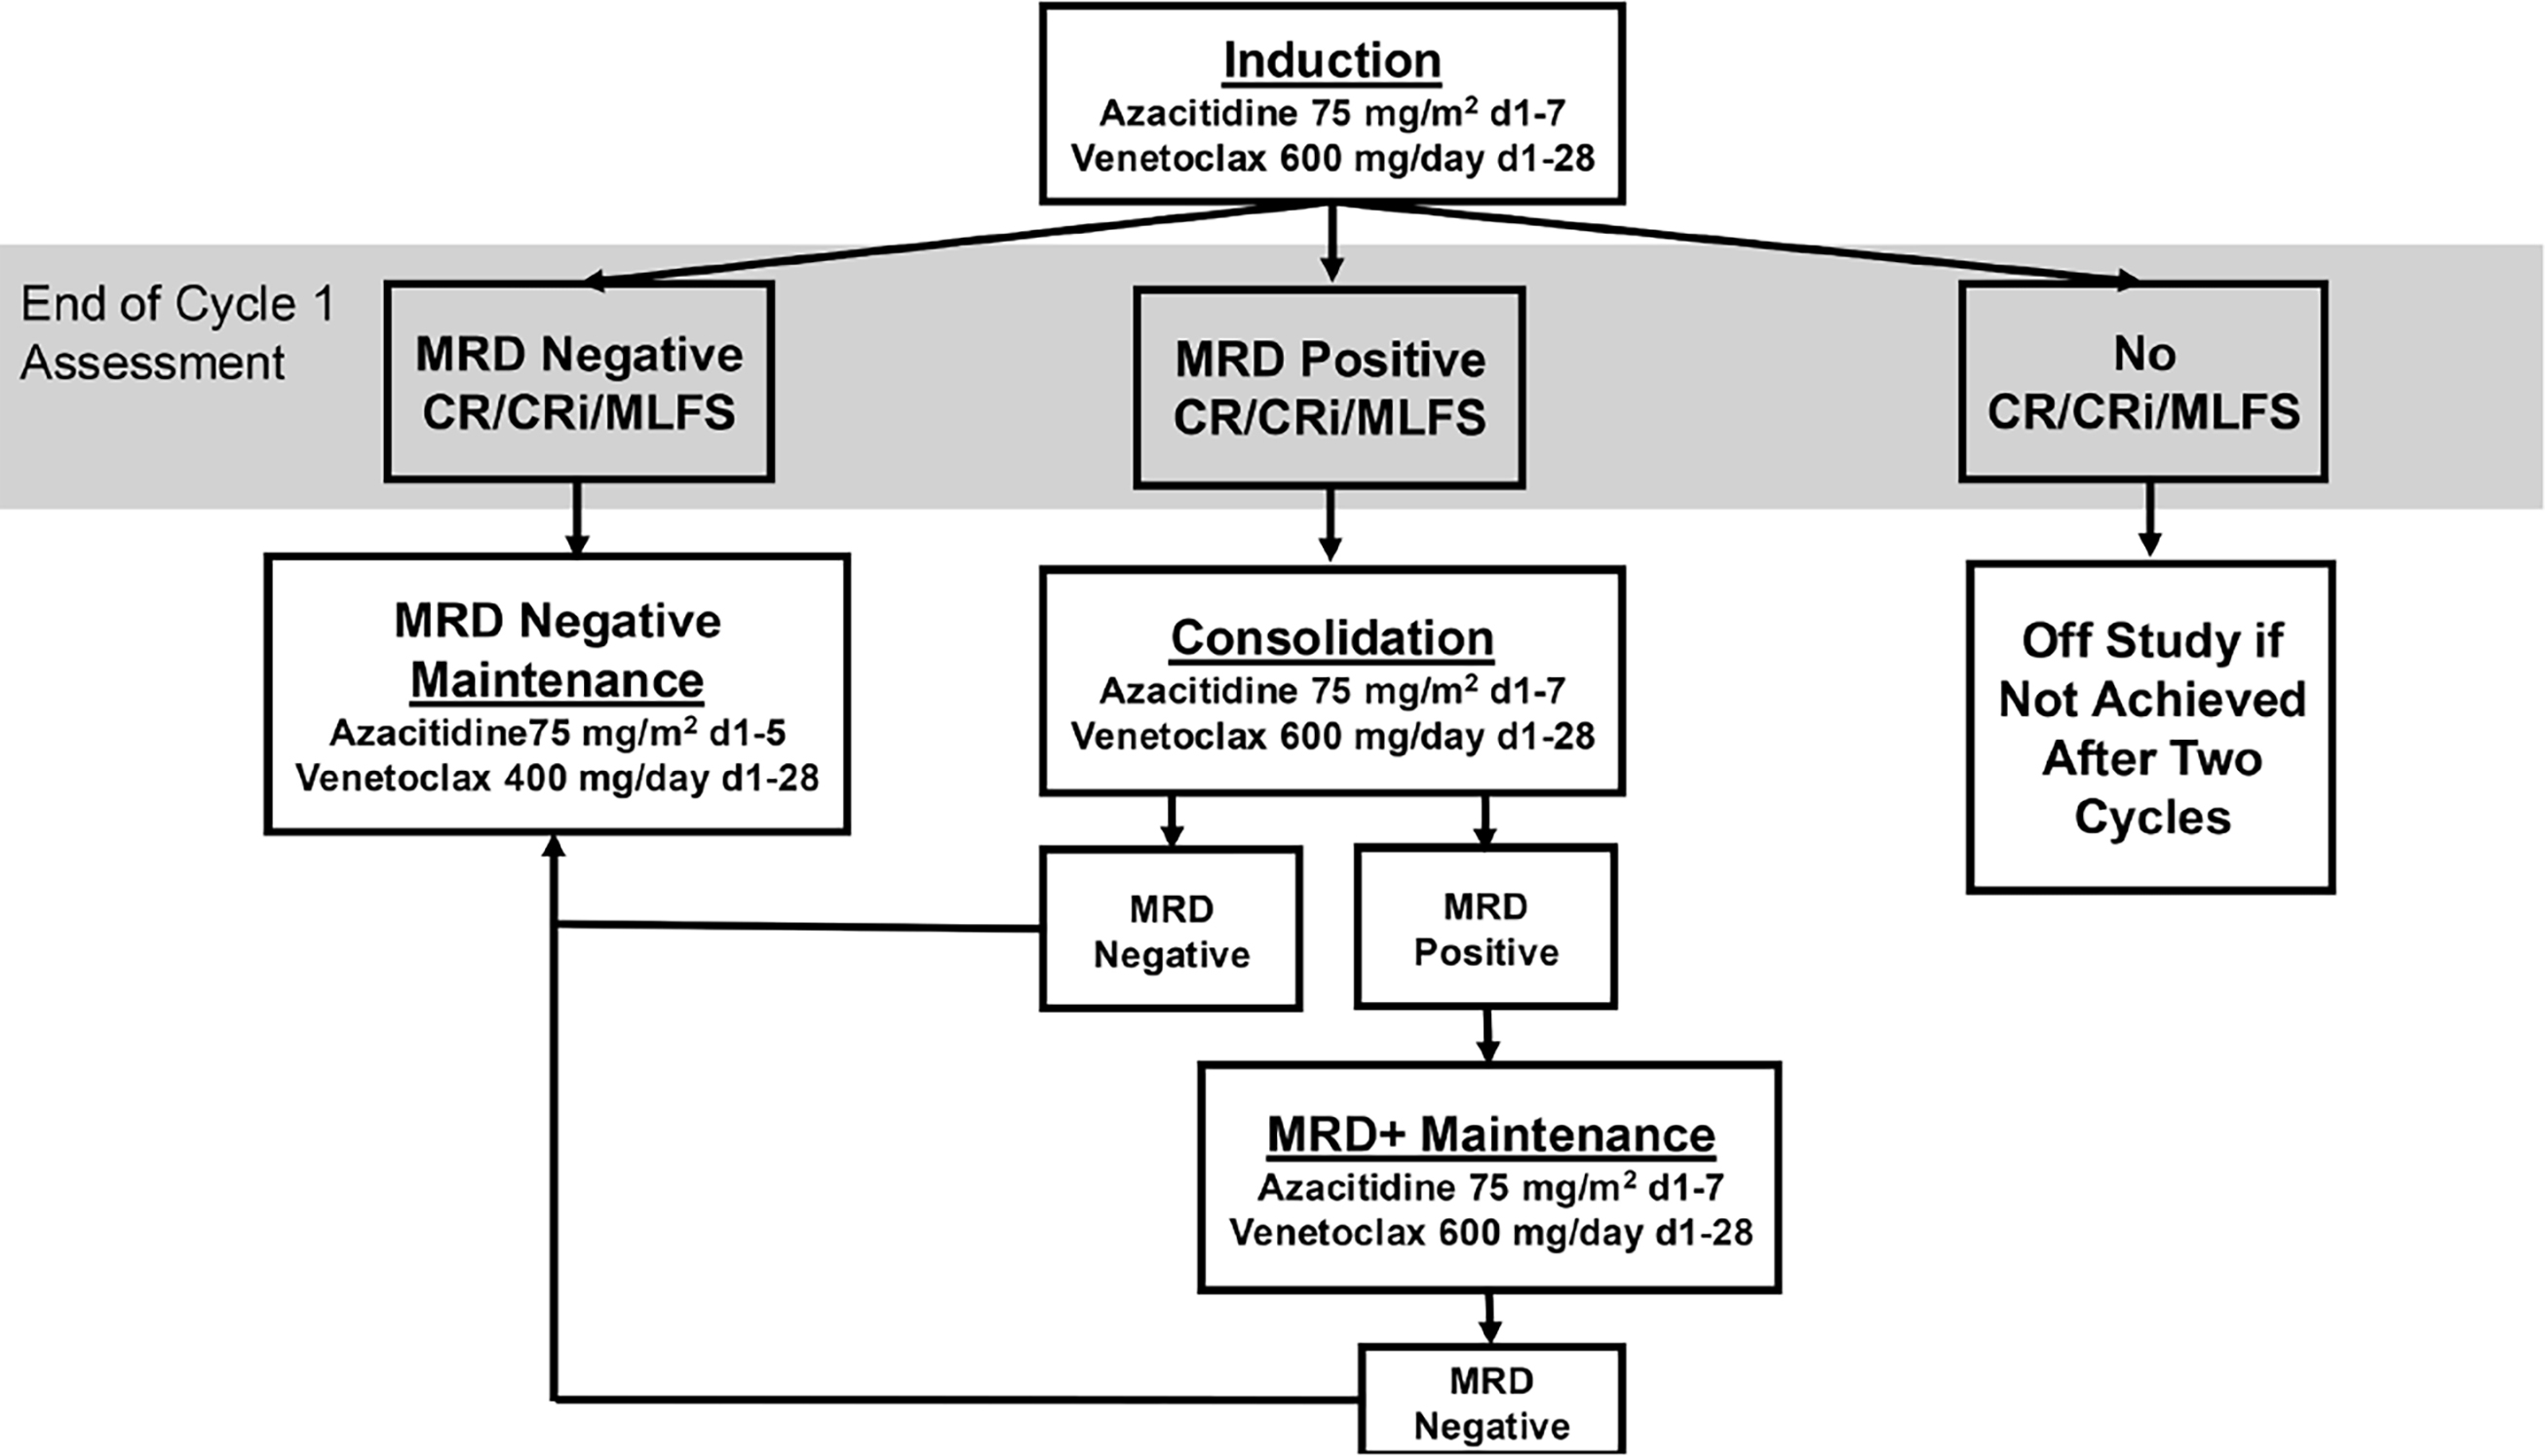
This was a phase 3, multicenter, open-label, randomized clinical trial enrolling patients diagnosed with CLL meeting criteria for treatment initiation. Participants were randomized into three arms:
1. Ibrutinib-venetoclax combination therapy
2. Ibrutinib monotherapy
3. Fludarabine-cyclophosphamide-rituximab (FCR) chemotherapy
The primary endpoints were twofold:
– The proportion of patients achieving undetectable MRD in bone marrow within 2 years comparing ibrutinib-venetoclax with ibrutinib alone.
– Progression-free survival analysis comparing ibrutinib-venetoclax against FCR.
A powered secondary endpoint evaluated progression-free survival between ibrutinib-venetoclax and ibrutinib monotherapy. Overall survival and safety profiles were additional key secondary endpoints.
Key Findings
A total of 786 patients were randomized into the study: 260 to ibrutinib-venetoclax, 263 to ibrutinib alone, and 263 to FCR. Median follow-up was 62.2 months (approximately 5 years).
- Measurable Residual Disease: Within 2 years, 66.2% (172/260) of patients receiving ibrutinib-venetoclax achieved undetectable MRD in bone marrow, compared to 0% in the ibrutinib-alone group (P<0.001) and 48.3% (127/263) in the FCR group. This demonstrates a marked advantage for the combination therapy in eradicating residual disease.
- Progression-Free Survival: Disease progression or death occurred in only 6.9% (18/260) of ibrutinib-venetoclax-treated patients, markedly lower than 22.4% (59/263) in the ibrutinib-alone group (hazard ratio [HR] 0.29; 95% confidence interval [CI], 0.17–0.49; P<0.001), and 42.6% (112/263) in the FCR group (HR 0.13; 95% CI, 0.08–0.21; P<0.001). The 5-year PFS rates were 93.9%, 79.0%, and 58.1%, respectively, underscoring prolonged clinical benefit with combination therapy.
- Overall Survival: Death occurred in 4.2% of patients in the ibrutinib-venetoclax arm, compared with 9.9% in the ibrutinib-alone group (HR 0.41; 95% CI, 0.20–0.83) and 14.8% in the FCR group (HR 0.26; 95% CI, 0.13–0.50). This survival advantage affirms the impact of combined targeted therapy on long-term outcomes.
- Safety: Sudden deaths were observed but were numerically lower in the ibrutinib-venetoclax group (3 cases) versus ibrutinib alone (8 cases) and FCR (4 cases). Overall, the toxicity profile favored the targeted therapies over chemotherapy, consistent with prior studies.
Expert Commentary
This rigorously conducted trial substantially extends prior knowledge by directly comparing frontline ibrutinib-venetoclax to ibrutinib monotherapy and FCR in CLL, with mature outcomes and a median follow-up exceeding 5 years. The prominent increase in undetectable MRD rates with combination therapy serves as a surrogate marker for the observed PFS and overall survival benefits.
These data underscore the biologic synergism between ibrutinib and venetoclax, targeting distinct pathogenic pathways—B-cell receptor signaling and apoptosis regulation—resulting in deeper remissions. The MRD-guided approach not only refines treatment effectiveness assessment but also offers a potential avenue for treatment discontinuation, thereby limiting cumulative toxicity and healthcare costs.
While the study was open-label and did not include some patients with high-risk genomic features frequently seen in clinical practice, the results are broadly generalizable to frontline CLL management. Importantly, the findings align with evolving clinical guidelines endorsing combination targeted regimens in suitable patients.
Future research is warranted to explore long-term safety, optimize duration of therapy based on MRD kinetics, and understand resistance mechanisms emerging under combined BTK and BCL-2 blockade.
Conclusion
This landmark phase 3 randomized trial demonstrates that measurable residual disease-guided therapy utilizing ibrutinib in combination with venetoclax significantly improves eradication of residual disease, progression-free survival, and overall survival compared with ibrutinib monotherapy or standard chemoimmunotherapy FCR in patients with chronic lymphocytic leukemia.
These findings position ibrutinib-venetoclax as a new frontline standard of care, offering patients deeper remission and prolonged disease control with a manageable safety profile. Adoption of MRD-driven treatment strategies promises to individualize therapy duration and improve long-term outcomes in CLL.
Continued follow-up and translational research will further cement the role of this regimen and elucidate optimal MRD monitoring protocols for personalized care pathways.
References
1. Munir T, Girvan S, Cairns DA, et al; UK CLL Trials Group. Measurable Residual Disease-Guided Therapy for Chronic Lymphocytic Leukemia. N Engl J Med. 2025 Sep 25;393(12):1177-1190. doi: 10.1056/NEJMoa2504341.
2. Wierda WG, O’Brien S, Wang X, et al. Chemoimmunotherapy with fludarabine, cyclophosphamide, and rituximab for relapsed CLL. J Clin Oncol. 2010;28(10):1756–1761.
3. Stilgenbauer S, Eichhorst B, Schetelig J, et al. Venetoclax for relapsed or refractory CLL with 17p deletion: a pooled analysis of 350 patients. Lancet Oncol. 2018;19(7):947-956.
4. Hallek M, Shanafelt TD, Eichhorst B. Chronic lymphocytic leukaemia. Lancet. 2018;391(10129):1524-1537.