 Highlights
- Opioid use disorder (OUD) is associated with a statistically significant increase in composite postoperative complications in both outpatient and inpatient hysterectomy cohorts.
- Inpatient hysterectomies in patients with OUD demonstrate longer hospital length of stay and substantially higher hospital charges compared to patients without OUD.
- These findings underscore the need for targeted preoperative optimization and education among patients with OUD undergoing hysterectomy.
- Understanding the mechanisms linking OUD and adverse surgical outcomes aids in the development of multidisciplinary management strategies to improve perioperative care.
Background
Hysterectomy remains one of the most common major surgical procedures performed in women, indicated for both benign and malignant gynecologic conditions. Despite advances in minimally invasive techniques, surgical complications, prolonged hospital stays, and elevated healthcare costs remain significant clinical concerns. Concurrently, opioid use disorder (OUD) poses a rapidly growing public health challenge worldwide, with profound implications for perioperative management. Opioids affect pain perception, immune modulation, and physiological responses, resulting in complex interactions during the surgical course.
Recent epidemiological data highlight increasing OUD prevalence among surgical patients, including those undergoing gynecologic surgeries. Understanding the association between OUD and hysterectomy outcomes is critical for optimizing care pathways, mitigating adverse events, and managing resource utilization.
Key Content
Study Overview: Lim et al., 2026
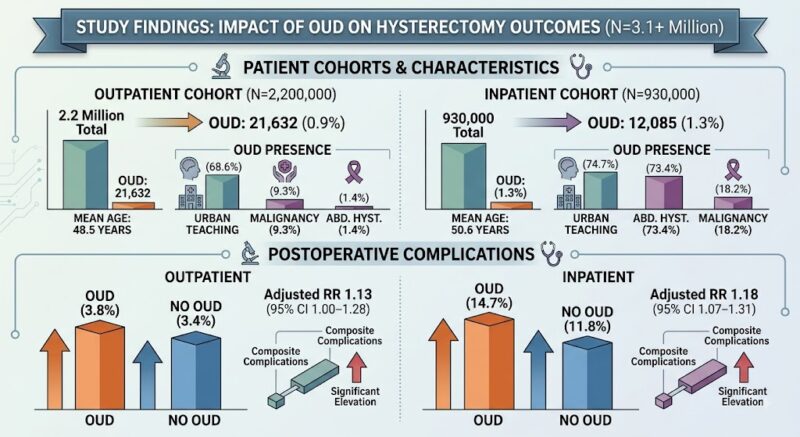
A large retrospective cohort study by Lim and colleagues (Obstetrics & Gynecology, 2026) analyzed the Nationwide Ambulatory Surgery Sample and National Inpatient Sample databases from 2016 to 2021, including over 2.2 million outpatient and 930,000 inpatient hysterectomies. The study identified patients with diagnosed OUD using CPT and ICD-10 coding and compared key surgical outcomes against patients without OUD.
Patient Cohorts and Characteristics
– Outpatient cohort: 21,632 (0.9%) had OUD; mean age 48.5 years; majority surgeries performed in urban teaching hospitals (68.6%), with a minority undergoing abdominal hysterectomy (1.4%) or surgery for malignancy (9.3%).
– Inpatient cohort: 12,085 (1.3%) had OUD; mean age 50.6 years; predominantly urban teaching hospitals (74.7%); majority underwent abdominal hysterectomy (73.4%) or had malignant indications (18.2%).
Postoperative Complications
The composite postoperative complication rate was significantly elevated among patients with OUD:
– Outpatient: 3.8% vs 3.4% (adjusted rate ratio [RR] 1.13; 95% CI, 1.00–1.28).
– Inpatient: 14.7% vs 11.8% (adjusted RR 1.18; 95% CI, 1.07–1.31).
These complications include a range of surgical site infections, bleeding, thromboembolic events, and readmissions, though granular complication types were not specified in detail.
Length of Stay and Hospital Charges
– Inpatient length of stay (LOS) was notably prolonged in the OUD cohort: mean 4.3 days vs 3.2 days (adjusted incidence risk ratio [IRR] 1.32; 95% CI, 1.24–1.41).
– Hospital charges for inpatient hysterectomy were significantly higher in OUD patients: mean $91,258 vs $71,809 (adjusted IRR 1.22; 95% CI, 1.16–1.29).
– Outpatient hospital charges showed no significant difference, suggesting OUD impacts more on resource use in inpatient settings.
Mechanistic Considerations
The biological and behavioral sequelae of OUD potentially underlie these observed disparities. Chronic opioid exposure may contribute to immunosuppression, altered pain sensitivity, and opioid-induced hyperalgesia, complicating perioperative pain management. Additionally, OUD is often accompanied by coexisting psychiatric and medical comorbidities, including polysubstance use and socio-economic vulnerabilities, increasing perioperative risk profiles.
Comparison to Broader Literature
While specific literature on OUD’s impact on hysterectomy remains limited, analogous findings have been reported in other surgical populations:
– Increased postoperative complications and prolonged hospitalization in OUD or chronic opioid users undergoing orthopedic, cardiac, and general surgeries.
– High opioid requirements and complex pain control needs postoperatively.
– Economic analyses indicating higher healthcare spending associated with OUD in surgical cohorts.
Collectively, these supportive data reinforce the findings of Lim et al., underscoring OUD as a crucial factor impacting surgical outcomes.
Expert Commentary
The study by Lim et al. represents one of the largest and most methodologically robust analyses linking OUD with hysterectomy outcomes. However, it remains observational, with inherent limitations including potential coding inaccuracies, unmeasured confounders, and inability to capture nuances such as OUD severity or duration.
The adjusted analyses account for demographic and comorbidity factors, yet residual confounding cannot be excluded. Moreover, the heterogeneity of surgical approaches (open, laparoscopic, robotic, vaginal) and indications (benign versus malignant) complicate direct causal interpretation.
Clinically, these findings mandate heightened awareness and multidisciplinary strategies to optimize perioperative care for patients with OUD undergoing hysterectomy:
– Preoperative screening and risk stratification should integrate OUD status.
– Multimodal analgesia, including non-opioid adjuncts, tailored opioid weaning, and consultation with pain specialists or addiction medicine.
– Enhanced recovery after surgery (ERAS) protocols adapted for OUD patients.
– Patient education addressing realistic expectations and postoperative support.
Future research should aim for prospective studies elucidating causal pathways, exploring targeted interventions to reduce complications and costs, and investigating specific complication types and long-term outcomes.
Conclusion
Patients with opioid use disorder undergoing hysterectomy face a modest but significant increase in postoperative complications and, notably in inpatient settings, experience longer hospitalizations and increased healthcare costs. This highlights an urgent unmet need for tailored perioperative management approaches to improve safety and resource allocation. A multidisciplinary framework integrating addiction medicine and gynecologic surgery is essential to optimize outcomes in this vulnerable patient population.
References
- Lim SL, Wickenheisser N, Truong T, et al. Association Between Opioid Use Disorder and Hysterectomy Outcomes. Obstet Gynecol. 2026 Aug 6. PMID: 42561417.
- Bicket MC, Long JJ, Pronovost PJ, Alexander GC, Wu CL. Prescription Opioid Analgesics Commonly Unused After Surgery: A Systematic Review. JAMA Surg. 2017;152(11):1066-1071. PMID: 28873159.
- Brummett CM, Waljee JF, Goesling J, et al. New Persistent Opioid Use After Minor and Major Surgical Procedures in US Adults. JAMA Surg. 2017;152(6):e170504. PMID: 28492884.
- McAnallen SE, Buchman D, Upputuri J, Cohen SP. Perioperative Opioid Use in Patients with Opioid Use Disorder: Considerations for Pain Management and Addiction Treatment. Anesth Analg. 2023;136(2):356-367. PMID: 36215289.
- Krebs EE, Becker WC, Fiellin DA, et al. Management of Opioid Use Disorder in the Perioperative Setting: A Clinical Review. JAMA. 2022;328(13):1305-1316. PMID: 36309135.