Adult Overweight and Obesity Management: Key Updates from the 2025 VA/DoD Clinical Practice Guideline
Introduction and Context
Obesity is a chronic, relapsing neurohormonal disease that contributes to cardiovascular disease, diabetes, musculoskeletal disorders, mental-health burden, and reduced quality of life. Among U.S. veterans and active-duty service members, obesity prevalence and its downstream health and readiness consequences are high, prompting the U.S. Department of Veterans Affairs (VA) and Department of Defense (DoD) to update their 2020 clinical practice guideline (CPG) for adult overweight and obesity. The updated guideline, developed by the VA/DoD Evidence-Based Practice Work Group and published in 2026 (reporting a 2025 guideline update), synthesizes evidence through 6 January 2025 and uses GRADE methodology to produce practical, patient-centered recommendations for primary care clinicians and specialty teams (Corrado et al., 2026).
This article summarizes the guideline’s rationale and key recommendations, highlights what has changed since the 2020 guidance, and offers practical advice for implementing the 2025 guidance in clinical practice—particularly for teams caring for veterans and service members.
Why the Guideline Was Updated
– Rapid growth in high-quality evidence since 2019, especially large randomized controlled trials showing dramatic weight loss with new pharmacotherapies (notably GLP‑1 receptor agonists and dual incretin agents such as tirzepatide). Key trials include the STEP program for semaglutide and SURMOUNT for tirzepatide (Wilding et al., 2021; Wilding et al., 2022).
– Expanded data on endoscopic bariatric therapies and refinements in metabolic and bariatric surgery indications and outcomes.
– A shifting clinical paradigm recognizing obesity as a chronic disease needing longitudinal, individualized therapy rather than a short-term lifestyle problem.
– Need to address veteran-specific issues: high prevalence of multimorbidity, barriers to access, weight stigma within military and veteran settings, and readiness considerations for active-duty personnel.
New Guideline Highlights
The 2025 VA/DoD CPG centers on several overarching themes:
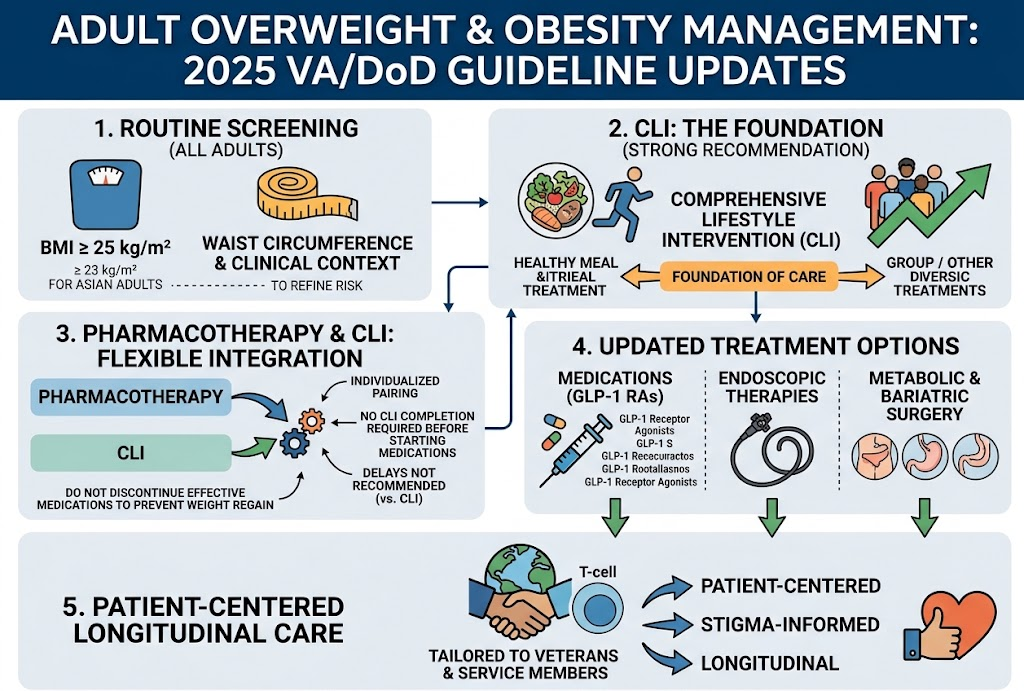
– Screening and risk assessment updated: routine screening for adults with BMI ≥25 kg/m2 (and ≥23 kg/m2 for Asian adults), with waist circumference and clinical context used to refine cardiometabolic risk.
– Comprehensive lifestyle intervention (CLI) is the foundational treatment and is strongly recommended as standard of care.
– Flexible integration of pharmacotherapy and CLI: there is no requirement to complete CLI before prescribing medications; the guideline explicitly discourages delaying effective pharmacotherapy when clinically indicated.
– Explicit recommendations on GLP‑1 receptor agonists and newer agents: the guideline recognizes robust efficacy and recommends individualized use aligned with comorbidities, risks, and patient preferences.
– Endoscopic therapies and metabolic/bariatric surgery receive updated, more granular recommendations about indications and sequencing.
– Longitudinal, stigma-informed, patient-centered care: the guideline emphasizes shared decision-making, equity, and long-term support to prevent weight regain and address social determinants.
Key takeaways for clinicians:
– Screen actively and quantify risk beyond BMI.
– Start with CLI but integrate medications early when appropriate; expect that stopping effective drugs commonly leads to weight regain.
– Use patient-centered discussion that addresses goals, side effects, costs, and expected long-term commitments.
Updated Recommendations and Key Changes (Compared with 2020)
– Screening threshold: unchanged primary BMI threshold remains ≥25 kg/m2, but the guideline now specifies an adjusted threshold for Asian adults (≥23 kg/m2) to account for higher cardiometabolic risk at lower BMI.
– Pharmacotherapy timing: 2020 emphasized CLI first; the 2025 update (Corrado et al., 2026) removes a strict sequencing requirement. Clinicians may initiate pharmacotherapy concurrently with or after starting CLI—depending on patient factors and access.
– Medication discontinuation: a new, strong recommendation discourages stopping effective antiobesity medications solely to test whether weight is maintainable without them; trials show substantial weight regain after cessation of GLP‑1 or incretin-based therapy (as noted in the clinical trials summarized by the guideline).
– New evidence incorporated: large trials of semaglutide and tirzepatide demonstrating unprecedented mean weight losses are explicitly integrated into benefit–harm assessments (Wilding et al., 2021; Wilding et al., 2022).
– Surgical and endoscopic care: updated guidance on candidacy and timing for endoscopic therapies and metabolic/bariatric surgery, with more emphasis on multidisciplinary preoperative optimization and long-term follow-up (Mechanick et al., 2013; ASGE/ASGE Task Force literature).
Table: Snapshot of major recommendation changes (textual)
– Screening: 2020 vs 2025 — 2025 clarifies Asian BMI threshold and recommends routine waist circumference measurement.
– CLI: remains foundational; 2025 strongly endorses consistent delivery in primary care and referral pathways.
– Pharmacotherapy: 2020 suggested sequencing; 2025 permits concurrent initiation and emphasizes patient preference and shared decision-making.
– Surgery/endoscopy: 2025 expands indications and stress on longitudinal pathways and access issues.
Topic-by-Topic Recommendations
Diagnosis and risk stratification
– Screening: Routine screening for overweight/obesity in all adults using BMI; use BMI ≥25 kg/m2 as the operational threshold (≥23 kg/m2 for Asian adults) to prompt risk assessment and counseling.
– Waist circumference: Measure waist circumference to refine risk (e.g., increased cardiometabolic risk at WC >40 in men and >35 in women, with ethnicity-specific considerations).
– Clinical context: Consider comorbidities (diabetes, sleep apnea, ASCVD), functional impairment, medications that contribute to weight gain, and social determinants of health when assessing urgency and treatment selection.
Comprehensive lifestyle intervention (CLI)
– Strong recommendation: CLI is the foundation—structured, multicomponent programs including dietary changes, physical activity promotion, behavioral strategies, and regular contact (often ≥12–26 weekly contact visits initially) yield clinically meaningful weight loss and must be available and offered.
– Delivery: Groups, telehealth, and digital modalities are acceptable if they reproduce the intensity and behavioral content of proven programs.
Pharmacotherapy
– Flexible initiation: No requirement to exhaust CLI before starting medication. Clinicians should individualize timing based on severity, comorbidity, patient preferences, and access.
– Evidence-based options: GLP‑1 receptor agonists (semaglutide 2.4 mg) and dual incretin agents (tirzepatide) have changed the risk–benefit calculus by producing substantial average weight loss in trials; the WG incorporates these data into conditional or strong recommendations depending on outcome and population.
– Long-term approach: The guideline emphasizes that obesity medications are often chronic therapies. Discontinuation frequently leads to weight regain; stopping effective medication should be approached cautiously and only with shared decision-making.
– Safety monitoring: Assess common adverse effects (gastrointestinal, gallbladder disease, pancreatitis risk considerations), monitor for contraindications (pregnancy, certain personal histories), and consider drug–drug interactions.
Endoscopic bariatric therapies
– Role: Endoscopic therapies (e.g., endoscopic sleeve gastroplasty) are recognized as intermediate options for patients with BMI typically in ranges where they may be alternatives to or bridges to surgery; recommendations are conditioned on local expertise, availability, and patient preference.
– Longitudinal care: Like medications and surgery, endoscopic therapy should be embedded in a program that provides CLI, nutritional monitoring, and long-term follow-up.
Metabolic and bariatric surgery
– Indications: Surgery remains highly effective for appropriate candidates (e.g., BMI ≥40 or ≥35 with significant comorbidity), with shared decision-making and multidisciplinary preoperative optimization. The guideline aligns with contemporary society statements while emphasizing veteran-specific considerations and access barriers.
– Long-term follow-up: Lifelong monitoring for nutritional deficiencies, complications, weight regain, and mental-health sequelae is required.
Special Populations and Considerations
– Veterans and active-duty service members: The guideline highlights operational readiness concerns, comorbidity patterns (e.g., PTSD, musculoskeletal injuries), and potential access challenges. It underscores stigma-informed care and the need for nonpunitive, functional assessments for readiness or fitness-for-duty decisions.
– Asian adults: Lower BMI threshold (≥23 kg/m2) to recognize higher cardiometabolic risk at lower BMI.
– Reproductive-age individuals: Counsel about pregnancy planning—most pharmacotherapies are contraindicated in pregnancy, and surgery or medication decisions require reproductive counseling.
Follow-up and outcomes monitoring
– Regular follow-up is recommended, with more intensive contact early (monthly to quarterly) and annual comprehensive reviews thereafter.
– Outcomes: Track weight, waist circumference, cardiometabolic markers (A1c, lipids, blood pressure), medication adverse effects, functional status, and quality of life.
Expert Commentary and Insights
The guideline panel comprised multidisciplinary clinicians and stakeholders. Major expert perspectives included:
– Consensus that obesity must be managed as a chronic disease with long-term therapies and follow-up. The panel emphasized integrating behavioral, pharmacologic, endoscopic, and surgical options within longitudinal care pathways.
– Appreciation for the potency of new pharmacologic agents tempered by concerns about cost, access (including formulary restrictions), long-term safety data, and equitable distribution for veterans. The WG explicitly considered resources, equity, and feasibility in formulating recommendations.
– Caution regarding medication discontinuation: Several panel members noted trial data showing weight regain after stopping GLP‑1 or incretin therapies and recommended against routine discontinuation of effective therapy.
– Controversies: Timing of medication initiation (immediate vs after CLI), the role of endoscopic interventions in community settings with variable expertise, and how best to align surgical referrals with limited capacity were highlighted as areas requiring judgment and local adaptation.
Selected quotations/paraphrases from panel discussion (paraphrased):
– “Treat obesity like a chronic cardiometabolic disease; put in place systems that allow longitudinal care and access to effective therapies.”
– “Medications are not a replacement for lifestyle support—both are needed—but they can and often should be used together when appropriate.”
– “We must address structural barriers to access within the VA/DoD systems and ensure that veterans receive stigma-free, evidence-based options.”
Practical Implications for Clinical Practice
– Screening workflow: Incorporate BMI and waist circumference into routine vitals and flag patients with BMI ≥25 (or ≥23 for Asian adults) for brief assessment and possible referral to CLI.
– Shared decision-making: Present CLI as foundational but discuss pharmacologic, endoscopic, and surgical options transparently, including expected weight-loss magnitude, side effects, cost, and long-term commitments.
– Medication initiation: Consider early pharmacotherapy for patients with significant comorbidity or when rapid weight reduction is clinically indicated, and avoid forcing a stepwise requirement to complete CLI first.
– Long-term planning: Create longitudinal care pathways (or refer to multidisciplinary clinics) that include behavioral support, medication management, surgical/endoscopic referral options, and mental-health and social support services.
– Address stigma: Train staff in stigma-informed communication; frame conversations around function, comorbidity reduction, and patient goals.
Clinical vignette (illustrative)
James, a 55-year-old veteran with BMI 33 kg/m2, hypertension, and OSA, presents wanting to lose weight. Under the 2025 VA/DoD guideline, James is offered enrollment in a structured CLI and—because of his comorbidities and high motivation—also discussing semaglutide as an adjunct. After shared decision-making about benefits, side effects, cost, and the expectation of long-term therapy, James starts CLI and semaglutide simultaneously, with plans for monthly follow-up to monitor weight, blood pressure, side effects, and glucose, and to consider surgical referral if goals are unmet or complications arise.
Research Gaps and Future Directions
The guideline identifies needs for:
– Longer-term safety and comparative-effectiveness data for GLP‑1 and dual incretin therapies, especially in populations with multimorbidity.
– Implementation research on equitable access to medications, endoscopic therapies, and surgery within VA/DoD systems.
– Models of multidisciplinary, longitudinal care that are resource-feasible for large health systems.
Bottom Line
The 2025 VA/DoD CPG reframes adult overweight and obesity care toward patient-centered, longitudinal management. CLI remains the foundation, but pharmacotherapy—particularly GLP‑1 receptor agonists and newer incretin agents—has a central, flexible role alongside endoscopic and surgical options. Clinicians should screen actively (with ethnicity-specific thresholds), use shared decision-making, plan for long-term care, and guard against abrupt discontinuation of effective therapies that commonly precipitate weight regain.
References
– Corrado RL, Raffa SD, Bauer EM, et al. Adult Overweight and Obesity Management: Updates From the 2025 U.S. Department of Veterans Affairs and U.S. Department of Defense Clinical Practice Guidelines. Ann Intern Med. 2026 Aug 25. PMID: 42636450. https://pubmed.ncbi.nlm.nih.gov/42636450/
– U.S. Department of Veterans Affairs & U.S. Department of Defense. Clinical Practice Guideline for the Management of Adult Overweight and Obesity. 2020. (VA/DoD CPG repository) https://www.healthquality.va.gov/guidelines/weight
– Wilding JPH, et al. Once-Weekly Semaglutide in Adults with Overweight or Obesity. N Engl J Med. 2021;384:989–1002.
– Wilding JPH, Batterham RL, Calanna S, et al. Once-Weekly Tirzepatide for the Treatment of Obesity. N Engl J Med. 2022;387:205–216.
– U.S. Preventive Services Task Force. Screening for Obesity in Adults: Recommendation Statement. JAMA. 2018;319(3):253–264.
– Mechanick JI, Youdim A, Jones DB, et al. Clinical Practice Guidelines for the Perioperative Nutritional, Metabolic, and Nonsurgical Support of the Bariatric Surgery Patient—2013 Update. Surg Obes Relat Dis. 2013;9(2):159–191.
– ASGE Bariatric Endoscopy Task Force. Endoluminal bariatric therapies: A critical review and procedural guidance. Gastrointest Endosc. 2015 (task force publications available via ASGE).
Note: The full VA/DoD guideline and its evidence appendix provide detailed recommendation statements, strength and certainty gradings, and the complete evidence synthesis that supports implementation in VA/DoD clinical settings.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.