Systemic Therapy for Metastatic Castration-Resistant Prostate Cancer: Key Recommendations from the ASCO Living Guideline (Version 2026.1.4)
Introduction and Context
Metastatic castration‑resistant prostate cancer (mCRPC) remains a biologically heterogeneous disease with evolving treatment options. The American Society of Clinical Oncology (ASCO) maintains a living guideline to keep recommendations current as new data appear rapidly. The most recent update—”Systemic Therapy in Patients with Metastatic Castration‑Resistant Prostate Cancer: ASCO Living Guideline, Version 2026.1.4″ (Taplin et al.)—reflects high‑impact trial results, the expanding role of molecular testing, and the growing availability of targeted radioligand therapies. This article summarizes the guideline’s core recommendations, highlights what changed from prior versions, and offers practical interpretation for clinicians.
Why an update now
– New, practice‑changing evidence since the last update includes larger real‑world and trial data for lutetium‑177‑PSMA‑617 (177Lu‑PSMA‑617), matured results for PARP inhibitors in homologous recombination repair (HRR)–altered tumors, and trials of PARP+androgen‑receptor pathway inhibitor (ARPI) combinations with mixed results.
– Rapid adoption of PSMA PET imaging and wider availability of radioligand therapy make timely guidance essential.
Intended audience
– Urologists, medical oncologists, radiation oncologists, nuclear medicine physicians, and other clinicians caring for men with advanced prostate cancer.
New Guideline Highlights
Major themes and high‑level recommendations in Version 2026.1.4:
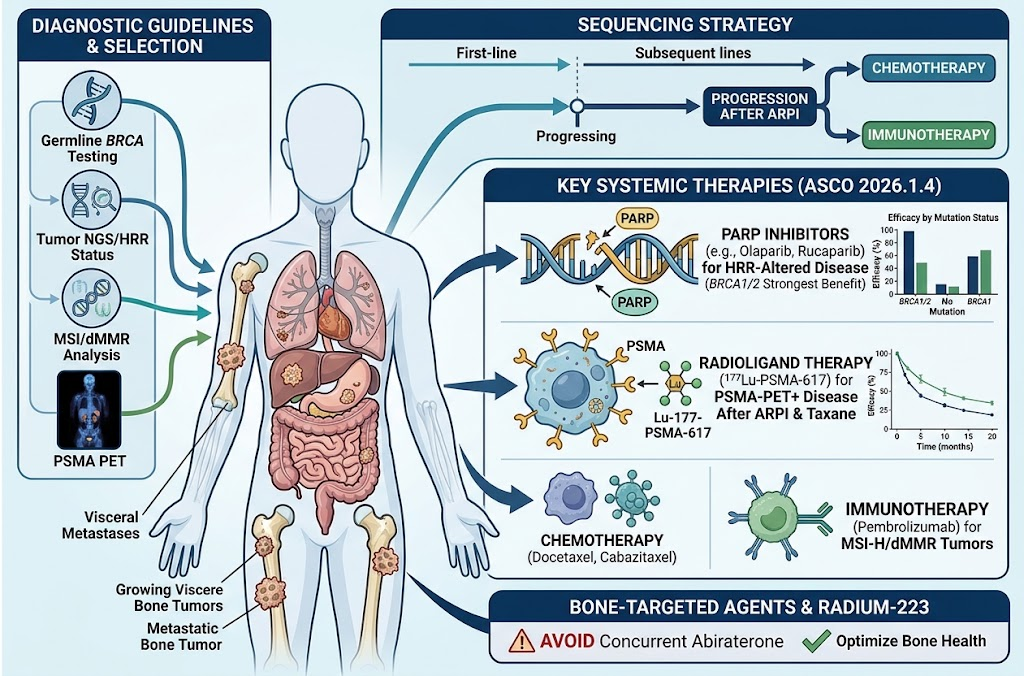
– Biomarker‑guided therapy is central. Routine tumor and germline testing for HRR gene alterations (including BRCA1/2) and testing for mismatch‑repair deficiency (dMMR)/microsatellite instability (MSI‑H) are strongly recommended.
– 177Lu‑PSMA‑617 is included as a recommended option for appropriately selected patients with PSMA‑PET‑positive disease after progression on ARPI and taxane chemotherapy (or when taxane is not appropriate), with attention to eligibility criteria used in pivotal trials.
– PARP inhibitors (olaparib or rucaparib where approved) are recommended for patients with deleterious HRR alterations, with particular strength for BRCA1/2 alterations.
– For most patients who progress after an ARPI, switching to chemotherapy (docetaxel or cabazitaxel depending on prior exposure) is preferred over switching to a second ARPI because of frequent cross‑resistance.
– Immunotherapy (pembrolizumab) is recommended for MSI‑H/dMMR tumors or other rare tumor‑agnostic indications (e.g., high tumor mutational burden in jurisdictions where approved).
– Radium‑223 remains an option for symptomatic bone‑predominant disease but should not be combined with abiraterone because of fracture risk; bone health optimization is emphasized.
Key takeaways for clinicians
– Test early and widely: somatic and germline HRR panels and MSI/dMMR status should be obtained as soon as mCRPC is diagnosed or suspected.
– Use PSMA PET to determine eligibility for PSMA‑targeted radioligand therapy; ensure imaging meets trial‑derived selection criteria.
– Sequence thoughtfully: prior treatments in the castrate‑sensitive setting (e.g., docetaxel or ARPI given up front) influence optimal next lines in the castrate‑resistant phase.
Updated Recommendations and Key Changes from Prior Versions
What changed in 2026.1.4 (highlights):
– 177Lu‑PSMA‑617: upgraded from an emerging option to a recommended therapeutic option for PSMA‑PET‑positive mCRPC after prior ARPI and taxane, reflecting mature OS benefit data and wider availability.
– Molecular testing: stronger language endorsing universal germline testing for men with metastatic prostate cancer and earlier somatic HRR testing to inform therapy selection.
– PARP inhibitors: clarified indications and stronger emphasis on the differential benefit by specific HRR genes (greater benefit in BRCA1/2 than in some non‑BRCA HRR alterations), and guidance on sequencing relative to other agents.
– Radium‑223: reinforced safety lessons from prior trials (avoid concurrent abiraterone) and detailed bone health measures to mitigate fracture risk.
Side‑by‑side summary (selected items)
– 177Lu‑PSMA‑617: Not recommended/experimental in older versions → Recommended option for PSMA‑PET‑positive, post‑ARPI and post‑taxane mCRPC (2026.1.4).
– Germline/somatic HRR testing: Encouraged → Strong recommendation for both germline and tumor HRR testing in all men with metastatic disease.
– PARP inhibitor use: Selective recommendation for HRR alterations (esp. BRCA) → Stronger evidence base and expanded approvals; guideline clarifies gene‑specific benefits.
Evidence driving changes
– VISION and subsequent confirmatory analyses established OS benefit for 177Lu‑PSMA‑617 in heavily pretreated PSMA‑PET‑positive mCRPC (Sartor et al.).
– PROfound and follow‑up analyses established the efficacy of olaparib in HRR‑altered mCRPC, particularly BRCA‑mutated disease (de Bono et al.).
– Trials of PARP plus ARPI combinations produced mixed results; benefit appears strongest in HRR‑mutated subsets, and the guideline reflects this nuance.
Topic‑by‑Topic Recommendations
Definitions and diagnostic criteria
– mCRPC: disease progression despite castrate levels of testosterone (typically <50 ng/dL) with rising PSA and/or radiographic progression while on continuous androgen deprivation therapy (ADT). The guideline uses standard Prostate Cancer Working Group criteria for progression.
Molecular testing and imaging (strong recommendations)
– Germline testing: Offer germline testing for BRCA1/2 and other inherited cancer predisposition genes to all men with metastatic prostate cancer (reflects implications for therapy and familial risk).
– Somatic tumor testing: Perform next‑generation sequencing (NGS) panel for HRR genes (BRCA1, BRCA2, ATM, PALB2, CHEK2, CDK12, etc.) on metastatic tissue or circulating tumor DNA where tissue is unavailable.
– MSI/dMMR testing: Test tumors for dMMR/MSI‑H to identify candidates for pembrolizumab.
– PSMA PET: Recommended to determine eligibility for 177Lu‑PSMA‑617, using the same positivity criteria used in pivotal trials (intense PSMA uptake in metastatic lesions without discordant PSMA‑negative/FDG‑positive disease).
First‑line systemic therapy for mCRPC (when castration‑resistant disease first appears)
– If the patient has neither received an ARPI nor docetaxel in the castrate‑sensitive setting: options include an ARPI (abiraterone, enzalutamide, apalutamide where indicated) or docetaxel depending on presence of symptoms, disease burden, and patient fitness. (Recommendation strength: conditional to strong depending on comorbidities and prior exposures.)
– If prior ARPI was used earlier (in the castrate‑sensitive setting) and progression occurs, chemotherapy (docetaxel if not previously given; otherwise cabazitaxel) is generally preferred over switching to another ARPI.
Subsequent lines and sequencing
– After progression on an ARPI and docetaxel: consider 177Lu‑PSMA‑617 for PSMA‑PET‑positive patients (strong recommendation where available and eligible), cabazitaxel, PARP inhibitors for HRR‑mutated disease, clinical trials, or immunotherapy for MSI‑H.
– For patients who have progressed after ARPI but not yet received chemotherapy: docetaxel is preferred to switching to a second ARPI (CARD trial showed superior outcomes for chemotherapy over ARPI swap in this setting).
– Cabazitaxel is preferred over ARPI re‑challenge in patients previously treated with docetaxel and ARPI who now require further systemic therapy (based on randomized evidence of benefit in this setting).
Targeted therapies and biomarkers
– PARP inhibitors (olaparib, rucaparib): Recommended for mCRPC with deleterious/suspected deleterious BRCA1/2 alterations; conditional benefit for certain non‑BRCA HRR alterations (e.g., PALB2) and less consistent benefit for ATM and CDK12. (Recommendation strength: strong for BRCA1/2; conditional for others.) [PROfound trial]
– 177Lu‑PSMA‑617: Recommend for PSMA‑PET‑positive patients with progression after ARPI and taxane chemotherapy (or when taxane not appropriate), provided patients meet the imaging and organ‑function criteria used in pivotal trials. (Recommendation strength: strong where accessible.) [VISION trial]
– Immune checkpoint blockade (pembrolizumab): Recommend for MSI‑H/dMMR tumors or other approved tumor‑agnostic indications.
Bone‑targeted agents and radium‑223
– Continue ADT in all men; use bone‑protective agents (denosumab or zoledronic acid) to reduce skeletal complications when indicated.
– Radium‑223: Reserve for symptomatic, bone‑predominant disease after other options; do not combine with abiraterone due to increased fracture risk; ensure bone health optimization and consider concurrent bisphosphonate/denosumab.
Supportive care and survivorship
– Early assessment and management of pain, mobility, and bone health.
– Counseling regarding fertility, sexual health, and family genetic implications when germline testing identifies pathogenic variants.
Expert Commentary and Insights
Panel perspectives
– The ASCO panel emphasizes a precision‑medicine approach: test early, match therapies to biomarkers, and sequence agents to avoid predictable cross‑resistance (e.g., ARPI to ARPI swaps).
– There is strong consensus that PSMA PET is not merely a staging tool but a gatekeeper for PSMA‑targeted therapy eligibility; however, access and variability in imaging interpretation remain challenges.
Key controversies and areas of uncertainty
– PARP inhibitor combinations: Trials of PARP+ARPI combinations have produced variable results. The panel notes the strongest evidence for PARP in HRR‑mutant disease; routine use of PARP+ARPI in unselected patients is not recommended until more consistent survival data and biomarker strategies are available.
– Optimal sequencing of cabazitaxel versus 177Lu‑PSMA‑617: No head‑to‑head randomized data exist; decisions should be individualized by prior therapies, PSMA‑PET status, organ function, symptoms, and patient preference.
– Access and cost: Novel agents (radioligands, PARP inhibitors) pose affordability and availability challenges; the guideline stresses equity considerations and the role of clinical trials.
Future directions highlighted by the panel
– Better predictive biomarkers to identify which non‑BRCA HRR alterations confer meaningful PARP sensitivity.
– Prospective, randomized comparisons of sequencing strategies (e.g., cabazitaxel vs 177Lu‑PSMA‑617), and trials of combinations with manageable toxicity profiles.
Practical Implications for Clinical Practice
Applying the guideline in clinic
– At the time of mCRPC diagnosis: order germline testing and tumor NGS for HRR genes; perform MSI/dMMR testing; consider PSMA PET if 177Lu‑PSMA‑617 might be an option.
– For a patient progressing on first‑line ARPI: avoid ARPI re‑challenge; consider docetaxel if chemotherapy‑naïve, or cabazitaxel/177Lu‑PSMA‑617/PARP inhibitor per biomarker profile.
Fictional vignette
– John M., a 68‑year‑old man with prior ADT + enzalutamide in the castrate‑sensitive setting, now presents with radiographic progression and rising PSA on castrate testosterone. NGS of metastatic biopsy shows BRCA2 loss; PSMA PET demonstrates intense PSMA uptake without visceral discordant disease. According to ASCO 2026.1.4, John is a candidate for a PARP inhibitor (olaparib) given BRCA2 loss; if he had already received chemotherapy and remained PSMA‑PET‑positive, 177Lu‑PSMA‑617 would be an alternate option. Germline testing is recommended to determine hereditary implications for his relatives.
Monitoring and toxicity management
– PARP inhibitors: monitor for anemia, nausea, fatigue; hematologic monitoring per label.
– 177Lu‑PSMA‑617: monitor for hematologic toxicity, xerostomia, and renal function.
– Taxanes: manage neutropenia (growth factor support per guidelines), neuropathy, and fluid retention.
References
(Selected key sources cited by the ASCO panel and discussed here)
1. Taplin ME, Parikh RA, Rumble RB, et al. Systemic Therapy in Patients with Metastatic Castration‑Resistant Prostate Cancer: ASCO Living Guideline, Version 2026.1.4. J Clin Oncol. 2026. doi:10.1200/JCO-26-01898. PMID:42561262.
2. de Bono J, et al. Olaparib for metastatic castration‑resistant prostate cancer. N Engl J Med. 2020;382:2091–2102. doi:10.1056/NEJMoa1911440.
3. Sartor O, et al. Lutetium‑177‑PSMA‑617 for metastatic castration‑resistant prostate cancer. N Engl J Med. 2021;385:1091–1103. doi:10.1056/NEJMoa2107322.
4. de Bono J, et al. Prednisolone and cabazitaxel in mCRPC (TROPIC). N Engl J Med. 2010;364:1995–2005. doi:10.1056/NEJMoa1010961.
5. de Wit R, et al. Cabazitaxel vs an alternate androgen‑targeted approach in mCRPC (CARD): Lancet. 2021. (CARD trial shows superiority of cabazitaxel over ARPI switch in appropriate patients.)
6. ERA‑223 trial investigators. Increased fracture risk with radium‑223 combined with abiraterone in mCRPC: implications for bone health management. (See trial publications and regulatory communications.)
7. NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for Prostate Cancer (latest version); European Association of Urology (EAU) Guidelines on Prostate Cancer (latest version).
Note on evidence and updates
ASCO’s living guideline model means recommendations will continue to evolve as new randomized evidence and longer follow‑up become available. Clinicians should consult the live ASCO guideline page for the most current recommendations and the full evidence tables.
Bottom line
The 2026 ASCO living guideline synthesizes an era of precision systemic therapy for mCRPC: early and comprehensive molecular testing, appropriate use of PARP inhibitors in HRR‑mutant disease, judicious use of chemotherapy based on prior exposures, and incorporation of 177Lu‑PSMA‑617 for PSMA‑PET‑positive patients. While important questions about optimal sequencing and combinations remain, the guideline gives clinicians a practical, evidence‑based framework for delivering personalized care to men with advanced prostate cancer.
Full citations and further reading
Readers should consult the full guideline (Taplin et al., J Clin Oncol 2026) and cited pivotal trials (PROfound, VISION, TROPIC, CARD) for detailed trial eligibility, endpoints, and safety profiles before applying recommendations to individual patients.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.