Reevaluating Menopausal Estrogen Therapy: Implications for Breast Cancer Risk Reduction
Highlight
- Menopausal estrogen-only therapy in women post-hysterectomy is associated with a statistically significant reduction in breast cancer risk among low-risk and BRCA mutation carriers.
- A meta-analysis of 10 randomized controlled trials (RCTs) involving over 14,000 women demonstrated a 23% relative risk reduction of breast cancer with estrogen alone versus placebo.
- A prospective cohort study showed a markedly lower 15-year cumulative breast cancer incidence in BRCA mutation carriers using estrogen-only menopausal hormone therapy compared with nonusers.
- Clinical counseling for women considering hysterectomy should integrate discussions on breast and endometrial cancer risks, cardiovascular disease, and alternative uterine-sparing strategies.
Study Background
Menopausal hormone therapy (MHT) has historically been scrutinized for its association with breast cancer risk, particularly with combined estrogen-progestin regimens. However, the role of estrogen-only therapy in women who have undergone hysterectomy remains less clearly defined. Given the substantial morbidity of breast cancer worldwide and the unmet need for preventive strategies in susceptible populations, understanding the nuanced risk modulation by menopausal estrogen therapy is critical. Furthermore, women carrying pathogenic BRCA1 and BRCA2 variants face significantly elevated lifetime breast cancer risks, raising important considerations for hormone therapy post-oophorectomy or hysterectomy.
Study Design
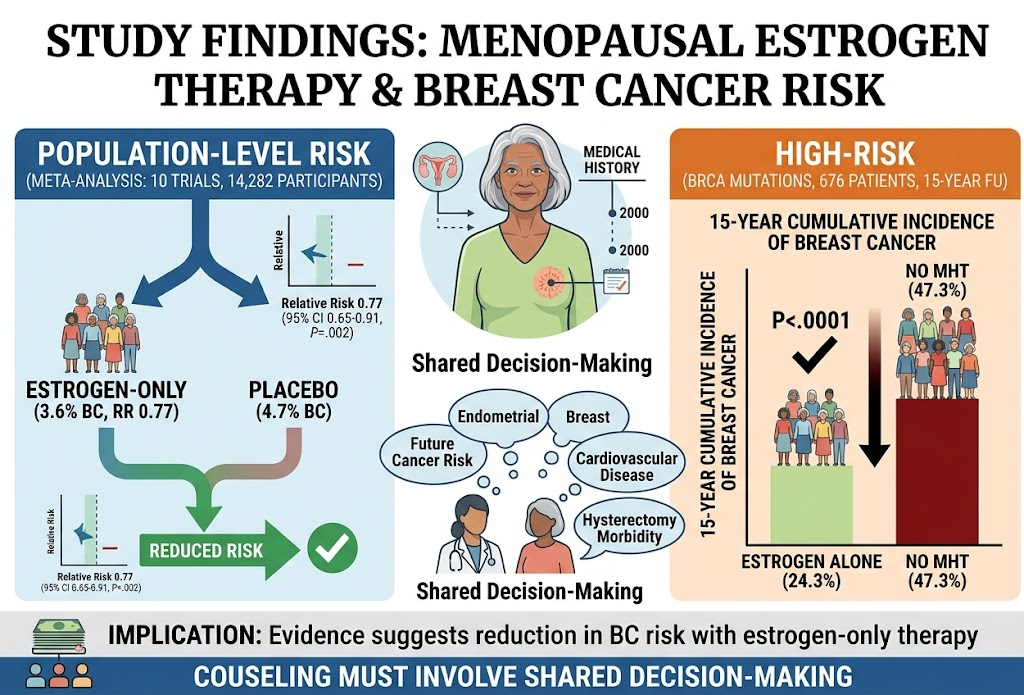
Two key types of evidence frame current understanding. First, a meta-analysis encompassing 10 randomized trials comparing menopausal estrogen therapy alone to placebo enrolled 14,282 women at population-level breast cancer risk. Intervention involved estrogen-only therapy, generally prescribed to patients post-hysterectomy to mitigate menopausal symptoms.
Second, a matched prospective cohort study enrolled 676 women with pathogenic BRCA mutations and intact breast tissue who used menopausal hormone therapy regimens, stratified by estrogen-only therapy versus no hormone use. This study assessed 15-year cumulative breast cancer incidence to elucidate long-term effects in a high-risk genetic cohort.
Key Findings
The meta-analysis reported that 3.6% of women randomized to estrogen-only therapy developed breast cancer compared with 4.7% in the placebo groups, yielding a relative risk (RR) of 0.77 (95% CI, 0.65-0.91; P = .002). This represents a 23% reduction in breast cancer incidence attributable to estrogen therapy alone, challenging prior assumptions that all estrogen exposures augment breast cancer risk.
In the BRCA mutation cohort, estrogen-only MHT users had a 15-year cumulative breast cancer incidence of 24.3%, substantially lower compared to 47.3% among matched nonusers (P < .0001). This striking difference underscores potential beneficial effects of estrogen therapy on breast tissue carcinogenesis pathways in genetically predisposed women.
The safety profile of estrogen-only therapy in these analyses was consistent with prior data in post-hysterectomy populations, with no new adverse signals. However, these studies predominantly involved estradiol or conjugated equine estrogens at typical menopausal doses.
Expert Commentary
The findings presented by Kaunitz and Wright merit careful interpretation in clinical practice. Estrogen-only therapy appears to confer breast cancer risk reduction rather than elevation in women without a uterus, potentially reflecting complex hormonal milieu alterations and breast tissue receptor modulation. This phenomenon may not extrapolate to combined estrogen-progestin therapy, which remains associated with increased breast cancer incidence.
Among women harboring BRCA mutations, the marked reduction in incidence with estrogen-only MHT suggests a paradigm shift in counseling post-oophorectomy or hysterectomy hormone management. Nonetheless, absence of randomized trial data specifically in this population demands cautious application and underlines the importance of individualized treatment decisions.
Limitations include varying hormone formulations and doses, potential residual confounding in observational cohorts, and the need for mechanistic studies to elucidate biological pathways. Moreover, the balance of risks including endometrial cancer (which estrogen-only therapy augments in women with a uterus), cardiovascular events, and other morbidities must be accounted for.
Conclusion
Current evidence indicates that menopausal estrogen-only therapy after hysterectomy may reduce breast cancer risk in both average-risk women and those with high-risk BRCA mutations. This challenges established paradigms and opens avenues for tailored hormone therapy approaches. Until confirmatory data from randomized trials in high-risk populations are available, clinical decision-making should employ shared decision-making frameworks. Conversations must address the comprehensive risk-benefit profile, including breast and endometrial cancer risks, cardiovascular implications, and the morbidity associated with hysterectomy. Offering uterine-sparing alternatives when appropriate may preserve options for safer hormone therapy regimens.
Adequate patient education, precise risk stratification, and personalized hormone management strategies remain pivotal for optimizing long-term outcomes in menopausal women at risk for breast cancer.
Reference
Kaunitz AM, Wright JD. Menopausal Estrogen Therapy and Risk of Breast Cancer. Obstet Gynecol. 2026 Aug 13. doi: 10.1097/AOG.0000000000006397. Epub ahead of print. PMID: 42594383.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.