Recurrent Severe Hypertensive Disorders in Pregnancy: Evaluating Risks and Outcomes for Future Pregnancies
Highlight
- Severe hypertensive disorders of pregnancy (HDP), including preeclampsia with severe features, HELLP syndrome, and eclampsia, have substantial recurrence risks in subsequent pregnancies.
- The highest recurrence risk is associated with severe HDP manifesting before 28 weeks of gestation, conferring up to a 23-fold increased risk of severe HDP recurrence.
- While recurrent HELLP syndrome and eclampsia occur less frequently, individuals with prior history face significantly elevated relative risks.
- Findings provide a critical evidence base to guide counseling and risk stratification for patients with a history of severe HDP.
Study Background
Hypertensive disorders of pregnancy (HDP) remain one of the leading causes of maternal and perinatal morbidity and mortality worldwide. Among these, severe preeclampsia, HELLP syndrome (Hemolysis, Elevated Liver enzymes, and Low Platelet count), and eclampsia represent the most critical clinical phenotypes associated with adverse outcomes such as preterm delivery, maternal end-organ damage, and increased risk of future cardiovascular disease. Despite this, data on recurrence rates of severe HDP are inconsistent, limiting effective clinical counseling and planning for future pregnancies. This study fills an essential gap by quantifying recurrence risks based on an extensive U.S. inpatient database, stratified by severity and gestational age at onset in the index pregnancy.
Study Design
This retrospective cohort study utilized the Premier Inpatient database, encompassing patient records from October 2015 through December 2020. Inclusion criteria restricted to individuals with at least two pregnancies during the study period, enabling longitudinal assessment. Classification of HDP was based on International Classification of Diseases, Tenth Revision (ICD-10) codes, distinguishing between severe phenotypes, including preeclampsia with severe features, superimposed preeclampsia on chronic hypertension, HELLP syndrome, and eclampsia. The principal outcomes were the absolute risk and relative risk (RR) of developing severe HDP in a subsequent pregnancy, analyzed via multivariable risk regression. Risk estimates were further stratified by severity and timing of HDP in the index pregnancy, especially focusing on early onset before 28 weeks gestation.
Key Findings
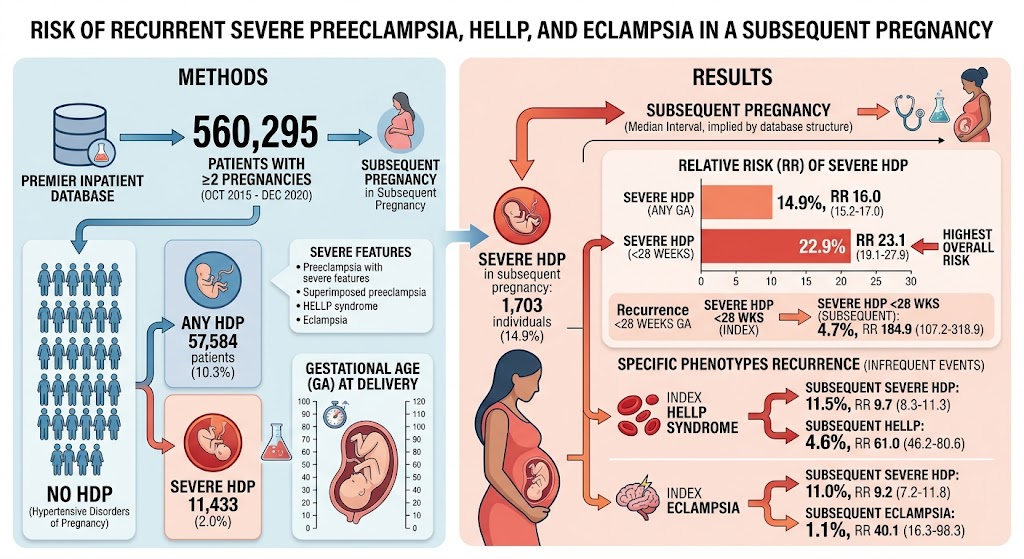
The cohort comprised 560,295 patients with at least two pregnancies; among them, 57,584 (10.3%) had any HDP during the first observed (index) pregnancy, while 11,433 (2.0%) experienced severe HDP.
In total, 1,703 (14.9%) of those with severe HDP in the index pregnancy had recurrence in a subsequent pregnancy. Patients with severe HDP had a markedly increased risk of recurrent severe HDP compared to those without HDP initially (14.9% versus baseline; RR 16.0, 95% CI 15.2–17.0). Notably, the highest risk was observed in patients with early-onset severe HDP before 28 weeks gestation, with a recurrence risk of 22.9% (RR 23.1, 95% CI 19.1–27.9).
Recurrent early-onset severe HDP before 28 weeks reached a risk of 4.7% with a dramatic relative risk of 184.9 (95% CI 107.2–318.9), underscoring the persistence of severe phenotypes in subsequent pregnancies.
Further, prior HELLP syndrome and eclampsia conferred risks of recurrent severe HDP at 11.5% (RR 9.7, 95% CI 8.3–11.3) and 11.0% (RR 9.2, 95% CI 7.2–11.8), respectively. Although recurrence of HELLP syndrome (4.6%, RR 61.0) and eclampsia (1.1%, RR 40.1) was infrequent, these relative risks indicate a substantial elevation compared with baseline, alerting clinicians to careful surveillance in these high-risk groups.
The study elucidates that both timing and severity of HDP in the index pregnancy critically predict recurrence risk, with early-onset severe HDP representing a key marker for heightened vigilance.
Expert Commentary
This comprehensive analysis leverages a large, nationally representative database to address a clinically important question: the risk of recurrent severe hypertensive disorders in pregnancy. The findings reinforce previous smaller studies while providing granular risk stratification by gestational age and HDP phenotype, which is invaluable for clinical counseling.
Importantly, the exceptionally high relative risk observed for early-onset severe HDP recurrence suggests a potential shared pathophysiologic mechanism, possibly linked to placental maladaptation, endothelial dysfunction, or genetic predisposition. This aligns well with current understanding but highlights a need for focused research towards predictive biomarkers and targeted prophylaxis.
Limitations include reliance on ICD-10 coding, which may under- or misclassify HDP phenotypes. The retrospective design precludes assessment of modifiable risk factors between pregnancies, such as interpregnancy interval, weight control, or aspirin use. Moreover, the dataset’s inpatient nature may not capture less severe presentations managed outpatient. Generalizability to populations outside the United States warrants caution.
Nevertheless, these results provide a critical tool for individualized risk assessment and shared decision-making. Future guidelines may incorporate this evidence to refine recommendations on surveillance intensity, timing of delivery, and preconception counseling.
Conclusion
This large U.S. cohort study defines the recurrence risk of severe hypertensive disorders of pregnancy as substantial, especially when the index pregnancy involved early-onset severe disease. Women with prior severe HDP, HELLP syndrome, or eclampsia represent high-risk groups requiring close monitoring and tailored obstetric management in subsequent pregnancies.
Clinicians should counsel patients on these quantified risks to inform pregnancy planning and optimize maternal-fetal outcomes. Further prospective studies are needed to explore mechanisms, preventative strategies, and interventions that may mitigate this recurrence risk.
Funding and ClinicalTrials.gov
The original study does not specify funding sources. Given its retrospective nature, no clinical trial registration applies.
References
1. Trawick E, Kucirka LM, Fuller M, et al. Risk of Recurrent Severe Preeclampsia, HELLP Syndrome, and Eclampsia in a Subsequent Pregnancy. Obstet Gynecol. 2026 Aug 20; PMID: 42623674.
2. American College of Obstetricians and Gynecologists’ Task Force on Hypertension in Pregnancy. Hypertension in Pregnancy. Obstet Gynecol. 2013;122(5):1122-1131.
3. Sibai BM, Mercer BM, Sarinoglu C. Severe preeclampsia in the second trimester: recurrence risk and long-term prognosis. Am J Obstet Gynecol. 1991;165(6 Pt 1):1583-1588.
4. Rana S, Lemoine E, Granger JP, Karumanchi SA. Preeclampsia: Pathophysiology, Challenges, and Perspectives. Circ Res. 2019;124(7):1094-1112.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.