Highlight
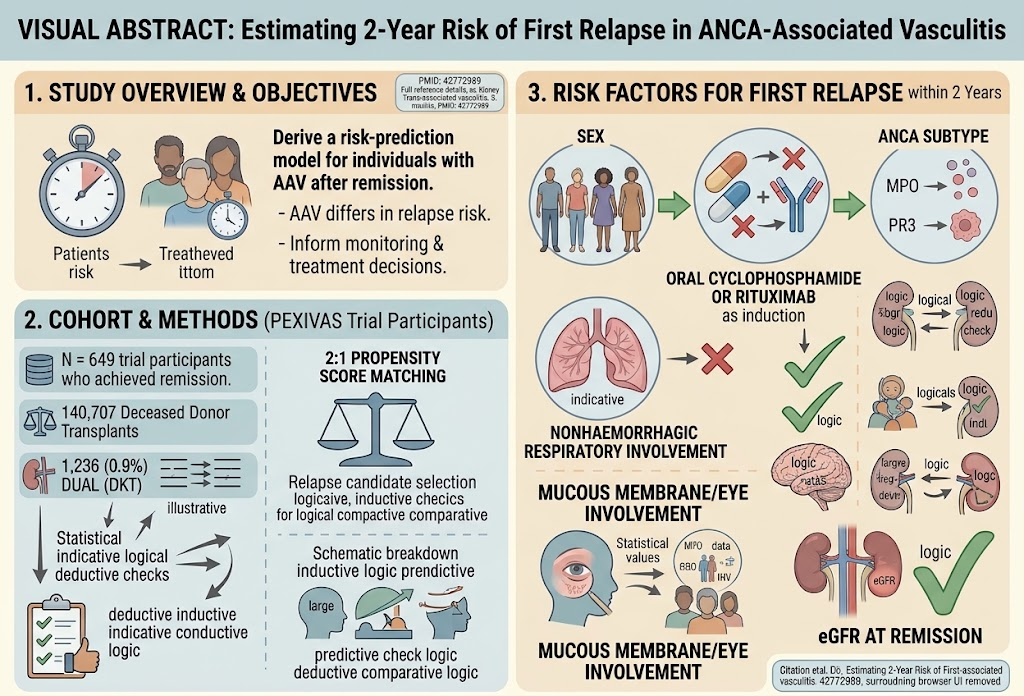
• A novel risk prediction model estimates the 2-year risk of first relapse following remission in patients with ANCA-associated vasculitis (AAV).
• The model incorporates clinical factors including sex, induction therapy type, ANCA subtype, organ involvement at presentation, and kidney function at remission.
• Validation within the PEXIVAS trial population demonstrates good discrimination (Harrell’s C-index ~0.71) and calibration, supporting its potential use in clinical decision-making.
• The model awaits external validation before widespread clinical adoption but offers a personalized approach to guide monitoring intensity and treatment strategies.
Study Background
Antineutrophil cytoplasmic antibody (ANCA)-associated vasculitis (AAV) is a rare, severe autoimmune disease characterized by small- to medium-vessel inflammation affecting multiple organs, notably the kidneys and respiratory tract. Despite current immunosuppressive therapies achieving remission, relapses occur frequently and contribute significantly to morbidity, mortality, and treatment-related toxicity. The heterogeneous relapse risk among patients challenges clinicians in tailoring maintenance therapy duration and intensity, balancing relapse prevention against drug side effects.
Reliable individual risk stratification for early relapse post-remission is an unmet clinical need. Existing predictors based on clinical experience lack quantification and validation, limiting practical application. The Plasma Exchange and Glucocorticoids for Treatment of ANCA-Associated Vasculitis (PEXIVAS) trial provides a rich dataset to derive a risk prediction model to estimate the likelihood of relapse within two years after achieving remission.
Study Design
This post hoc analysis used data from the PEXIVAS trial, which enrolled patients with AAV exhibiting either significant renal impairment (estimated glomerular filtration rate [eGFR] <50 mL/min/1.73 m2) or diffuse alveolar hemorrhage. All participants had attained disease remission following induction treatment, which included plasma exchange and a reduced glucocorticoid regimen.
The primary endpoint was the first relapse occurring within two years after remission. Candidate predictor variables were selected based on prior literature, then refined through statistical methods including least absolute shrinkage and selection operator (LASSO) regression and time-to-event analyses. Model performance metrics comprised discrimination by concordance statistics (Harrell’s C-index) and calibration assessed by slope. Multiple sensitivity analyses ensured model stability.
Key Findings
The analysis included 649 participants, with 100 experiencing relapse within 2 years post-remission. The finalized risk estimation model incorporated six key predictors:
- Sex (male vs. female)
- Type of induction therapy (oral cyclophosphamide or rituximab)
- ANCA subtype (proteinase 3 [PR3] vs. myeloperoxidase [MPO])
- Nonhaemorrhagic respiratory involvement at presentation
- Mucous membrane or eye involvement at presentation
- eGFR at remission
This model achieved an optimism-corrected Harrell’s C-index of 0.709 (95% CI: 0.707–0.710), indicating moderate discrimination ability. The calibration slope was 0.99 (95% CI: 0.65–1.34), reflecting agreement between predicted and observed relapse probabilities.
The inclusion of induction agent type suggests treatment choices influence relapse risk, possibly due to differential mechanisms of action or remission depth. ANCA subtype reaffirmed its prognostic value, with PR3-ANCA patients generally exhibiting higher relapse rates. The incorporation of specific organ involvement highlights heterogeneous disease manifestations as relapse predictors. Renal function at remission remains a pivotal marker for ongoing disease activity and recurrence risk.
Expert Commentary
This study marks an important step toward personalized medicine in AAV by quantitatively estimating relapse risk using routine clinical parameters from a large, well-characterized randomized trial cohort. The choice of variables reflects biologically plausible and clinically accessible markers, enhancing translation to practice.
While the model’s discrimination is moderate, it compares favorably to existing relapse prediction approaches, which often lack robust validation. The observed calibration suggests clinicians can rely on model-generated probabilities for decision-making. However, inherent limitations exist, including the post hoc design and restriction to a selected high-risk PEXIVAS population, which may limit generalizability to patients with milder disease or different demographics.
External validation in diverse cohorts is crucial before wide clinical implementation. Future iterations might integrate novel biomarkers or imaging to improve predictive accuracy. Importantly, tailored relapse risk predictions could refine maintenance therapy duration, intensity, and monitoring frequency, potentially reducing overtreatment and adverse effects without compromising disease control.
Conclusion
The derived risk prediction model from the PEXIVAS trial offers a pragmatic tool to estimate the 2-year risk of first relapse in AAV patients achieving remission. By combining clinical features, treatment regimen, and kidney function, it enhances individualized risk stratification, informing surveillance strategies and therapeutic decisions.
Pending external validation, this model has the potential to optimize patient outcomes by balancing relapse prevention and treatment toxicity, a pivotal challenge in managing systemic vasculitis. Integration into clinical workflows and electronic health systems could further promote its utility and support evidence-based precision care in AAV.
Funding and ClinicalTrials.gov
The original PEXIVAS trial was funded by national research organizations and supported by collaborating academic institutions. The trial is registered under ClinicalTrials.gov identifier NCT00987389.
References
- Junek M, Ibrahim Q, Merkel PA, et al. Estimating 2-year risk of first relapse in ANCA-associated vasculitis: derivation of a risk-prediction model based on participants in the PEXIVAS trial. Ann Rheum Dis. 2026 Sep 22. PMID: 42772989.
- Walsh M, Merkel PA, Jayne D, et al. Plasma exchange and glucocorticoids in severe ANCA-associated vasculitis. N Engl J Med. 2020;382(7):622-631.
- Stone JH, Merkel PA, Spiera R, et al. Rituximab versus cyclophosphamide for ANCA-associated vasculitis. N Engl J Med. 2010;363(3):221-232.
- Seo P, Stone JH. The antineutrophil cytoplasmic antibody-associated vasculitides. Am J Med. 2004;117(1):39-50.
- Weidner S, Stallmach A, Mestermann S, et al. Relapse risk in ANCA-associated vasculitis treated with immunosuppressive regimens: a clinical perspective. Clin Dev Immunol. 2013;2013:1-8.