Highlight
– Approximately 30% of gynecologic cancer clinical trials fail to complete, impeding the advancement of treatments.
– Insufficient patient accrual is the predominant reason for trial non-completion.
– Intervention type, year of trial initiation, and U.S. regional differences significantly influence trial completion rates.
– Recent trials (2018-2021) show a markedly higher likelihood of non-completion, underscoring emerging challenges in clinical trial conduct.
Study Background
Gynecologic cancers, including ovarian, uterine, and cervical malignancies, represent a significant health burden globally, with substantial morbidity and mortality despite advances in treatment. Clinical trials remain the cornerstone in establishing effective therapies and improving patient outcomes. However, inefficiencies during the clinical trial lifecycle, particularly premature trial termination, undermine research progress and resource allocation. Understanding factors associated with non-completion of clinical trials in gynecologic oncology is crucial to devising strategies that enhance trial feasibility and success.
Study Design
This study retrospectively analyzed interventional clinical trials registered on ClinicalTrials.gov focusing on cervical, ovarian, and uterine cancer. Inclusion criteria mandated trials to be initiated between 2008 and 2021 with at least one trial site in the United States and clearly designated as completed or non-completed (terminated early or withdrawn). A total of 1,033 eligible trials were included. Multivariable logistic regression assessed associations between trial-level characteristics—including intervention type, year of initiation, and regional location—and the odds of trial non-completion. Reasons for premature termination were categorized to identify predominant barriers.
Key Findings
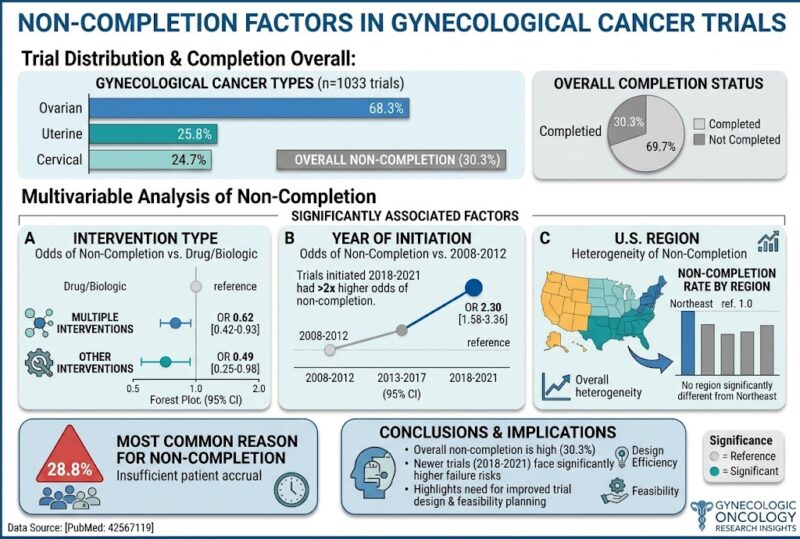
The analysis revealed that 30.3% of gynecologic cancer clinical trials did not complete. Breaking down by cancer subtype, ovarian cancer trials constituted the majority (68.3%), followed by uterine (25.8%) and cervical (24.7%) cancers. Key factors significantly associated with lower odds of non-completion included trials evaluating multiple interventions (OR 0.62, 95% CI 0.42-0.93) or other types of interventions (OR 0.49, 95% CI 0.25-0.98) compared to those focused solely on drugs or biologics.
Temporal trends showed a striking increase in non-completion risk among trials initiated in the period 2018–2021 compared with 2008–2012 (OR 2.30, 95% CI 1.58–3.36), suggesting evolving challenges in trial conduct over time. Geographical analysis indicated variability in non-completion rates across different U.S. regions, though no region showed statistically significant deviation from the reference Northeast region.
Regarding causes of premature termination, insufficient patient accrual was the most frequent reason, accounting for 28.8% of non-completed trials. Other reasons included funding issues, administrative decisions, and safety concerns.
Expert Commentary
The findings highlight the persistent challenge of patient recruitment in gynecologic oncology trials, which must be addressed to reduce waste and improve the yield of clinically actionable knowledge. The higher risk of non-completion in recent years may reflect increased trial complexity, regulatory burdens, or competing studies diluting eligible participants.
Experts emphasize the importance of rigorous feasibility assessments during the trial design phase, including realistic recruitment projections and engagement with patient advocacy groups. Incorporating adaptive trial designs and leveraging novel digital recruitment strategies may enhance enrollment efficiency. Additionally, broadening intervention types beyond drugs—such as behavioral, device-based, or combination approaches—might facilitate trial completion.
Limitations of the study include reliance on registry data which may have reporting biases and lack of granular patient demographic details that could influence accrual rates. Nonetheless, the large sample size and robust statistical methods support the validity of the conclusions. Future research should explore patient-, provider-, and institution-level factors contributing to accrual difficulties.
Conclusion
Non-completion of gynecologic cancer clinical trials remains a substantial barrier to therapeutic advancement, occurring in nearly one-third of trials. Insufficient patient accrual predominates as the critical limiting factor. Intervention type, trial initiation period, and geography also modulate completion likelihood. These insights underscore the urgent need to optimize trial design and recruitment strategies tailored to gynecologic oncology. Improved feasibility planning, including patient-centered approaches and multi-disciplinary collaboration, will be essential to elevate trial success rates and accelerate innovations in care.
Funding and ClinicalTrials.gov
No specific funding details were reported in the abstract. All analyzed trials were registered on ClinicalTrials.gov, providing a comprehensive and standardized source of trial data within the U.S.
References
Lange P, Kanal SA, Vidwans Y, Donneyong M, Meade CE, Darby JP, Sinnott JA, Felix AS. Factors associated with non-completion of gynecological cancer clinical trials. Gynecol Oncol. 2026 Aug 7;212:80-88. PMID: 42567119.
U.S. National Library of Medicine. ClinicalTrials.gov. https://clinicaltrials.gov/
Blackburn J, O’Brien J, et al. Challenges and opportunities in gynecologic cancer clinical trial enrollment: A systematic review. Gynecol Oncol Rep. 2021;36:100694.
Simon R. Clinical trial design issues in gynecologic oncology: strategies to improve trial success. Gynecol Oncol. 2019;153(2):440-445.