Highlight
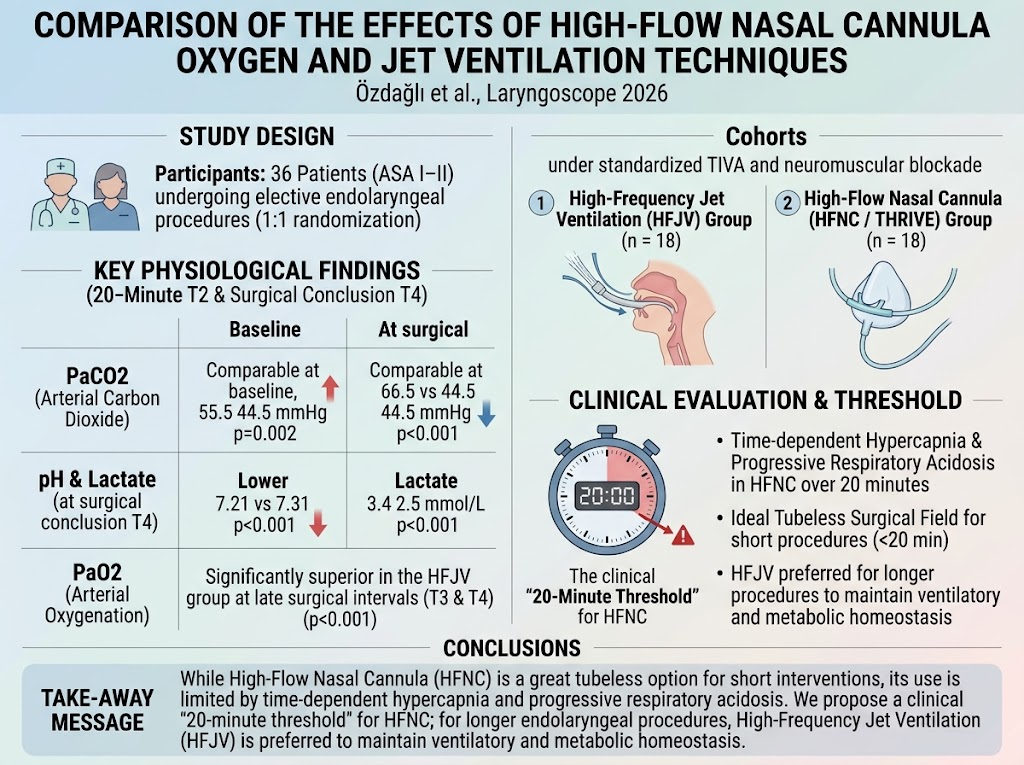
– High-Flow Nasal Cannula (HFNC) provides a tubeless surgical field but causes time-dependent hypercapnia and respiratory acidosis during endolaryngeal procedures.
– High-Frequency Jet Ventilation (HFJV) maintains better PaO2 levels and stable arterial CO2 throughout longer endolaryngeal surgeries.
– A clinical “20-minute threshold” for HFNC use is proposed to prevent metabolic derangements.
– HFJV is preferable for longer endolaryngeal surgeries to maintain ventilatory and metabolic homeostasis.
Study Background
Endolaryngeal surgery demands precise surgical access to the airway while simultaneously requiring adequate ventilation and oxygenation. Traditional ventilation methods may impede the surgeon’s visual and physical access. HFNC, through Transnasal Humidified Rapid-Insufflation Ventilatory Exchange (THRIVE), delivers high-flow humidified oxygen via nasal cannula, offering a tubeless field but its effects on ventilation, especially CO2 clearance during longer procedures, remain under scrutiny. Alternatively, High-Frequency Jet Ventilation employs rapid pulses of gas through a small catheter, potentially maintaining better gas exchange without compromising surgical access. Understanding the comparative effects of these ventilation strategies on perioperative oxygenation, carbon dioxide kinetics, and metabolic stability is vital to optimizing anesthesia during endolaryngeal surgery.
Study Design
This prospective randomized controlled trial enrolled 36 patients classified as ASA physical status I or II undergoing elective endolaryngeal procedures. Patients were randomly assigned to two groups: HFJV (n=18) and HFNC (n=18). Both groups received a standardized total intravenous anesthesia (TIVA) regimen with neuromuscular blockade to ensure uniformity in anesthetic depth and muscle relaxation. Primary endpoints involved arterial partial pressure of carbon dioxide (PaCO2) measured longitudinally at baseline (T0), 10 minutes (T1), 20 minutes (T2), 30 minutes (T3) post-induction, and at surgery completion (T4). Secondary outcomes included arterial oxygen partial pressure (PaO2), blood pH, and serum lactate levels to assess metabolic response and oxygenation during ventilation.
Key Findings
At baseline (T0) and 10 minutes post-induction (T1), both groups displayed comparable PaCO2, indicating similar initial respiratory status. From 20 minutes (T2) onward, HFNC patients exhibited significant worsening of hypercapnia, with median PaCO2 rising to 55.5 mmHg, compared to 44.5 mmHg in the HFJV group (p=0.002). At surgery end (T4), the disparity was profound, with median PaCO2 at 66.5 mmHg in the HFNC group versus 44.5 mmHg for HFJV (p<0.001). Correspondingly, the HFNC cohort showed a significant drop in arterial pH (7.21) compared to HFJV (7.31; p<0.001), indicating respiratory acidosis, alongside elevated serum lactate (3.4 vs. 2.5 mmol/L; p<0.001), which suggests metabolic stress. PaO2 measurements at the 30-minute (T3) and conclusion (T4) timepoints significantly favored HFJV (p<0.001), demonstrating superior oxygenation with jet ventilation. No significant complications or adverse events were reported in either group within the perioperative period.
Expert Commentary
This rigorous randomized trial provides valuable clinical insight into airway management strategies balancing surgical access and patient ventilation during endolaryngeal procedures. The documented progressive hypercapnia and acidosis under HFNC are physiologically plausible due to insufficient CO2 clearance despite high oxygen flows, consistent with previous observational reports. The demonstrated threshold of approximately 20 minutes for safe HFNC application is a practical clinical guideline that could reduce intraoperative metabolic derangements and potential complications associated with hypercapnia. HFJV’s enhanced gas exchange likely results from its active ventilatory mechanism producing effective CO2 elimination, making it a logical choice for longer surgeries. However, HFJV may require specialized equipment and expertise, potentially limiting its availability in some centers. Future studies could investigate combined or sequential use of these modalities or alternate techniques to optimize both surgical exposure and respiratory homeostasis.
Conclusion
This study conclusively shows that while HFNC provides an optimal tubeless surgical field for short endolaryngeal procedures, its utilization beyond approximately 20 minutes is limited by a significant rise in PaCO2 and ensuing respiratory acidosis with metabolic compromise. Conversely, HFJV effectively maintains normocapnia, adequate oxygenation, and pH balance throughout longer interventions. Clinicians should consider these physiological effects when selecting airway management modalities for endolaryngeal surgery, tailoring ventilation strategy to the anticipated procedure duration to optimize patient safety and surgical conditions.
Funding and ClinicalTrials.gov
This clinical trial was registered at ClinicalTrials.gov under registration number NCT05746949. No specific funding sources were disclosed.
References
1. Özdağlı S, Canbaz M, Çamcı E, Kırşan N, Akdoğan B, Altun D, Çelik M, Altun D. Comparison of the Effects of High-Flow Nasal Cannula Oxygen and Jet Ventilation Techniques. The Laryngoscope. 2026 Oct 6. PMID: 42838698.
2. Patel A, Nouraei SA. Transnasal Humidified Rapid-Insufflation Ventilatory Exchange (THRIVE): A Physiological Method of Increasing Apnoea Time in Patients with Difficult Airways. Anaesthesia. 2015;70(3):323-329.
3. Belafia F, Massard G, Bessede D et al. High-Frequency Jet Ventilation in Microlaryngeal Surgery: Physiological Insights and Clinical Outcomes. Eur J Anaesthesiol. 2018;35(10):786-792.