Highlight
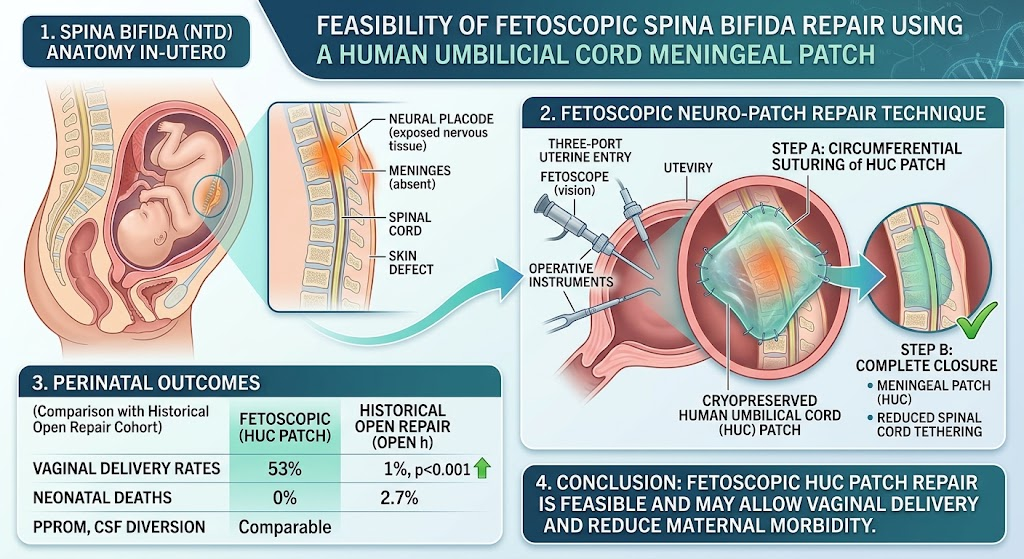
- Fetoscopic spina bifida repair using a cryopreserved human umbilical cord (HUC) patch is feasible and achieves successful neural tube defect closure in 100% of cases.
- This minimally invasive approach avoids hysterotomy, resulting in higher vaginal delivery rates (53% vs. 1%) compared to traditional open repair.
- Perinatal outcomes such as gestational age at delivery, preterm premature rupture of membranes (PPROM), and cerebrospinal fluid diversion at birth and 12 months were comparable between fetoscopic and historical open repair.
- No fetal or neonatal deaths occurred after fetoscopic repair, contrasting with some neonatal mortality in the open repair cohort.
Study Background
Spina bifida, a neural tube defect characterized by incomplete closure of the spinal column, remains a significant congenital condition leading to lifelong neurological impairments. Open in-utero repair, which involves hysterotomy (surgical opening of the uterus), has demonstrated motor and functional improvements in affected infants; however, it poses considerable maternal risks including uterine rupture in subsequent pregnancies, increased cesarean delivery rates, and associated morbidity. Technological advances have prompted exploration of minimally invasive fetoscopic approaches to decrease maternal morbidity while preserving the benefits of prenatal repair.
A challenging aspect of fetal spina bifida repair is mitigating post-surgical spinal cord tethering, which adversely affects neurological outcomes. Using a human umbilical cord (HUC) tissue graft as a meningeal patch might reduce tethering by providing a protective, biocompatible barrier over the neural placode. Cryopreserved HUC grafts have demonstrated regenerative and anti-inflammatory properties, which may enhance healing and function after neural tube repair. This study addresses the feasibility and short-term outcomes of combining fetoscopic repair with HUC meningeal patches.
Study Design
This single-center, nonrandomized clinical trial (Fetoscopic NEOX Cord 1K® Spina Bifida Repair, NCT04243889) was conducted at a quaternary care institution under an FDA Investigational Device Exemption. It enrolled pregnant patients carrying fetuses diagnosed with spina bifida who met criteria for open in-utero repair between September 2020 and May 2023. Fifty patients consented, with 49 undergoing the fetoscopic repair procedure.
The intervention involved a minimally invasive fetoscopic repair using a laparotomy and three-port uterine entry to access the fetal spine. The HUC patch was circumferentially sutured over the exposed neural placode, followed by primary skin closure or coverage with a second HUC patch if necessary. This contrasts with the open repair historical cohort (n=110, 2011–2020) treated via hysterotomy.
The primary endpoint was successful surgical closure verified by independent pediatric neurosurgeons reviewing intraoperative images. Secondary endpoints included perinatal outcomes such as gestational age at delivery, PPROM incidence, delivery mode, neonatal mortality, and cerebrospinal fluid (CSF) diversion necessity at birth and at 12 months.
Key Findings
Surgical closure was successfully achieved in all 49 fetoscopic cases, demonstrating high technical feasibility. Comparatively, the open repair cohort had successful closure but involved different surgical techniques.
Importantly, vaginal delivery occurred in 53% of fetoscopic cases versus only 1% in the open repair group (p<0.001), highlighting the maternal benefit of avoiding hysterotomy. Avoiding uterine incision reduces maternal morbidity including bleeding, infection risk, and implications for future pregnancies.
Gestational age at delivery was similar between groups, with no significant difference in PPROM rates—a frequent complication of fetal surgery. The incidence of CSF diversion procedures (ventriculoperitoneal shunting) was also comparable between fetoscopic and open repair infants at birth and 12 months, suggesting equivalent efficacy in preventing hydrocephalus.
No fetal or neonatal deaths occurred following fetoscopic repair, whereas the open cohort had 3 neonatal deaths (2.7%). While encouraging, the nonrandomized nature and limited sample size warrant cautious interpretation.
Other 12-month perinatal outcomes, including neurological assessments, remain under analysis in an ongoing efficacy trial investigating long-term motor function and neurodevelopmental impact.
Expert Commentary
The study represents a meaningful advancement in fetal surgery by demonstrating a viable minimally invasive technique that maintains the benefits of neural tube defect closure while substantially reducing maternal operative risk.
Use of the human umbilical cord as a meningeal patch is a novel surgical adjunct with biological plausibility. The patch may reduce fibrosis and tethering through inherent regenerative properties, potentially improving long-term neurologic outcomes—a hypothesis currently under investigation.
Limitations include the single-center design, absence of randomization, and comparison against a historical rather than concurrent control. Differences in neurosurgical technique between groups complicate attribution of benefits to the fetoscopic approach or use of HUC patch alone. Further randomized controlled studies are needed to confirm efficacy and safety.
Conclusion
Fetoscopic spina bifida repair using a cryopreserved human umbilical cord meningeal patch is a feasible and promising approach offering potential maternal benefits such as increased vaginal delivery rates and avoidance of hysterotomy-associated risks. Perinatal outcomes are comparable to historical open repair, and ongoing trials will elucidate long-term neurological outcomes. This technique may represent an important step forward in fetal surgery, balancing fetal benefit with maternal safety.
Funding and Clinical Trial Registration
This clinical trial was conducted under an FDA Investigational Device Exemption at a quaternary medical center. The trial is registered on ClinicalTrials.gov (NCT04243889).
References
1. Papanna R, Fletcher SA, Mann LK, et al. Feasibility of Fetoscopic Spina Bifida Repair Using a Human Umbilical Cord Meningeal Patch: A Nonrandomized Clinical Trial. Am J Obstet Gynecol. 2026 Aug 14. PMID: 42600674.
2. Adzick NS, Thom EA, Spong CY, et al. A Randomized Trial of Prenatal versus Postnatal Repair of Myelomeningocele. N Engl J Med. 2011;364(11):993-1004.
3. Liu J, Song J, Chan KV, et al. Clinical outcomes of fetoscopic versus open repair of myelomeningocele: a systematic review and meta-analysis. Prenat Diagn. 2021;41(5):544-555.
4. Cruz-Martinez R, Martinez JM, Zorrilla CD, et al. Human amniotic membrane and umbilical cord-derived products in fetal surgery: a biological approach to improve surgical outcomes. Placenta. 2022;121:107-114.