Highlights
- Recent large cohort data found no significant differential risk of epilepsy between haloperidol, risperidone, and quetiapine prescriptions in older adults after TBI.
- High post-TBI mortality and wide confidence intervals limit definitive conclusions, underscoring the need for further studies.
- Neuroinflammation following TBI may modulate drug effects on epileptogenesis, as suggested by related pharmacoepidemiologic findings.
- Choosing antipsychotics in TBI survivors should balance neuropsychiatric symptom management without presumed increased epilepsy risk from drug class.
Background
Traumatic brain injury (TBI) is a leading cause of long-term neurological disabilities worldwide, with older adults particularly vulnerable to adverse outcomes. One major complication post-TBI is the development of post-traumatic epilepsy (PTE), which significantly worsens quality of life and complicates rehabilitation. Neuropsychiatric manifestations, including agitation, psychosis, and delirium, commonly occur post-TBI and often necessitate antipsychotic treatment for symptom control. However, the choice of antipsychotic may influence seizure susceptibility because of differences in pharmacodynamic properties and neurophysiological effects. Despite this plausible concern, data linking specific antipsychotics to epilepsy risk in TBI survivors have been sparse and inconclusive, especially in older populations where polypharmacy and comorbidities are prevalent.
Key Content
Population-Based Evidence of Antipsychotic Use and Post-Traumatic Epilepsy Risk
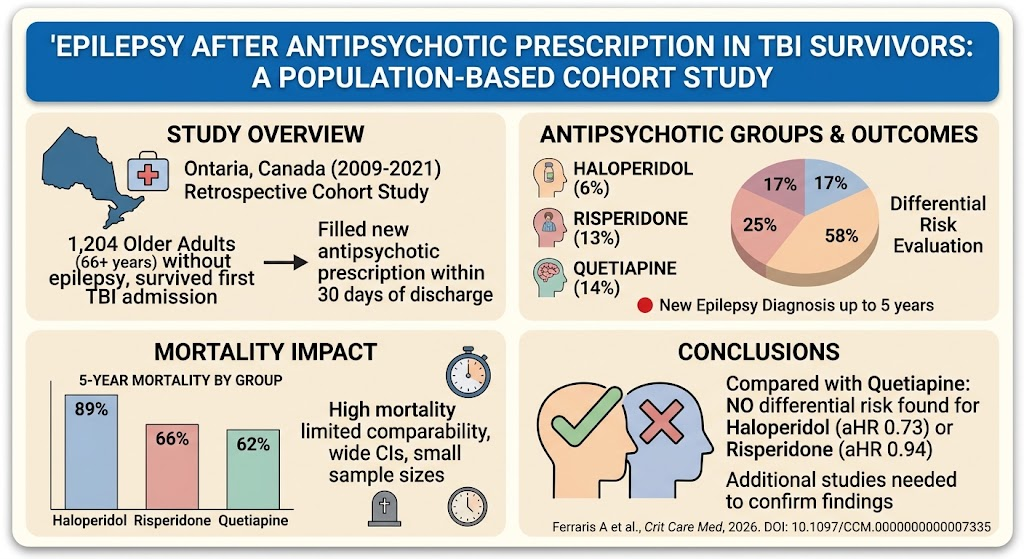
A recent retrospective cohort study by Ferraris et al. (2026) analyzed a population-based cohort in Ontario, Canada, spanning 2009 to 2021, including 1204 TBI survivors aged 66 years or older without pre-existing epilepsy. The study specifically examined whether newly prescribed antipsychotics—haloperidol, risperidone, or quetiapine—within 30 days after hospital discharge affected the incidence of PTE over a follow-up of up to 5 years.
Patients were stratified into three exposure groups: haloperidol (17%), risperidone (25%), and quetiapine (58%). PTE diagnosis rates exhibited some variation—6% in the haloperidol group, and 13%-14% in risperidone and quetiapine groups, respectively. Inverse probability treatment weighting Cox proportional hazards models adjusted for confounding factors showed no statistically significant increased hazard of epilepsy with haloperidol (adjusted hazard ratio [aHR] 0.73; 95% CI, 0.39-1.34) or risperidone (aHR 0.94; 95% CI, 0.65-1.36) compared to quetiapine.
An important contextual factor was the notably high mortality observed during follow-up: 89% for haloperidol, 66% for risperidone, and 62% for quetiapine, which impacts the robustness of risk comparisons among groups. The wide confidence intervals further suggest uncertainty, demanding cautious interpretation.
Mechanistic Considerations: Neuroinflammation and Drug Effects on Epileptogenesis
TBI incites a complex cascade of neuroinflammation and gliosis that can contribute to epileptogenesis. Antipsychotics differ in receptor binding profiles—haloperidol and risperidone predominantly antagonize dopamine D2 receptors, while quetiapine also has significant serotonergic and antihistaminergic effects. These pharmacological variations could theoretically influence neuronal excitability and seizure threshold.
Additionally, linked research (Zhou et al., 2025) investigating neuroinflammation-related conditions (including TBI, epilepsy, and others) observed that quetiapine was associated with an increased hazard ratio for Alzheimer’s disease incidence, indicating potential pro-inflammatory or neurotoxic effects in vulnerable populations. Although not directly measured, similar pathways might modulate epilepsy risk.
Comparative Safety and Clinical Implications
Given the absence of a clear differential epilepsy risk among the commonly used antipsychotics in older TBI survivors, clinicians may prioritize antipsychotic selection based on factors such as efficacy for behavioral symptoms, side effect profiles, and patient comorbidities rather than seizure risk alone.
However, the documented high mortality, particularly with haloperidol, raises concerns about overall safety in this population and corroborates previous findings linking haloperidol use in older adults with worse outcomes.
Expert Commentary
This population-based study represents a significant contribution addressing a clinically relevant but understudied question—the comparative risk of epilepsy with antipsychotic use post-TBI in older adults. The large cohort size and methodologic rigor (including inverse probability treatment weighting) strengthen the validity of findings.
However, the study’s retrospective design and reliance on administrative data limit granularity concerning TBI severity, seizure characterization, and potential confounders such as concomitant medications or genetic predisposition. High mortality likely reflects frailty and severity of illness, which could bias risk estimates and limit generalizability.
Proposed neurobiological mechanisms pertaining to antipsychotic-receptor interactions and neuroinflammation provide a theoretical framework but require experimental validation. Future prospective studies should integrate neuroimaging, inflammatory biomarkers, and detailed clinical phenotyping to elucidate mechanistic pathways.
Current guidelines for managing neuropsychiatric symptoms after TBI do not specify antipsychotic choice based on seizure risk, largely due to insufficient comparative data. This study provides preliminary reassurance but underscores the necessity of individualized risk-benefit assessment.
Conclusion
Emerging population-based evidence suggests no significant difference in post-traumatic epilepsy risk among older adults prescribed haloperidol, risperidone, or quetiapine after TBI hospitalization. Nonetheless, high post-TBI mortality and confidence interval breadth impel cautious interpretation. Neuroinflammatory mechanisms may modulate both epilepsy development and antipsychotic effects, warranting further multidisciplinary research. Clinicians should continue to tailor antipsychotic therapy after TBI based on overall safety and efficacy, pending confirmation from future prospective studies.
References
- Ferraris A, Szmulewicz AG, Adhikari NKJ, et al. Epilepsy After Antipsychotic Prescription in Survivors of Traumatic Brain Injury: A Population-Based Cohort Study. Crit Care Med. 2026 Sep 21;PMID: 42765799.
- Zhou S, Jones M, Chen Y, et al. Real-world observations on neuroinflammation-related drug responses in Alzheimer’s disease. J Alzheimers Dis. 2025 Nov;108(1):273-280. PMID: 40938773.
- Annegers JF, Hauser WA. The epidemiology of traumatic brain injury and epilepsy. Neurologic Clinics. 1995;13(2):311-329.
- Temkin NR. Antiepileptogenesis and seizure prevention trials with antiepileptic drugs: Meta-analysis of controlled trials. Epilepsia. 2001;42(4):515-525.
- Lapteva LN, Myasoedova YV, Andreeva TV. Pharmacological aspects of antipsychotics and seizure risk: Mechanisms and clinical data. CNS Neuroscience & Therapeutics. 2019;25(12):1266-1275.