Highlight
- Patients with Cushing’s syndrome exhibit unfavorable lipid profiles during active disease.
- Early postoperative remission after curative surgery is marked by paradoxical worsening of lipid parameters including decreases in HDL and ApoA1 and increases in triglycerides.
- These lipid alterations persist up to 6 months post-surgery and associate with increased inflammation, suggesting heightened cardiovascular risk in early remission.
- Distinct postoperative trajectories of non-esterified fatty acids correlate with baseline BMI, indicating metabolic heterogeneity.
Study Background
Cushing’s syndrome (CS) is characterized by chronic endogenous hypercortisolism which profoundly disrupts metabolic homeostasis, notably lipid metabolism. Individuals with active CS commonly exhibit dyslipidemia, including elevated triglycerides and low high-density lipoprotein (HDL), contributing to increased cardiovascular morbidity and mortality. While curative surgery often restores hormonal balance, the early postoperative period represents a vulnerable phase wherein physiological adjustments may paradoxically exacerbate cardiovascular risk factors. Data specifically examining lipid profile dynamics during this early remission are limited, presenting a gap in understanding and clinical management.
Study Design
This single-center longitudinal cohort study was conducted at the Ludwig Maximilian University (LMU) Hospital, Munich. Twenty-six patients with confirmed endogenous CS undergoing curative surgery were prospectively enrolled. Comprehensive lipid profiling—total cholesterol, LDL, HDL, apolipoproteins A1 and B, lipoprotein(a), triglycerides, and non-esterified fatty acids—along with metabolic markers were measured preoperatively and at 1, 3, 6, 12, and 24 months postoperatively (23 patients completed the 24-month follow-up). A control group of 26 age-, BMI-, and sex-matched individuals without hypercortisolism served for baseline comparisons. The primary objective was to define the trajectory of lipid alterations through the active CS phase and into early remission after surgery.
Key Findings
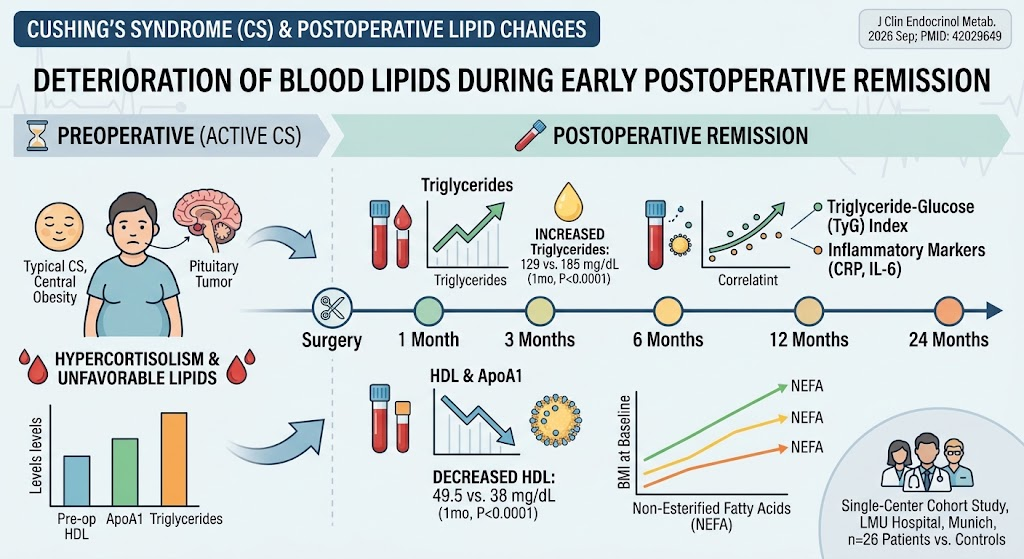
Contrary to expectations, lipid profiles worsened transiently in the early postoperative remission phase rather than improving immediately after cortisol normalization. Specifically, HDL cholesterol significantly decreased from a median of 49.5 mg/dL during active disease to 38 mg/dL at 1 month post-surgery (P < .0001). ApoA1 levels followed a similar trajectory, dropping from 193 mg/dL to 160 mg/dL (P < .0001). Concurrently, triglycerides rose markedly from 129 mg/dL preoperatively to 185 mg/dL one month after surgery (P < .0001). These dyslipidemic changes persisted up to 6 months postoperatively before gradual normalization.
Additionally, the triglyceride-glucose index, a surrogate marker for insulin resistance and cardiovascular risk, increased significantly during early remission. This index showed positive correlations with systemic inflammatory markers C-reactive protein (CRP) and interleukin-6 (IL-6), suggesting inflammation as a potential mediator of lipid worsening.
Analysis of non-esterified fatty acids revealed three unique postoperative patterns stratified by baseline body mass index (BMI), reflecting metabolic heterogeneity in recovery trajectories. Obese individuals exhibited different lipid mobilization or clearance compared to leaner counterparts, which could influence cardiovascular risk profiles.
Expert Commentary
The study presents compelling evidence that the immediate postoperative period after curative CS surgery is paradoxically characterized by a deterioration rather than improvement of lipid metabolism. This may reflect transient hypothalamic-pituitary-adrenal (HPA) axis suppression, altered adipose tissue function, and heightened inflammatory responses that often accompany abrupt cortisol withdrawal. It underscores the complexity of metabolic recovery following hypercortisolism and highlights a critical time window for intensified cardiovascular risk monitoring.
Importantly, these findings suggest that clinicians should not assume lipid normalization upon cortisol control and instead maintain vigilance for worsening dyslipidemia, which may necessitate early initiation or adjustment of lipid-lowering therapies. Future guidelines may benefit from incorporating postoperative lipid assessment protocols and personalized therapies based on metabolic phenotyping, including BMI stratification.
Limitations include a modest sample size and single-center design, which might limit broader applicability. However, the comprehensive longitudinal follow-up and matched control comparisons strengthen the internal validity.
Conclusion
This longitudinal cohort study reveals that the early postoperative remission phase of Cushing’s syndrome is paradoxically associated with further deterioration in lipid profiles, sustained inflammation, and variable metabolic recovery trajectories. These findings illuminate an underrecognized period of increased cardiovascular vulnerability warranting proactive monitoring and possibly tailored therapeutic interventions. Further research should explore mechanistic underpinnings and optimal management strategies to mitigate cardiovascular risk in CS patients transitioning to remission.
Funding and ClinicalTrials.gov
The study was conducted at LMU Hospital, Munich. No specific funding or clinical trial registration was reported in the source publication.
References
- Schrenk M, Haenelt M, Oettle M, et al. Deterioration of blood lipids during early postoperative remission of Cushing’s syndrome: a longitudinal cohort study. J Clin Endocrinol Metab. 2026;111(10):2816–2826. PMID: 42029649.
- Newell-Price J, Nieman LK, Reincke M, et al. Cushing’s syndrome. Lancet. 2006;367(9522):1605-1617.
- Nieman LK. Cushing’s syndrome: update in diagnosis and biochemical evaluation. Endocrinol Metab Clin North Am. 2018;47(2):259–273.
- Funder JW, Carey RM, Mantero F, et al. The Management of Primary Aldosteronism: Case Detection, Diagnosis, and Treatment. Hypertension. 2016;68(1):e7–e44.
- Colao A, Pivonello R, Auriemma RS, et al. The burden of comorbidities in Cushing’s disease: Clinical and health-related quality of life aspects. Endocrinol Metab Clin North Am. 2018;47(2):303–326.