Early Escalation of Acute Treatment Reduces Relapse Risk in Pediatric MOG Antibody-Associated Disease
Highlight
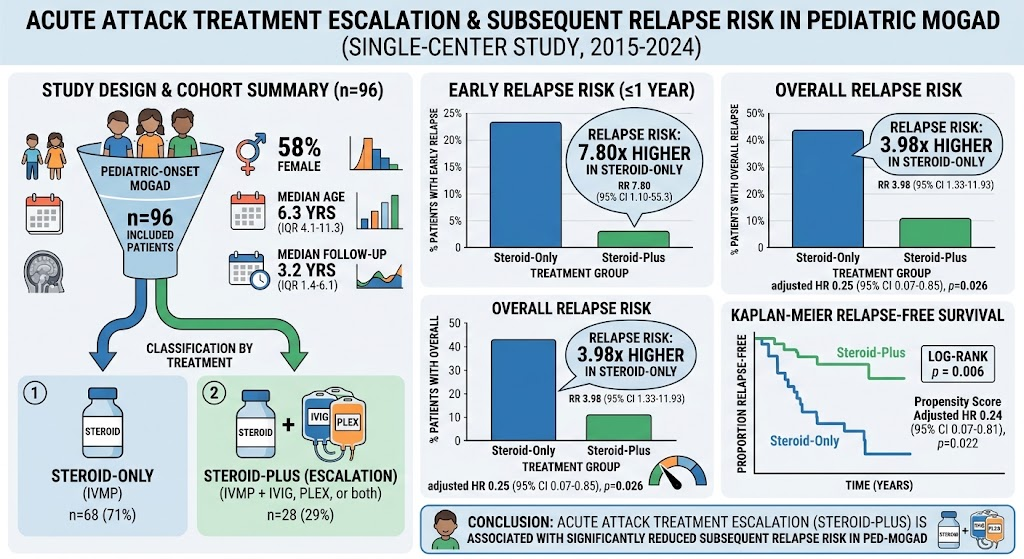
This study demonstrates that in pediatric myelin oligodendrocyte glycoprotein antibody-associated disease (MOGAD), escalation of acute immunotherapy from steroids alone to include intravenous immunoglobulin and/or plasma exchange during the first attack is associated with a substantial reduction in early and overall relapse risk. Key findings include a 7.8-fold increased risk of relapse at 1 year with steroid-only treatment versus escalation therapy and sustained relapse risk reduction over a median follow-up exceeding 3 years. These results suggest that aggressive immunotherapy at initial presentation may beneficially modify long-term disease course.
Study Background
MOG antibody-associated disease (MOGAD) is an autoantibody-mediated central nervous system demyelinating condition increasingly recognized in pediatric neurology. It manifests with diverse phenotypes such as optic neuritis, transverse myelitis, and acute disseminated encephalomyelitis. Although often monophasic, a significant subset of patients experiences relapsing disease, leading to cumulative neurological disability. Treatment paradigms focus on acute immunotherapy to reduce inflammation during relapses and maintenance therapy to prevent recurrence. However, the optimal acute treatment strategy remains uncertain, particularly regarding escalation beyond high-dose intravenous methylprednisolone (IVMP) to adjunct therapies like intravenous immunoglobulin (IVIG) and plasma exchange (PLEX). Identifying whether early treatment intensification after the first attack influences relapse risk is crucial to improve pediatric patient outcomes and guide clinical decision-making.
Study Design
This retrospective single-center cohort study evaluated 96 pediatric patients diagnosed with MOGAD between 2015 and 2024. Eligibility criteria included documented MOG antibody positivity and pediatric-onset demyelinating events. Patients were categorized into two groups based on acute attack treatment received: the steroid-only group (high-dose IVMP alone) and the steroid-plus group (IVMP followed by escalation to IVIG, PLEX, or both). The median age at onset was 6.3 years with a female predominance (58%). Median clinical follow-up was 3.2 years, allowing assessment of both early (within 1 year) and overall relapse occurrences. Primary outcome measures were relapse rates and time to relapse analyzed using Kaplan-Meier survival curves and adjusted Cox proportional hazards models controlling for potential confounders, supplemented by propensity score adjustment to minimize treatment selection bias.
Key Findings
The analysis revealed that 71% of patients received only steroid treatment, while 29% received escalation immunotherapy. At one year post-initial attack, relapse occurred in 28% of the steroid-only cohort compared with just 4% in the escalation group, yielding a relative risk (RR) of 7.80 (95% confidence interval [CI], 1.10–55.3). Over the entire follow-up period, relapses were recorded in 43% of the steroid-only versus 11% of the escalation patients (RR 3.98; 95% CI 1.33–11.93). Time-to-event analyses indicated that escalation therapy reduced relapse hazard by approximately 75% (adjusted hazard ratio [HR] 0.25; 95% CI 0.07–0.85; p = 0.026), consistent across propensity score-adjusted models (HR 0.24; 95% CI 0.07–0.81; p = 0.022), indicating robustness of the finding despite potential confounders. The log-rank test confirmed significant differences in relapse-free survival between groups (p = 0.006).
No specific safety data were detailed in this report, but escalation treatments such as IVIG and PLEX are established as generally safe in pediatric neuroimmunology with manageable adverse effect profiles. The study contributes important evidence suggesting that intensifying acute immunotherapy during the first attack is associated with favorable disease control in pediatric MOGAD.
Expert Commentary
The findings align with the evolving understanding of MOGAD as a disorder where early and aggressive immunomodulation may prevent pathogenic immune processes from establishing a chronic relapse-prone state. The first demyelinating event may represent a critical window wherein immune-mediated injury and autoimmune memory can be disrupted with intensive therapy. This study fills a gap in pediatric neuroimmunology by quantifying the benefits of acute treatment escalation, supporting clinical strategies that go beyond steroids alone in severe or incomplete-response cases.
However, retrospective design, single-center setting, and potential selection bias must be considered. Patients receiving escalation were likely those with more severe initial presentations or suboptimal steroid responses, possibly confounding results despite statistical adjustments. Prospective randomized trials are needed to definitively establish causality and guide standardized treatment algorithms. Additionally, long-term safety and cost-benefit analyses of escalation therapies require further exploration.
Guidance from recent consensus recommendations acknowledges the role of PLEX and IVIG in steroid-refractory MOGAD attacks but lacks precise protocols on timing or patient selection, signaling an area for future research integration.
Conclusion
This robust retrospective cohort study demonstrates that escalation of acute immunotherapy to include IVIG and/or plasma exchange at the first attack in pediatric MOGAD significantly decreases early and mid-term relapse risk compared with steroids alone. These data support the concept that early therapeutic intensification can alter disease trajectory, highlighting the first attack as a vital therapeutic opportunity. Incorporating escalation treatment into early clinical management may improve long-term neurological outcomes and reduce cumulative disease burden. Ongoing research should aim to standardize treatment thresholds and confirm findings in prospective controlled settings.
Funding and ClinicalTrials.gov
The report does not specify funding sources or clinical trial registration. Future studies should emphasize transparency of funding and trial registration to enhance evidence reliability.
References
1. Bartolomeo S, Nistri R, Kim NN, et al. Acute Attack Treatment Escalation and Subsequent Relapse Risk in Pediatric Myelin Oligodendrocyte Glycoprotein Antibody-Associated Disease. Neurology. 2026;107(5):e218405. doi:10.1212/WNL.0000000000002184
2. Baumann M, Hennes EM, Schanda K, et al. Clinical and neuroradiological differences of pediatric monophasic and relapsing MOG-IgG-associated demyelination. Neurology. 2016;87(12):1382-1391.
3. Wong Y, Wong K, Alsaadon M, et al. Clinical features and outcomes of MOG antibody disease in children. Dev Med Child Neurol. 2022;64(2):170-177.
4. Hacohen Y, Whittam D, Woodhall M, et al. MOG antibody-associated disease: characterizing clinical disease. Semin Neurol. 2020;40(4):493-504.
5. Burgoon JM, Pittock SJ, Messina SA, et al. Diagnostic criteria and treatment strategies for relapsing MOG-IgG antibody-associated disease. Neurol Neuroimmunol Neuroinflamm. 2021;8(5):e1043.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.