Highlight
Derazantinib, a selective FGFR1-3 kinase inhibitor, showed clinically meaningful efficacy in previously treated intrahepatic cholangiocarcinoma (iCCA) patients harboring FGFR2 fusions, mutations, or amplifications.
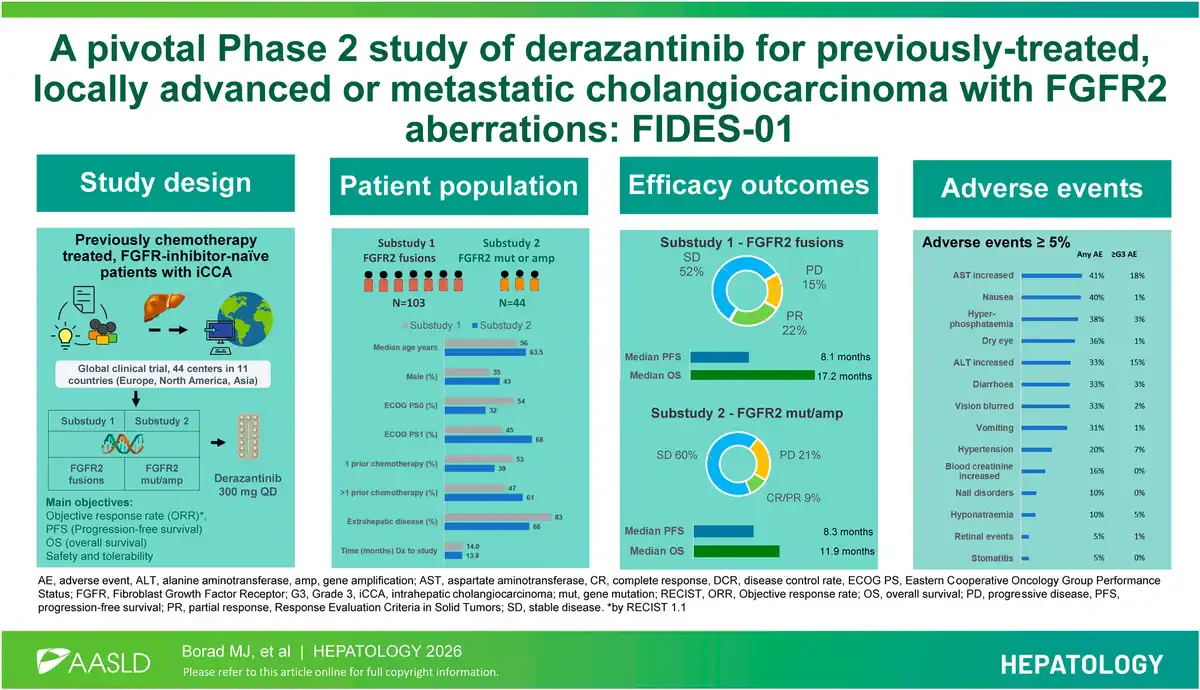
The Phase 2 FIDES-01 trial demonstrated an objective response rate (ORR) of 22.3% in patients with FGFR2 fusions, median progression-free survival (PFS) of 8.1 months, and overall survival (OS) exceeding 17 months in this subgroup.
Patients with FGFR2 mutations or amplifications also displayed disease control with a 3-month progression-free survival rate of 63% and manageable safety profile.
Common FGFR inhibitor class-related adverse events included hyperphosphataemia and dry eye, mostly low grade, with no grade 4 or 5 drug-related toxicities reported.
Study Background
Intrahepatic cholangiocarcinoma (iCCA) is an aggressive biliary tract malignancy with limited treatment options in advanced stages, particularly after progression on chemotherapy. Recent molecular characterization has identified fibroblast growth factor receptor 2 (FGFR2) alterations—including fusions, mutations, and amplifications—in a subset of iCCA patients, representing actionable targets for FGFR inhibitors.
Existing FGFR inhibitors have shown variable efficacy and safety profiles, necessitating further development of effective targeted therapies that can improve clinical outcomes with tolerable adverse events.
Study Design
FIDES-01 was an open-label, single-arm, Phase 2 trial assessing the safety and efficacy of derazantinib in patients with advanced, locally advanced or metastatic iCCA harboring FGFR2 aberrations, who had received at least one prior chemotherapy regimen. The trial was divided into two substudies based on FGFR2 alteration type:
Substudy 1: Patients with FGFR2 fusions or rearrangements (FGFR2F).
Substudy 2: Patients with FGFR2 mutations (FGFR2M) or amplifications (FGFR2A).
Patients received derazantinib 300 mg orally once daily until disease progression, unacceptable toxicity, withdrawal of consent, or investigator decision. Efficacy was centrally assessed via imaging using RECIST v1.1 criteria.
Primary endpoints were:
Substudy 1: Objective response rate (ORR).
Substudy 2: 3-month progression-free survival rate (PFS3).
Secondary endpoints included disease control rate (DCR), duration of response (DOR), progression-free survival (PFS), overall survival (OS), and safety.
Key Findings
Substudy 1 (FGFR2 Fusions):
Among 103 evaluable patients, a partial response was observed in 23 cases, yielding an ORR of 22.3% (95% CI not provided).
The disease control rate, encompassing stable disease plus responses, was 75.7%.
Median PFS was 8.1 months (95% CI, 5.5 to 8.3 months).
Duration of response median was 6.5 months (95% CI, 4.6 to 9.2 months).
Median overall survival reached 17.2 months (95% CI, 12.5 to 22.4 months), suggesting prolonged clinical benefit.
Substudy 2 (FGFR2 Mutations/Amplifications):
The 3-month progression-free survival rate was 63% (27/43 patients), indicating disease stabilization in a majority of patients.
ORR was modest at 9.3%, with one complete and three partial responses.
Disease control rate was 69.8%, comparable to Substudy 1.
Median OS was 11.9 months (95% CI, 8.4 to 15.9 months), showing some efficacy though less pronounced than in FGFR2 fusion cases.
Safety Profile:
No grade 4 or 5 drug-related adverse events were reported, underscoring a favorable safety profile.
The most common adverse events were drug-related hyperphosphataemia (38%, grade 3 in 3% of patients), a class effect of FGFR inhibition, and dry eye (36%).
Less common toxicities included nail disorders (10%), stomatitis (5%), retinal events (5%), and palmar-plantar erythrodysesthesia (1%), which were mostly low grade and manageable.
Expert Commentary
This study contributes valuable data on derazantinib as a treatment option in FGFR2-altered iCCA, expanding the therapeutic landscape for a patient population with historically poor prognosis after chemotherapy failure.
The efficacy outcomes, particularly in FGFR2 fusion-positive tumors, align with the known oncogenic role of FGFR2 rearrangements in iCCA pathogenesis and the rationale for targeted kinase inhibition.
While the response rate in patients with FGFR2 mutations or amplifications was lower, the high disease control rate suggests derazantinib may delay progression in this subgroup, warranting further exploration.
Compared with other FGFR inhibitors, derazantinib’s manageable safety profile and demonstrated durable clinical benefit position it as an important agent for FGFR2-driven cholangiocarcinoma.
Limitations include the non-randomized, open-label design without a comparator arm, which may impact the strength of efficacy conclusions. Long-term follow-up and real-world studies will be valuable to confirm durability and tolerability.
Conclusion
In patients with advanced iCCA harboring FGFR2 fusions, mutations, or amplifications who have previously received chemotherapy, derazantinib offers clinically meaningful efficacy and durable disease control with acceptable toxicity.
These data support derazantinib as a targeted therapy option in FGFR inhibitor-naïve iCCA patients, highlighting the importance of molecular stratification and personalized treatment strategies in biliary tract cancers.
Further investigation in larger randomized trials and comparative studies will clarify its definitive clinical role and optimal patient selection criteria.
Funding and Clinical Trials Registration
The trial was supported by industry and/or academic sponsors, as referenced in the original publication. Clinical trial details and registration information are retrievable via the cited PubMed ID.
References
1. Borad MJ, Droz Dit Busset M, Javle MM, et al. A pivotal Phase 2 study of derazantinib for previously-treated, locally advanced or metastatic cholangiocarcinoma with FGFR2 aberrations: FIDES-01. Hepatology (Baltimore, Md.). 2026 Oct 27. PMID: 42937546.
2. Abou-Alfa GK, et al. Pemigatinib for previously treated, locally advanced or metastatic cholangiocarcinoma: the FIGHT-202 study. J Clin Oncol. 2020; 38(8): 2963-2972.
3. Arai Y, Totoki Y, Hosoda F, et al. Fibroblast growth factor receptor 2 tyrosine kinase fusions define a unique molecular subtype of cholangiocarcinoma. Hepatology. 2014;59(4):1427-1434.