Coordinated Precision Care for Rare Genetic Obesity: European Expert Consensus on Centers of Expertise and Structured Monitoring
Introduction and Context
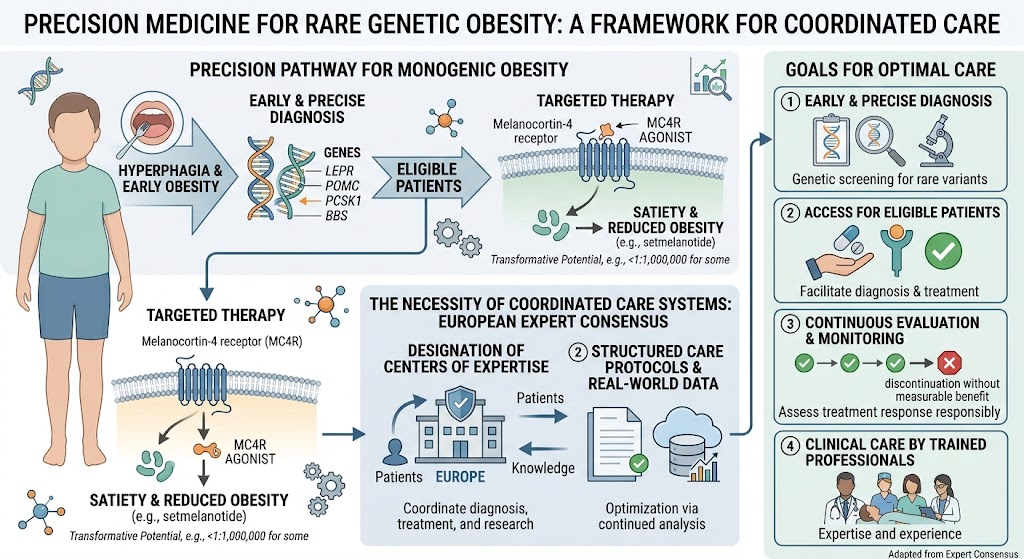
Rare, monogenic forms of obesity—caused by single-gene defects disrupting appetite regulation—have moved from biological curiosity to a treatable clinical entity. Over the past decade, foundational discoveries about hypothalamic leptin–melanocortin circuitry and targeted drug development culminated in regulatory approvals of melanocortin‑4 receptor (MC4R) agonists for selected monogenic disorders that present with severe early‑onset hyperphagia and obesity. These disorders include proopiomelanocortin (POMC) deficiency, prohormone convertase 1 (PCSK1) deficiency, leptin receptor (LEPR) deficiency, and Bardet‑Biedl syndrome (BBS).
The new European expert consensus (Clément et al., 2026) summarized here responds to urgent, practical challenges that accompany this scientific progress: very small patient numbers spread across countries; limited long‑term safety and effectiveness data for MC4R agonists; the need for equitable access to genetic diagnosis and treatment; and the responsibility to collect structured outcome data that will guide safe, effective, and ethical use of precision therapies.
Why this consensus matters now
– Therapies with disease‑modifying potential now exist for a handful of defined genetic obesity disorders. Prescribing these drugs without coordinated oversight risks inconsistent patient selection, missed safety signals, and inequitable access.
– Real‑world evidence (RWE) is sparse for long‑term outcomes, comorbidity effects, developmental and psychiatric sequelae, and pregnancy.
– National health systems and payers require transparent, evidence‑driven frameworks for identifying eligible patients, monitoring response, and discontinuing therapy when benefit is absent.
The consensus therefore prioritizes centralized expertise, standardized diagnostic and monitoring pathways, data registries, and multidisciplinary care.
New Guideline Highlights
Major recommendations and themes (high level)
– Designate regional or national centers of expertise for coordinated diagnosis, initiation, and follow‑up of patients with rare genetic obesity disorders.
– Ensure equitable access to timely genetic testing for children and adults with early‑onset hyperphagia and severe obesity or syndromic features suggestive of monogenic causes.
– Restrict initiation of MC4R agonist therapy (e.g., setmelanotide/Imcivree) to centers with multidisciplinary capability and experience in genetic obesity.
– Require structured, protocolized baseline assessment and longitudinal monitoring, with predefined criteria for treatment continuation or discontinuation.
– Mandate contribution to national or international real‑world registries to capture effectiveness, safety, developmental and psychosocial outcomes.
Key takeaways for clinicians
– Suspect a monogenic cause in severe early‑onset obesity with hyperphagia, developmental delay or syndromic features, or a strong family history.
– Refer promptly for genetic evaluation rather than empiric off‑label therapy.
– If MC4R agonist therapy is indicated, use centers of expertise to ensure appropriate dosing, monitoring, multidisciplinary support, and registry enrollment.
Updated Recommendations and Key Changes
What’s new compared with previous practice (or ad hoc care models)
– Formal recommendation to establish and designate centers of expertise across Europe to centralize rare obesity care.
– Explicit requirement that initiation and ongoing prescription of MC4R agonists occur within those centers (or in close shared‑care arrangements) rather than by scattered practitioners.
– Structured monitoring protocols specifying clinical, biochemical, developmental, and patient‑reported outcomes and intervals for evaluation.
– A governance framework for data sharing and real‑world evidence aggregation to support therapy optimization and safety surveillance.
Evidence driving these updates
– Regulatory approvals of MC4R agonists created clinical demand but highlighted knowledge gaps about long‑term outcomes.
– Small sample sizes in pivotal trials limit generalizability; pooled RWE from coordinated centers is the pragmatic path to build evidence.
– Experience from other rare disease networks (for example Endo‑ERN) demonstrates that centers of expertise improve diagnostic yield and patient outcomes while optimizing resource use.
Topic‑by‑Topic Recommendations
1) Case finding and diagnostic criteria
– Presentations that should prompt genetic evaluation:
– Severe obesity beginning in infancy or early childhood (typically before 5 years), especially with insatiable hunger (hyperphagia).
– Syndromic features (retinal dystrophy, polydactyly, genital anomalies, developmental delay) suggestive of Bardet‑Biedl syndrome.
– Family history consistent with autosomal recessive or dominant inheritance or consanguinity.
– Recommended testing: targeted gene panels for monogenic obesity including POMC, PCSK1, LEPR, MC4R pathway genes, and BBS genes; or clinical exome/genome sequencing where panels are negative and suspicion remains high.
– Recommendation strength: Strong expert consensus for testing in indicated phenotypes; conditional where phenotypes are atypical.
2) Referral and centers of expertise
– Centers should have multidisciplinary teams that include pediatric and/or adult endocrinology, clinical genetics, dietetics, behavioral/psychological support, nursing, pharmacy, and access to ophthalmology, nephrology, cardiology and reproductive medicine as needed.
– Centers should demonstrate experience with genetic diagnostics, consent for genomic testing, familiarity with MC4R agonist therapy, and capability to contribute to registries.
– Recommendation: National health authorities should identify and fund a network of centers to ensure geographic equity.
3) Treatment strategies: MC4R agonists and adjunctive care
– Indication for therapy: confirmed pathogenic or likely pathogenic variants in genes for which MC4R agonists are approved (per local regulatory labels) and the clinical phenotype is consistent (hyperphagia, severe early‑onset obesity).
– Treatment must be initiated in a center of expertise and include: individualized dosing per product label, education on expected benefits and adverse effects, baseline labs and anthropometrics, and psychosocial support.
– Adjunctive care: behavioral therapy, nutritional support, management of comorbidities (sleep apnea, type 2 diabetes, orthopedic complications), and developmental services in children.
– Recommendation strength: Strong for treating genotype‑confirmed, phenotype‑consistent patients; conditional for use in research protocols where genotype is uncertain.
4) Monitoring and outcomes
– Baseline evaluation (within 4 weeks prior to therapy): weight and BMI trajectory, validated hyperphagia/hunger scores, metabolic panel (lipids, glucose, liver tests), cardiac evaluation as indicated, mental health assessment, and quality‑of‑life measures.
– Follow‑up schedule (example): 1 month, 3 months, 6 months, then every 6–12 months thereafter, with more frequent checks early in therapy for adverse events and dose adjustment.
– Core outcomes to capture: weight/BMI change and trajectory, hyperphagia score change, metabolic markers, growth and pubertal progression in children, psychiatric symptoms, adverse events (cutaneous reactions, injection site issues, mood changes), and pregnancy outcomes if applicable.
– Prespecified stopping rules: lack of clinically meaningful benefit in weight trajectory or hyperphagia after a defined period (e.g., 6–12 months) should prompt discussion and supported discontinuation.
– Recommendation strength: Strong consensus to measure and re‑evaluate objectively and regularly; treatment should not continue indefinitely without benefit.
5) Pregnancy, fertility, and special populations
– Data are limited on MC4R agonist safety during pregnancy and lactation. Women of childbearing potential should receive counseling, effective contraception, and pregnancy testing per product guidance.
– If pregnancy is desired, centers should weigh risks and benefits, and coordination with obstetrics and maternal‑fetal medicine is essential.
– In older adults or individuals with complex comorbidities, individualized risk assessment is required.
6) Data capture, registries, and research
– All treated patients should be offered inclusion in national or international registries to capture long‑term safety and effectiveness, developmental outcomes, and health economic data.
– Centers should contribute standardized datasets to enable pooled analyses and generate higher‑quality RWE.
Recommendation Grades — Practical Summary
– Strong expert consensus (recommend):
– Genetic testing in phenotype‑concordant early‑onset severe obesity.
– Referral to centers of expertise for diagnosis and treatment initiation.
– Structured baseline and longitudinal monitoring with prespecified stopping criteria.
– Mandatory registry enrollment for treated patients where feasible.
– Conditional/Research (recommend with caution):
– Use of MC4R agonists off‑label or in genotype‑negative patients—only within research protocols or with careful multidisciplinary oversight.
Expert Commentary and Insights
Consensus committee perspectives
– The authors emphasize that the therapeutic era for monogenic obesity must be matched by systems of care that reduce variation, protect patient safety, and maximize learning. Centralizing care does not mean limiting access; rather, centers of expertise are envisioned as hubs that enable equitable outreach, telemedicine, and shared‑care models with local providers.
– Experts explicitly endorse transparent outcome measures and stopping rules to avoid indefinite therapy in nonresponders and to allow reallocation of scarce resources.
Key controversies and uncertainties
– Equity vs centralization: centralizing expertise can create travel burdens for families; shared‑care arrangements and telehealth can mitigate this but require funding.
– Off‑label prescribing: pressure from families seeking treatment can push clinicians toward off‑label use; the consensus discourages this outside research frameworks.
– Long‑term developmental, psychiatric, and reproductive effects of MC4R agonists remain unknown; the community must prioritize longitudinal follow‑up.
Future trends and research needs
– Harmonized, interoperable registries across countries to power meaningful long‑term analyses.
– Studies to define predictors of response (genotype‑phenotype correlations, modifier genes, early age at initiation).
– Workflows to reduce time to genetic diagnosis, including newborn or early childhood genomic screening pilots in high‑risk populations.
Practical Implications for Clinicians and Health Systems
– For front‑line clinicians: maintain a high index of suspicion for monogenic obesity in early‑onset severe cases with hyperphagia; expedite genetic referral rather than empiric treatment.
– For centers and health systems: identify and resource centers of expertise with multidisciplinary teams, build shared‑care pathways, and invest in registry participation and data governance.
– For payers and policymakers: adopt transparent coverage policies aligned with consensus recommendations that require genotypic confirmation, center involvement, and registry enrollment for funded therapy.
Patient vignette (illustrative)
Emma, an 8‑year‑old girl with insatiable hunger since infancy and rapidly increasing weight, had failed multiple behavioral interventions. Her pediatrician referred her to a regional center of expertise. Genetic testing identified biallelic POMC loss‑of‑function variants. After multidisciplinary counseling, Emma started an MC4R agonist at the center. Her hyperphagia score improved within weeks, BMI trajectory slowed over months, and she was enrolled in the national registry. At 12 months a formal review documented clinically meaningful benefit and no serious adverse events; therapy continued with ongoing monitoring.
References
– Clément K, Farooqi IS, Kühnen P, Wabitsch M, Cetiner M, Argente J, Grueters A. Precision Medicine in patients with rare forms of genetic obesity: Necessity for coordinated and structured care. J Clin Endocrinol Metab. 2026 Aug 14. PMID: 42598766. https://pubmed.ncbi.nlm.nih.gov/42598766/
– U.S. Food and Drug Administration. FDA approves first drug for chronic weight management in certain rare genetic disorders of obesity (press release and prescribing information for Imcivree/setmelanotide). Available at: https://www.fda.gov/news-events/press-announcements/fda-approves-first-drug-chronic-weight-management-certain-rare-genetic-disorders-obesity
– Farooqi IS, O’Rahilly S. Genetic syndromes of severe childhood obesity. Annu Rev Med. 2006;57: 277–298. (Seminal review on monogenic obesity biology and clinical features.)
– Endo‑ERN (European Reference Network on Rare Endocrine Conditions). Best practices for networks of expertise in rare endocrine disorders. https://endo-ern.eu/
Note: This article summarizes the 2026 European expert consensus and integrates established background references. Clinicians should consult original consensus text and local regulatory labels for detailed operational protocols and up‑to‑date indications.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.