The Gatekeeper of Diabetes Technology
For years, thousands of Americans living with insulin-requiring type 2 diabetes have hit a bureaucratic brick wall when seeking advanced treatment. This wall is often built on a single laboratory value: the C-peptide level. In the world of clinical endocrinology, C-peptide is a byproduct of insulin production. For the Centers for Medicare & Medicaid Services (CMS) and many private insurers, a low C-peptide level has long been the ‘golden ticket’ required to prove that a patient’s pancreas is failing enough to justify the cost of an insulin pump. If your C-peptide level is too high, you are often deemed ineligible for automated insulin delivery (AID) systems, under the assumption that your body still makes enough insulin to manage with traditional injections. However, a groundbreaking study published in Diabetes Care is now dismantling this assumption, proving that the benefit of technology is not dictated by a single blood test.
Meet Robert: A Case of Bureaucratic Limbo
To understand the impact of this research, consider Robert, a 68-year-old retired engineer from Ohio. Robert has lived with type 2 diabetes for 22 years. Despite a rigorous regimen of basal-bolus insulin therapy—requiring four to five injections a day and frequent finger pricks—his HbA1c remained stuck at 8.2%. He experienced frequent ‘rollercoaster’ blood sugar readings, with exhausting spikes after meals and frightening lows at night. Robert’s endocrinologist recommended an automated insulin delivery system, often called an ‘artificial pancreas.’ This technology uses a continuous glucose monitor (CGM) and a sophisticated algorithm to adjust insulin delivery automatically. But when the request reached his insurance provider, it was denied. The reason? Robert’s C-peptide level was 1.2 ng/mL. According to current CMS criteria, he produced too much of his own insulin to qualify for pump coverage. Robert was left in a clinical limbo: too ‘healthy’ on paper to receive the best technology, but too ‘sick’ in reality to achieve stable glucose levels.
The 2IQP Study: Challenging the Status Quo
The study, titled Adults With Type 2 Diabetes Benefit From Automated Insulin Delivery Irrespective of C-Peptide Level (the 2IQP study), led by Dr. Irl B. Hirsch and a team of expert researchers, sought to determine if these insurance restrictions are scientifically sound. The researchers evaluated the t:slim X2 insulin pump equipped with Control-IQ technology in a randomized trial. The study focused on adults with type 2 diabetes who were already using a basal-bolus insulin regimen (multiple daily injections). The participants were divided into two groups based on the CMS criteria: those with high C-peptide levels (n = 195) and those with low C-peptide levels (n = 59). Both groups were then randomized to either continue their current treatment or switch to the AID system.
Scientific and Clinical Evidence: What the Data Tell Us
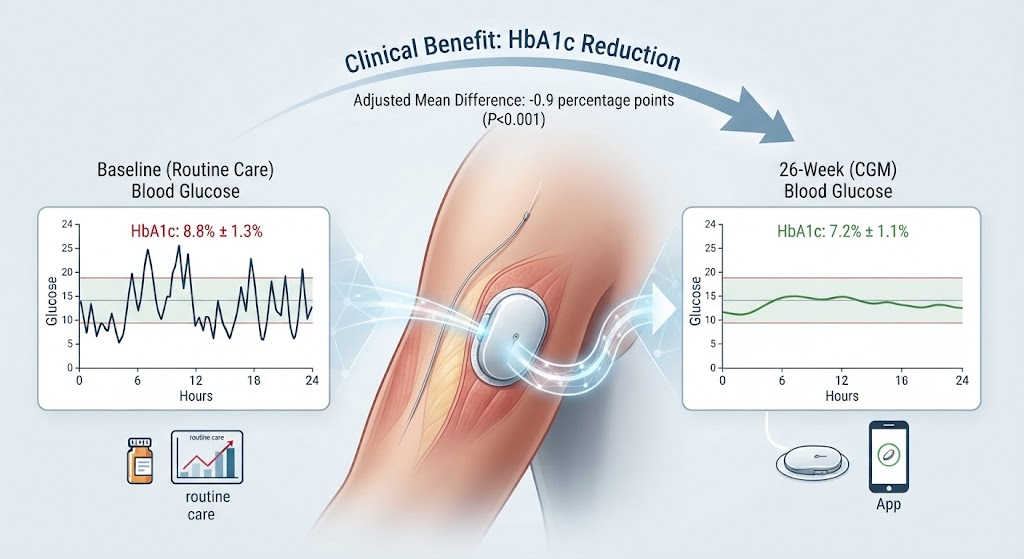
The results of the 2IQP study were strikingly clear. Both the high C-peptide group and the low C-peptide group saw significant improvements in their glycemic control when using the AID system. The primary metric, HbA1c (a three-month average of blood sugar), dropped by an average of 0.8% in the AID group compared to the control group. Crucially, this improvement occurred regardless of how much insulin the patient’s body was naturally producing.
Summary of HbA1c Reduction in the 2IQP Study
| Group Category | HbA1c Reduction (AID vs. Control) | Statistical Significance (P-value) |
|---|---|---|
| High C-Peptide Participants | 0.8% Improvement | P < 0.001 |
| Low C-Peptide Participants | 0.8% Improvement | P = 0.02 |
| Participants Age 65+ | Consistent Benefit | Significant across all ages |
The data demonstrate that the physiological ‘need’ for automated delivery isn’t just about the absence of endogenous insulin. Even patients who still produce some insulin (high C-peptide) struggle with insulin resistance and the complexity of dosing, which the AID algorithm manages more effectively than manual injections.
Misconceptions and the Myth of the ‘Sufficient’ Pancreas
A common misconception in diabetes management is that if a patient with type 2 diabetes still has beta-cell function (indicated by C-peptide), they should be able to manage their condition with simple injections. This view ignores the extreme insulin resistance often present in type 2 diabetes. For many, even though the pancreas is producing insulin, the body cannot use it effectively, leading to massive glucose fluctuations. The 2IQP study proves that AID technology is not just for those with ‘dead’ pancreases (like in type 1 diabetes). Instead, the technology acts as a powerful tool to overcome insulin resistance and the human error inherent in calculating dozens of doses every week. By automating the ‘basal’ or background insulin and providing corrective boluses, the system compensates for the unpredictable nature of type 2 diabetes in a way that manual injections simply cannot.
Expert Insights: Moving Beyond Outdated Policies
Dr. Irl Hirsch, the lead author and a prominent figure in diabetes research, has long argued that current coverage policies are based on outdated science from the early 2000s. In the study’s conclusion, the 2IQP group stated: ‘The benefit of AID is present with high and low C-peptide levels. Thus, requiring a low C-peptide level as a prerequisite for AID therapy is not warranted.’ Medical professionals emphasize that the goal of diabetes care is to prevent long-term complications such as kidney failure, blindness, and cardiovascular disease. If an 0.8% reduction in HbA1c can be achieved through technology, denying that technology based on a C-peptide threshold is essentially denying a safer, healthier future for the patient.
Practical Recommendations for Patients and Providers
For patients like Robert, this study provides the scientific ammunition needed to appeal insurance denials. Here are the practical takeaways for those navigating this landscape: 1. Focus on ‘Time in Range’: While HbA1c is the gold standard for insurance, patients should talk to their doctors about ‘Time in Range’ (TIR). AID systems are particularly good at increasing the hours per day spent in a healthy glucose zone (70–180 mg/dL). 2. Address Glycemic Variability: If you have high C-peptide but suffer from frequent ‘lows’ (hypoglycemia), this study supports the idea that AID can make your life safer. 3. Advocacy: Share this research with your clinical team. If a prior authorization is denied based on C-peptide, the 2IQP study can be cited in an appeal to demonstrate that the criteria are not evidence-based.
Conclusion: A Call for Policy Reform
The 2IQP study is a landmark moment for diabetes advocacy. It highlights a significant gap between clinical evidence and administrative policy. As the medical community moves toward more personalized medicine, the reliance on a single, arbitrary biomarker like C-peptide appears increasingly obsolete. For the millions of adults living with insulin-treated type 2 diabetes, the message is clear: the benefits of automated technology are universal. It is time for insurance policies to catch up with the science, ensuring that patients receive the tools they need based on their clinical outcomes rather than an outdated laboratory threshold.
Funding and Clinical Trials
This research was supported by the 2IQP Study Group. For further details on the clinical trial and its methodology, visit clinicaltrials.gov (Identifier: NCT04905862).
References
Hirsch IB, Kudva YC, Ahn DT, Blevins T, Rickels MR, Raghinaru D, Lum JW, Kollman C, Pinsker JE, Beck RW; 2IQP Study Group. Adults With Type 2 Diabetes Benefit From Automated Insulin Delivery Irrespective of C-Peptide Level. Diabetes Care. 2025 Dec 1;48(12):2061-2066. doi: 10.2337/dc25-1125. PMID: 40953318.