Highlight
- Bruton’s tyrosine kinase inhibitors (BTK-I) increase the risk of non-fatal ischemic major adverse cardiovascular events (MACE) in patients with B-cell malignancies.
- Among BTK inhibitors, ibrutinib predominates in clinical use and is associated with this cardiovascular risk.
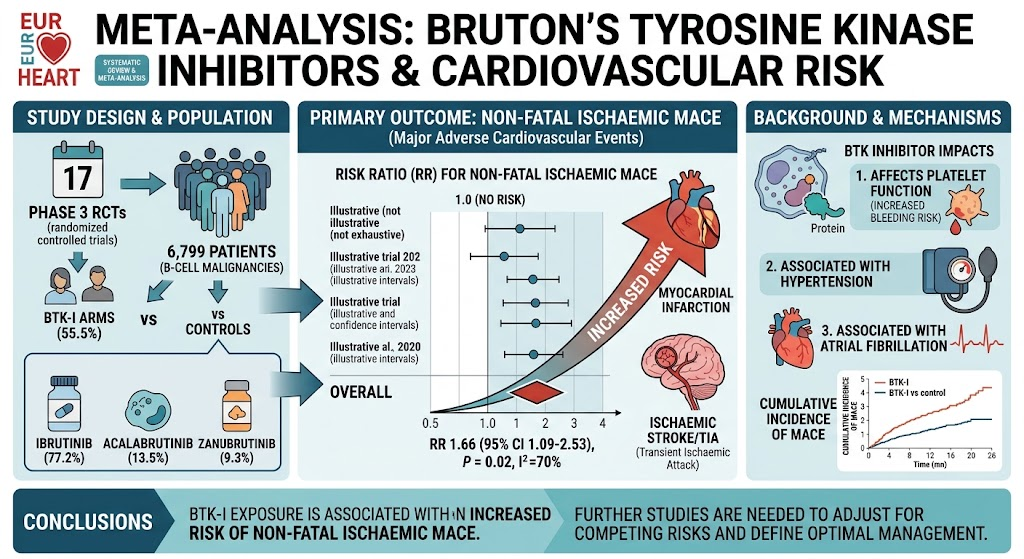
- The meta-analysis of 17 Phase 3 randomized controlled trials (RCTs) involving 6799 patients reveals a 66% increased relative risk of ischemic MACE compared to controls.
- Substantial heterogeneity exists among trials, highlighting variable cardiovascular risk profiles depending on patient populations, drug type, and trial design.
Study Background
Bruton’s tyrosine kinase inhibitors have revolutionized the treatment landscape for various B-cell malignancies, including chronic lymphocytic leukemia and mantle cell lymphoma. Despite their clinical efficacy, BTK inhibitors have been increasingly linked to cardiovascular toxicities. These include heightened bleeding risk due to platelet dysfunction, hypertension, and notably, atrial fibrillation. Emerging evidence further suggests that these agents may predispose patients to ischemic cardiovascular events, such as myocardial infarction and cerebrovascular ischemia, which constitute major adverse cardiovascular events (MACE). Because patients with hematologic cancers often have complex comorbidities, understanding the cardiovascular safety profile of BTK inhibitors is critical to optimizing care.
Study Design
This systematic review and meta-analysis targeted Phase 3 randomized controlled trials evaluating the cardiovascular risk of BTK inhibitors—specifically ibrutinib, acalabrutinib, and zanubrutinib—in adult patients diagnosed with B-cell malignancies. A comprehensive search was conducted across ClinicalTrials.gov, EudraCT, MEDLINE, and Cochrane CENTRAL databases up to December 19, 2024. The primary endpoint was the incidence of non-fatal ischemic MACE, a composite endpoint including myocardial ischemic syndromes (such as myocardial infarction and unstable angina) and ischemic stroke or transient ischemic attack. The meta-analysis utilized a random-effects Mantel-Haenszel model to generate pooled risk ratios (RR) with corresponding 95% confidence intervals (CI), accounting for inter-study heterogeneity (I2 statistic estimated using the DerSimonian-Laird method).
Key Findings
Seventeen Phase 3 RCTs encompassing a total of 6799 patients were included. The distribution of patients was 55.5% in the BTK inhibitor treatment arms and 44.5% in control arms (which likely included placebo or standard therapy). The majority of exposed patients (77.2%) received ibrutinib, followed by acalabrutinib (13.5%) and zanubrutinib (9.3%).
The meta-analysis demonstrated that BTK inhibitor therapy was associated with a statistically significant increased risk of non-fatal ischemic MACE, with a pooled risk ratio of 1.66 (95% CI, 1.09–2.53; P = .02). This indicates a 66% increase in risk relative to control patients. Notably, the analysis showed substantial heterogeneity (I2 = 70%), indicating variability in effect sizes across the trials.
This heterogeneity may result from differences in the study populations’ baseline cardiovascular risk, BTK inhibitors used, duration of follow-up, and variations in cardiovascular event ascertainment methods. While mainly ibrutinib dominates clinical use, the data on acalabrutinib and zanubrutinib remain limited but reassuring to some extent. However, the current dataset does not enable stratified risk assessments by individual agent or patient risk factors due to aggregate data limits and lack of patient-level covariate adjustment.
Expert Commentary
This meta-analysis adds to the growing awareness that BTK inhibitors bear cardiovascular risks beyond bleeding and arrhythmias, extending to ischemic major adverse cardiovascular events. The mechanisms are not fully elucidated but may involve direct vascular toxicity, prohypertensive effects, and disruption of platelet signaling pathways. The association with atrial fibrillation also compounds ischemic stroke risk.
Importantly, the reliance on adverse event reporting from RCTs restricts the ability to fully contextualize these risks within competing mortality risks or to adjust for other cardiovascular comorbidities. Real-world observational data and pharmacovigilance reports complement these findings but suffer from inherent biases and confounding. Prospective cardiovascular monitoring and mechanistic studies are warranted to better identify at-risk subgroups, discern class effects, and develop mitigation strategies.
Clinical guidelines currently emphasize monitoring for atrial fibrillation and bleeding in BTK inhibitor recipients. This meta-analysis underscores the necessity to expand cardiovascular vigilance to ischemic events as well. Clinicians should carefully weigh cardiovascular risk factors in patients considered for BTK inhibitor therapy and collaborate with cardio-oncology specialists as needed.
Conclusion
The evidence from this comprehensive meta-analysis suggests that BTK inhibitors increase the risk of non-fatal ischemic MACE by approximately 66% in patients treated for B-cell malignancies. While this elevates critical safety concerns, heterogeneity and data limitations indicate a nuanced cardiovascular risk profile. Clinicians must balance this increased ischemic risk with the substantial oncologic benefits of BTK inhibition. Future research should focus on individualized risk stratification, mechanistic understanding, and development of prophylactic strategies to minimize cardiovascular harm while preserving anticancer efficacy.
Funding and Registration
This meta-analysis was prospectively registered with PROSPERO (registration number CRD420251241020). The original publication does not disclose specific funding sources for this meta-analysis.
References
1. Alexandre J, Font J, Haddad S, et al. Bruton’s tyrosine kinase inhibitors and cardiovascular risk: a meta-analysis. European Heart Journal. 2026 Aug 8; PMID: 42568037.
2. Wang ML, Rule S, Martin P, et al. Targeting BTK with ibrutinib in relapsed chronic lymphocytic leukemia. NEJM. 2013;369(1):32-42.
3. Shanafelt TD, Wang XV, Kay NE. Ibrutinib and cardiovascular toxicity: incidence, risk factors, and management. Blood. 2020;135(12):1017-1027.
4. Caldeira D, Alves L, David C, Ferreira JJ, Pinto FJ. Risk of atrial fibrillation with ibrutinib: A systematic review and meta-analysis. Drug Saf. 2019;42(1):59-66.