Prognostic Impact of IPI Risk Factors on CAR T-Cell Therapy Versus Allogeneic Stem Cell Transplantation in Relapsed/Refractory Large B-Cell Lymphoma
Highlight
– The International Prognostic Index (IPI) remains a critical tool in stratifying relapse/refractory LBCL patients considering advanced therapies.
– CAR T-cell therapy demonstrated superior overall survival over alloSCT primarily due to reduced non-relapse mortality.
– Patients with low to low-intermediate IPI risk benefit most from CAR T-cell therapy, whereas high-risk patients do not show a survival advantage.
– Elevated LDH levels diminish progression-free survival (PFS) benefits of CAR T-cell therapy, underscoring the need for early alloSCT planning in select high-risk patients.
Study Background
Large B-cell lymphoma (LBCL) encompasses a heterogeneous group of aggressive lymphomas where prognosis and therapeutic outcomes widely vary according to disease biology and clinical characteristics. The International Prognostic Index (IPI), which incorporates age, performance status, lactate dehydrogenase (LDH) levels, extranodal involvement, and disease stage, remains pivotal in risk stratification. Relapsed or refractory LBCL presents a therapeutic challenge, especially beyond second-line treatment. Recent advances include chimeric antigen receptor T-cell (CAR T-cell) therapy and allogeneic stem cell transplantation (alloSCT). While CAR T-cell therapies have transformed management paradigms, alloSCT remains an important curative approach. Understanding how IPI risk factors influence outcomes after these interventions is vital for optimizing patient selection and sequencing of therapies.
Study Design
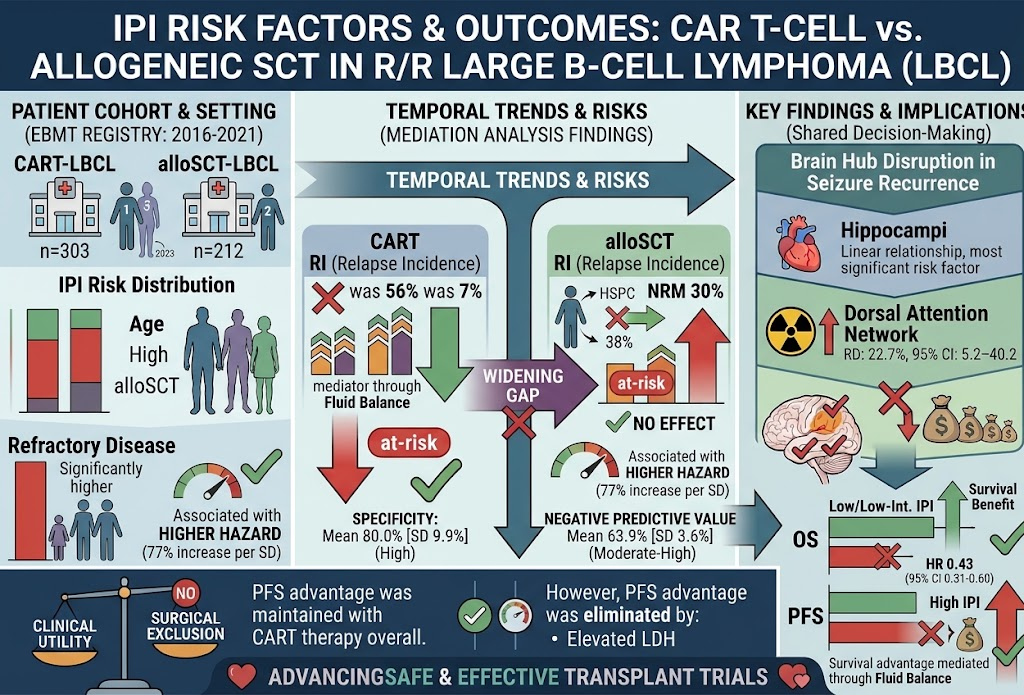
This retrospective multicenter analysis utilized the European Society for Blood and Marrow Transplantation (EBMT) registry data from 2016 to 2021, reviewing outcomes of 515 patients with relapsed or refractory LBCL who underwent third-line or later treatment with either CAR T-cell therapy (n=303) or alloSCT (n=212). Patient demographics, IPI risk classifications (low/low-intermediate vs. high/high-intermediate), refractory disease status, and survival outcomes were assessed. Endpoints included overall survival (OS), progression-free survival (PFS), relapse incidence (RI), and non-relapse mortality (NRM) at 24 months post-treatment. Multivariate analyses adjusted for confounders were conducted to evaluate the impact of IPI and other prognostic variables.
Key Findings
Baseline characteristics demonstrated that the CAR T-cell therapy cohort was older (median age 62.4 years versus 51.1 years for alloSCT), with a markedly higher proportion of patients carrying high or high-intermediate IPI risk scores (48.2% vs. 20.8%) and refractory disease (84.1% vs. 34.6%).
At 24 months, survival analyses revealed:
- Overall Survival: 49% in the CAR T-cell group versus 41% in the alloSCT group.
- Progression-Free Survival: 37% vs. 32%, respectively.
- Relapse Incidence: Higher in CAR T-cell recipients at 56% vs. 38% in alloSCT recipients.
- Non-Relapse Mortality: Significantly lower with CAR T-cell therapy (7%) compared to alloSCT (30%).
Multivariate modeling indicated that CAR T-cell therapy confers a survival advantage predominantly due to significantly reduced NRM, despite higher relapse rates. Subgroup analyses by IPI stratification showed a significant OS benefit in low and low-intermediate risk patients receiving CAR T-cell therapy (hazard ratio [HR] 0.43, 95% confidence interval [CI] 0.31–0.60). However, this benefit was not evident among patients categorized as high risk. Elevated LDH levels negated the PFS advantage observed with CAR T-cell therapy, underscoring its negative prognostic influence.
The study highlights that patients with high-risk features, particularly those with poor prognostic indices and elevated LDH, derive less benefit from CAR T-cell therapy. Given the high NRM associated with alloSCT, early identification and preparation for transplantation in suitable high-risk patients remains essential to potentially improve outcomes.
Expert Commentary
This comprehensive registry analysis provides valuable real-world insights into the prognostic impact of IPI factors on modern therapeutic modalities in relapsed/refractory LBCL. The findings align with emerging clinical experience where CAR T-cell therapy offers a favorable toxicity profile translating into improved OS in patients with lower disease burden and risk. The elevated relapse incidence following CAR T-cell therapy emphasizes the importance of vigilant post-treatment monitoring and integration of consolidative approaches.
For patients with high-risk disease characteristics and elevated LDH, the lack of a survival advantage with CAR T-cell therapy suggests alloSCT remains an indispensable component in curative strategies despite its higher NRM. Clinicians should consider early transplant referral and optimize supportive care to mitigate transplant-related risks.
Limitations include inherent registry biases and the retrospective design potentially influencing patient selection and outcome reporting. Prospective trials stratifying patients by molecular and clinical risk factors are warranted to refine individualized treatment pathways.
Conclusion
In relapsed or refractory LBCL, the International Prognostic Index retains critical relevance in guiding the choice between CAR T-cell therapy and allogeneic stem cell transplantation. CAR T-cell therapy demonstrates superior overall survival in low to low-intermediate risk patients, primarily attributed to lower non-relapse mortality. Conversely, patients with high IPI risk scores and elevated LDH show diminished benefits, supporting a strategy of early alloSCT consideration in this subgroup. Personalized risk-adapted approaches incorporating IPI stratification and biochemical markers are recommended to optimize outcomes. Further prospective studies are necessary to validate these findings and improve therapeutic sequencing.
Funding and Clinical Trials
The study was conducted using EBMT registry data without specific external funding reported. Clinical trials registered within the EBMT framework may provide ongoing data on CAR T-cell and alloSCT outcomes in LBCL.
References
Ossami Saidy A, Boumendil A, Dreger P, et al. The impact of IPI risk factors on CAR T-cell therapy or allogeneic stem cell transplantation for treatment of relapsed or refractory large B-cell lymphoma. Bone Marrow Transplant. 2026 Jun 19;61(8):1073-1082. PMID: 42321403.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.