Highlight
The PREOPANC-2 randomized phase 3 trial assessed overall survival outcomes comparing neoadjuvant FOLFIRINOX to neoadjuvant gemcitabine-based chemoradiotherapy, followed by surgery and adjuvant therapy, in patients with resectable or borderline resectable pancreatic ductal adenocarcinoma (PDAC). The study demonstrated no statistically significant difference in median overall survival between the two treatment approaches. Both regimens showed considerable but manageable toxicities, with differing safety profiles. These findings support the consideration of both neoadjuvant strategies as valid options in clinical practice.
Study Background
Pancreatic ductal adenocarcinoma (PDAC) remains a malignancy with poor prognosis, representing one of the leading causes of cancer-related mortality worldwide due to its aggressive biology and late presentation. Surgical resection offers the best chance for long-term survival, but even among resectable and borderline resectable cases, outcomes after upfront surgery remain suboptimal due to early systemic dissemination and high recurrence rates. Neoadjuvant therapy regimens aim to improve oncological outcomes by downstaging tumors, eradicating micrometastatic disease, and enabling better patient selection for surgery.
Previously, gemcitabine-based chemoradiotherapy was a widely accepted neoadjuvant treatment for PDAC, providing locoregional control. More recently, multi-agent chemotherapy regimens such as FOLFIRINOX (combining oxaliplatin, irinotecan, leucovorin, and fluorouracil) have demonstrated efficacy in metastatic and adjuvant settings and increasingly in neoadjuvant contexts. However, direct comparisons of these approaches in the neoadjuvant setting for resectable and borderline resectable PDAC were lacking.
Study Design
PREOPANC-2 was an investigator-initiated, multicenter, open-label, randomized phase 3 trial conducted in 19 Dutch centers. The trial enrolled adult patients (≥18 years) with either resectable or borderline resectable PDAC and a World Health Organization (WHO) performance status of 0 or 1. Patients were randomized 1:1 to two neoadjuvant strategies:
- FOLFIRINOX Arm (FFX): Eight cycles of neoadjuvant FOLFIRINOX administered biweekly, including intravenous oxaliplatin (85 mg/m2), irinotecan (180 mg/m2), leucovorin (400 mg/m2), bolus fluorouracil (400 mg/m2), and continuous infusion fluorouracil (2400 mg/m2 over 46 hours), followed by surgery without adjuvant therapy.
- Chemoradiotherapy Arm (CRT): Three cycles of neoadjuvant gemcitabine (1000 mg/m2 administered intravenously on specific days per cycle), combined with hypofractionated radiotherapy (36 Gy in 15 fractions delivered during the second cycle), followed by surgery and then four cycles of adjuvant gemcitabine.
Randomization was stratified by resectability status and participating center. The primary endpoint was overall survival in the modified intention-to-treat population after excluding ineligible patients. Secondary endpoints included safety and treatment-related adverse events.
Key Findings
Between June 2018 and January 2021, 375 patients were randomized: 188 to the FOLFIRINOX group and 187 to the chemoradiotherapy group. After exclusion of six patients due to ineligibility or withdrawal, 369 patients were analyzed (56% male). The median follow-up was 42.3 months. Key outcomes included:
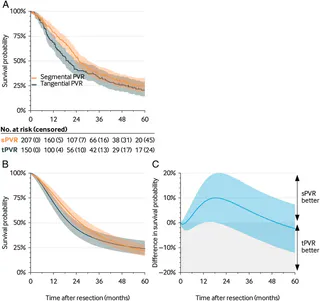
- Overall Survival: Median overall survival was 21.9 months (95% CI: 17.7–27.0) in the FOLFIRINOX group versus 21.3 months (95% CI: 16.8–25.5) in the chemoradiotherapy group. The hazard ratio (HR) was 0.88 (95% CI: 0.69–1.13; p=0.32), indicating no statistically significant difference.
- Toxicity: Grade 3–4 adverse events were frequent in both groups. Notably, neutropenia occurred in 25% (FFX) vs. 22% (CRT), diarrhoea was more common with FOLFIRINOX (23% vs. 1%), and leukopenia was more frequent in the CRT arm (8% vs. 15%). Serious adverse events were comparable (49% vs. 43%), and treatment-related deaths were rare but occurred in both groups.
The safety profiles reflect the known toxicities of the regimens, with gastrointestinal toxicity more prominent in FOLFIRINOX and hematologic toxicities apparent in both arms.
Expert Commentary
The PREOPANC-2 trial is a rigorously conducted comparative effectiveness study providing valuable data on the neoadjuvant management of resectable and borderline resectable pancreatic cancer. The absence of a significant survival difference underscores that both regimens remain reasonable options, enabling clinicians to tailor treatment based on patient fitness, toxicity profiles, and institutional experience.
The substantial toxicity observed with FOLFIRINOX, particularly diarrhoea, necessitates careful patient selection and supportive care measures. On the other hand, the addition of radiotherapy in the gemcitabine-based approach confers locoregional treatment which might benefit certain tumor biology or anatomical subgroups, though this trial did not identify survival superiority.
Limitations include the lack of racial and ethnic data, which may affect broader generalizability, and the open-label design, which is common in chemotherapy trials but may influence reporting of subjective adverse events.
Conclusion
In patients with resectable or borderline resectable PDAC, neoadjuvant FOLFIRINOX does not improve overall survival compared to neoadjuvant gemcitabine-based chemoradiotherapy followed by adjuvant gemcitabine. Both approaches are associated with significant but manageable toxicity. These findings support the use of either neoadjuvant strategy within multidisciplinary treatment planning to optimize outcomes.
Future work is needed to identify biomarkers predictive of response and to refine patient selection criteria, potentially improving personalized therapeutic strategies in this challenging disease.
Funding and Trial Registration
This trial was funded by the Dutch Cancer Society and ZonMw. It is registered on EudraCT under number 2017-002036-17.
References
Janssen QP, van Dam JL, van Bekkum ML, et al. Neoadjuvant FOLFIRINOX versus neoadjuvant gemcitabine-based chemoradiotherapy in resectable and borderline resectable pancreatic cancer (PREOPANC-2): a multicentre, open-label, phase 3 randomised trial. Lancet Oncol. 2025 Oct;26(10):1346-1356. doi: 10.1016/S1470-2045(25)00363-8. Epub 2025 Sep 10. PMID: 40945523.