Neighborhood Disadvantage and Mortality Risk After Major Hepatectomy: Insights from the Area Deprivation Index
Highlight
- Higher area deprivation index (ADI), reflecting greater neighborhood socioeconomic disadvantage, is associated with increased 90-day mortality after major hepatectomy.
- Posthepatectomy liver failure accounts for most deaths within 90 days post-surgery.
- No significant association was found between ADI and serious postoperative morbidity, indicating mortality risk is uniquely influenced by socioeconomic factors.
- Hepaticojejunostomy and cholangiocarcinoma are independently associated with postoperative morbidity after major hepatectomy.
Study Background
Major hepatectomy—surgical removal of a significant portion of the liver—is a complex procedure commonly performed for malignant liver tumors, including metastases and cholangiocarcinoma. Despite advances in surgical techniques and perioperative care, morbidity and mortality remain significant concerns. Identifying patients at elevated risk for adverse outcomes facilitates targeted preoperative optimization and improved postoperative management.
Increasingly, the role of social determinants of health in surgical outcomes has gained recognition. The area deprivation index (ADI) quantifies neighborhood-level socioeconomic disadvantage by integrating variables such as income, education, employment, and housing quality. Prior studies have correlated higher ADI with poorer outcomes after various major surgeries. However, these have often involved mixed surgical populations, with limited data specific to hepatobiliary procedures such as major hepatectomy.
This study addresses this gap by examining whether increasing ADI correlates with serious postoperative morbidity and 90-day mortality after major hepatectomy within a single health system over nearly a decade. The findings carry implications for risk stratification and perioperative planning among socially disadvantaged populations.
Study Design
A retrospective cohort study analyzed adult patients who underwent major hepatectomy between 2014 and 2023 at a single integrated health system. Major hepatectomy was defined by surgical resection extent, including right hepatectomy.
Neighborhood disadvantage was assigned based on patients’ residential addresses, stratified into tertiles by ADI: lower (0–49), middle (50–69), and upper (70–100), with higher values indicating greater socioeconomic deprivation.
Primary outcomes included serious postoperative morbidity and mortality within 90 days. Postoperative complications were classified, focusing on events of clinical significance, including posthepatectomy liver failure.
Statistical analyses employed Firth’s penalized logistic regression modeling to adjust for confounders and identify independent associations between ADI tier and outcomes. Additional variables analyzed included surgical factors such as presence of hepaticojejunostomy and diagnosis of cholangiocarcinoma.
Key Findings
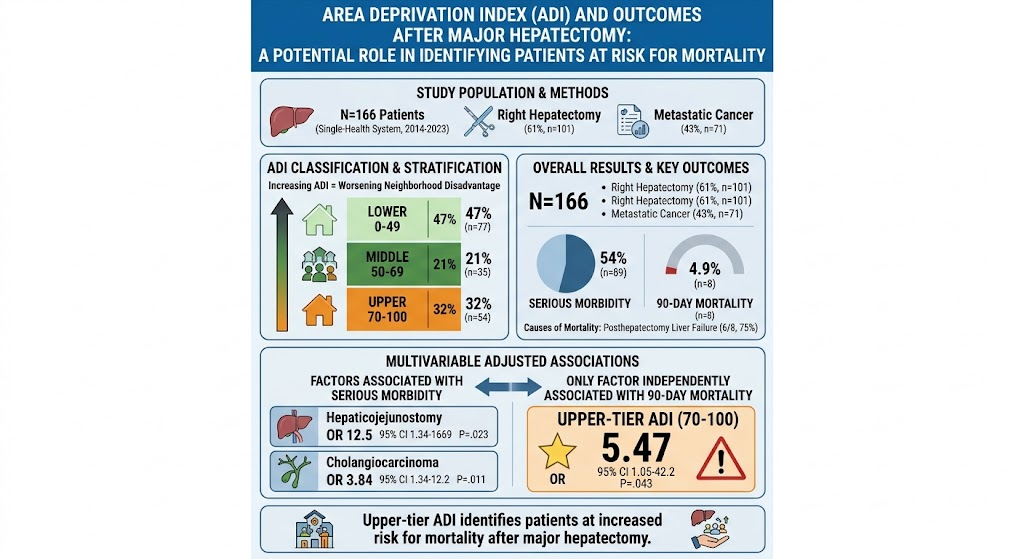
The cohort included 166 patients. Right hepatectomy constituted the majority (61%), with metastatic cancer as the most common indication (43%). Distribution across ADI tiers was 47% in lower, 21% middle, and 32% upper tiers.
Serious morbidity occurred in 54% (89/166) of patients, with hepaticojejunostomy (adjusted odds ratio [OR] 12.5; 95% confidence interval [CI], 1.34–1669; P = .023) and diagnosis of cholangiocarcinoma (OR 3.84; 95% CI, 1.34–12.2; P = .011) independently associated with morbidity. Notably, ADI tier did not significantly associate with morbidity.
In contrast, 90-day mortality occurred in 4.9% (8/166) of patients, with 75% of deaths attributable to posthepatectomy liver failure. The upper ADI tier independently predicted higher mortality risk (OR 5.47; 95% CI, 1.05–42.2; P = .043), suggesting that neighborhood disadvantage is a significant risk factor for mortality after major liver surgery.
These findings emphasize that while clinical variables influence postoperative complications, social determinants measured by ADI independently identify patients at risk of fatal outcomes.
Expert Commentary
The association between social deprivation and postoperative mortality underscores the complex interplay between biological vulnerability and social context. Higher ADI may reflect limited access to healthcare resources, suboptimal nutritional status, or challenges in adhering to postoperative care plans, all of which could exacerbate risks after major surgery.
The finding that ADI was not linked to morbidity but only mortality raises hypotheses: while complications may occur similarly across socioeconomic strata, disadvantaged patients may have reduced physiological reserve or less robust support systems, leading to increased mortality from critical events such as liver failure.
From a mechanistic perspective, posthepatectomy liver failure remains a major cause of death despite surgical advances. Disadvantaged patients may present later or with more advanced disease, have comorbidities, or face delays in intervention, compounding risk.
Limitations include the single-center retrospective design, which may affect generalizability. The modest sample size and wide confidence intervals, particularly for mortality associations, warrant cautious interpretation. Further multicentric prospective studies should validate these findings and elucidate modifiable factors within ADI components.
Clinically, integrating ADI into preoperative risk assessment could guide intensified monitoring, resource allocation, and tailored interventions—such as nutritional optimization, social work involvement, and closer postoperative surveillance—to improve outcomes in high-risk populations.
Conclusion
This study demonstrates that increased neighborhood socioeconomic disadvantage, as measured by a high area deprivation index, independently predicts 90-day mortality after major hepatectomy but does not affect serious morbidity rates. Most deaths result from posthepatectomy liver failure, highlighting the need for enhanced preoperative preparation and postoperative support for patients from socioeconomically deprived areas.
The findings advocate for inclusion of social determinants of health in surgical risk stratification models and postoperative care pathways. Addressing disparities related to neighborhood deprivation holds promise for improving liver surgery outcomes and reducing mortality among vulnerable populations.
Funding and ClinicalTrials.gov
The study was conducted within a single health system; specific funding sources were not reported. No clinical trial registration applies as this was a retrospective observational study.
References
1. Patel DJ, Nunez A, Hickson K, et al. Area deprivation index and outcomes after major hepatectomy: A potential role in identifying patients at risk for mortality. Surgery. 2026;199:110525. doi:10.1016/j.surg.2026.110525
2. Kind AJH, Buckingham WR. Making Neighborhood-Disadvantage Metrics Accessible — The Neighborhood Atlas. N Engl J Med. 2018;378(26):2456-2458. doi:10.1056/NEJMp1802313
3. Rahbari NN, Garden OJ, Padbury R, et al. Posthepatectomy liver failure: a definition and grading by the International Study Group of Liver Surgery (ISGLS). Surgery. 2011;149(5):713-724. doi:10.1016/j.surg.2010.11.012
4. Dimick JB, Chen SL, Taheri PA, et al. Hospital costs associated with surgical complications: a report from the private-sector National Surgical Quality Improvement Program. J Am Coll Surg. 2004 Oct;199(4):531-537. doi: 10.1016/j.jamcollsurg.2004.05.276
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.