Highlight
This multicenter phase II clinical trial reports a high 95% complete response rate in patients with newly diagnosed diffuse large B-cell lymphoma (DLBCL) treated with a combined regimen of glofitamab plus polatuzumab-R-CHP. The study demonstrates durable progression-free survival at 24 months (95%), confirms a favorable safety profile with only mild cytokine release syndrome (CRS) and no neurotoxicity, and supports further clinical evaluation of this novel immunochemotherapy approach.
Study Background
Diffuse large B-cell lymphoma (DLBCL) represents the most common aggressive subtype of non-Hodgkin lymphoma, characterized by heterogeneous biology and clinical outcomes. Standard treatment with R-CHOP (rituximab, cyclophosphamide, doxorubicin, vincristine, prednisone) achieves cure in many patients; however, patients with elevated International Prognostic Index (IPI) scores (≥ 2) or high-risk features often exhibit suboptimal responses, relapse, or refractory disease. Recent advancements have aimed to improve frontline outcomes by incorporating targeted and immune therapies into chemotherapy backbones.
Glofitamab is a bispecific CD3xCD20 T-cell engager antibody that redirects cytotoxic T cells to CD20-expressing B cells, showing promising single-agent activity in relapsed/refractory B-cell lymphomas. Polatuzumab vedotin, an antibody-drug conjugate targeting CD79b on B cells, combined with rituximab and chemotherapy (R-CHP), has demonstrated efficacy in DLBCL. Combining these agents with frontline chemotherapy could potentially enhance depth and durability of response via complementary mechanisms.
Study Design
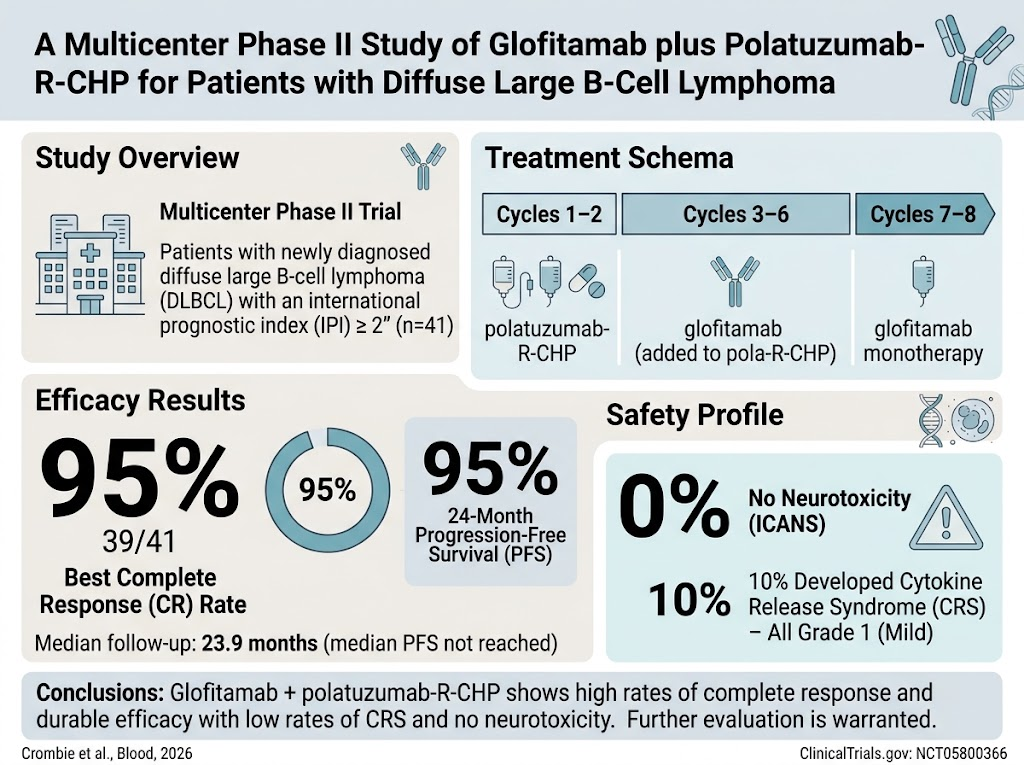
This phase II open-label, multicenter trial enrolled 41 patients with newly diagnosed DLBCL and intermediate to high-risk disease (IPI ≥ 2). The median age was 61 years, with a predominance of advanced stage (III/IV) disease and 12% harboring high-grade B-cell lymphoma with double-hit or triple-hit cytogenetics (MYC and BCL2 and/or BCL6 rearrangements).
Patients received frontline chemotherapy with polatuzumab, rituximab, cyclophosphamide, doxorubicin, and prednisone (pola-R-CHP) administered for two cycles initially. The bispecific antibody glofitamab was introduced starting from cycle 3 through cycle 6, followed by glofitamab monotherapy in cycles 7 and 8. A cycle of R-CHOP was permitted before initiating pola-R-CHP. The primary endpoint was best complete response (CR) rate assessed by imaging, while secondary endpoints included progression-free survival (PFS) and safety assessments.
Key Findings
The study observed an outstanding best CR rate of 95% (39/41 patients), with a 95% confidence interval of 83% to 99%. Notably, both patients who only achieved partial response at end-of-therapy assessments subsequently converted to CR without additional intervention. This suggests the regimen’s potent ability to induce deep and durable remission.
At a median follow-up of 23.9 months, median PFS has not been reached, with estimated 24-month PFS of 95% (95% CI: 89–100%), indicating sustained disease control in this high-risk population.
The safety profile was favorable, with only 10% (4 patients) experiencing cytokine release syndrome (CRS), all graded as mild (grade 1), and no incidents of immune effector cell-associated neurotoxicity syndrome (ICANS). This low toxicity may be attributed to the delayed and gradual incorporation of glofitamab into the treatment regimen, allowing mitigation of immune-related adverse effects.
Overall, the combination of glofitamab with polatuzumab-R-CHP displayed a remarkable balance of efficacy and tolerability, outperforming expected outcomes with standard R-CHOP, particularly in patients with high-risk clinical and molecular features.
Expert Commentary
The integration of bispecific antibodies into frontline therapy for DLBCL represents a paradigm shift toward harnessing immunotherapy earlier in treatment to improve long-term outcomes. Glofitamab’s dual engagement of T cells and CD20-positive lymphoma cells induces effective cytotoxicity, and polatuzumab-R-CHP adds apoptotic targeting of malignant B cells. The synergy observed here exemplifies the potential of combining novel immunotherapeutics with optimized chemoimmunotherapy backbones.
However, limitations include the single-arm design without a randomized control group, relatively small sample size, and short follow-up compared to long-term standards needed in lymphoma trials. The high CR and PFS rates are promising but warrant confirmation in larger randomized phase III studies. In addition, impact on overall survival, quality of life, and cost-effectiveness remain to be elucidated.
Mechanistically, the schedule with initial pola-R-CHP chemotherapy cycles followed by introduction of glofitamab appears to reduce immune-related adverse events while maintaining anti-lymphoma efficacy. This strategy could serve as a model for integrating other bispecific T-cell engaging antibodies in lymphoma treatment.
Conclusion
This phase II study provides compelling evidence that the combination of glofitamab with polatuzumab-R-CHP leads to high complete remission rates and durable response in newly diagnosed DLBCL patients with intermediate to high-risk features. The regimen’s excellent safety profile and low rates of CRS and neurotoxicity highlight its clinical appeal. These results justify further exploration in confirmatory randomized clinical trials to potentially establish a new frontline standard of care that integrates immunotherapy earlier in DLBCL management.
Funding and ClinicalTrials.gov Identifier
The study was conducted under the clinical trial registration number NCT05800366. Specific funding sources are not detailed in the abstract but would typically involve academic and industry partnerships supporting multicenter lymphoma research.
References
1. Crombie JL, Redd R, Phinney C, et al. A multicenter phase II study of glofitamab plus polatuzumab-R-CHP for patients with diffuse large B-cell lymphoma. Blood. 2026 Oct 6; PMID: 42837325.
2. Sehn LH, Herrera AF, Flowers CR, et al. Polatuzumab vedotin plus bendamustine and rituximab in relapsed/refractory DLBCL: a phase 2 trial. Blood. 2020;136(2):169-179.
3. Hutchings M, Morschhauser F, Iacoboni G, et al. Glofitamab, a CD20xCD3 bispecific antibody, in relapsed or refractory B-cell lymphoma: a phase 1 study. J Clin Oncol. 2021;39(23): 2462-2473.