Highlight
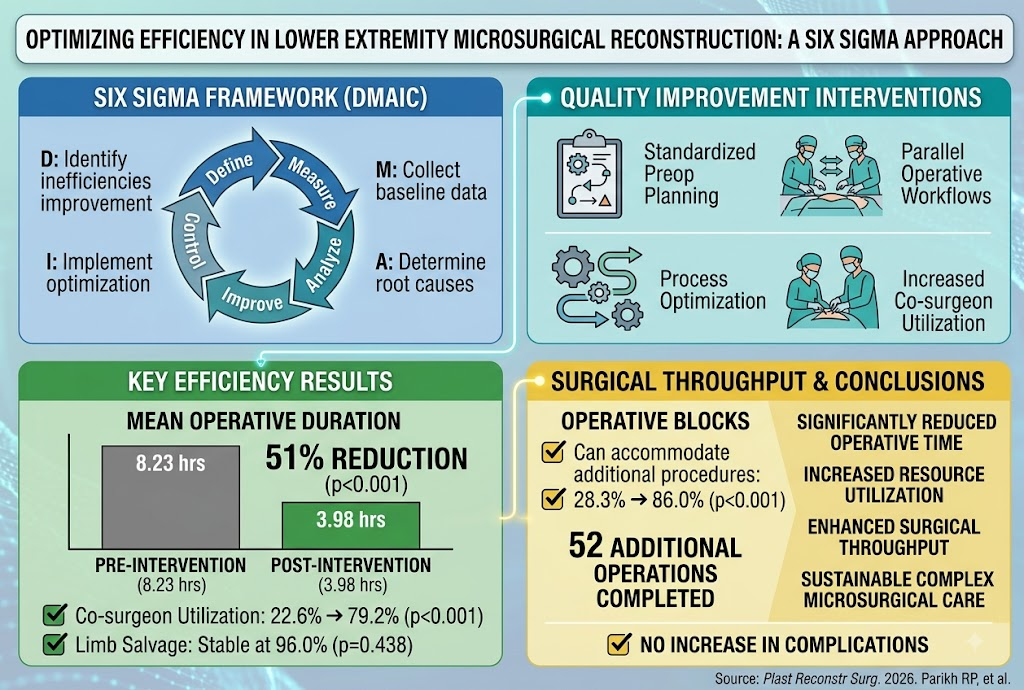
- Implementation of a Six Sigma DMAIC framework significantly reduced operative time from 8.23 to 3.98 hours in lower extremity microsurgical reconstruction.
- Increased co-surgeon utilization and standardized workflows improved operative throughput, enabling completion of 52 additional procedures without extending operative block times.
- Limb salvage rates remained stable, demonstrating efficiency gains did not compromise clinical outcomes.
Background
Lower extremity microsurgical reconstruction presents unique clinical challenges due to the complexity of procedures required to restore functional tissue after trauma, infection, or oncologic defects. These operations demand extensive resources and surgical expertise, often resulting in prolonged operative times and extended hospital stays. In the context of declining reimbursement and the added strain on healthcare systems exacerbated by the COVID-19 pandemic, optimizing efficiency without compromising outcomes is imperative to maintain the viability of these high-stakes procedures.
Microsurgical breast reconstruction has seen advances in operative efficiency through standardized protocols and parallel workflows; however, analogous data and quality improvement efforts tailored to lower extremity reconstruction remain limited. This study sought to address this gap by evaluating the impact of a structured quality improvement (QI) initiative based on Six Sigma methodologies applied to lower extremity microsurgical reconstruction.
Study Design
This was a single-center quality improvement study conducted between July 2021 and May 2023. The initiative employed the Six Sigma DMAIC (Define, Measure, Analyze, Improve, Control) framework to systematically identify inefficiencies and implement process optimizations. Key interventions included:
– Standardized preoperative planning protocols to streamline surgical preparation.
– Parallel operative workflows enhancing intraoperative coordination.
– Increased utilization of co-surgeons to facilitate concurrent surgical steps.
– Process optimization targeting resource allocation and operative block scheduling.
Following a three-month implementation phase, outcomes were assessed retrospectively comparing a post-intervention cohort (October 2021–May 2023, n=50 free flaps) with an 18-month pre-intervention cohort (n=53 free flaps). The primary endpoint was total operative duration. Secondary outcomes encompassed limb salvage rates as a measure of clinical efficacy and operative throughput evaluated by the ability to perform additional procedures within the same surgical block.
Multivariable regression models adjusted for case complexity and other operative characteristics ensured robust comparisons.
Key Findings
The QI initiative resulted in a statistically and clinically significant reduction in operative time, with mean duration decreasing from 8.23 ± 2.29 hours pre-intervention to 3.98 ± 1.77 hours post-intervention (p<0.001). Notably, the utilization of co-surgeons increased markedly from 22.6% to 79.2% (p<0.001), reflecting the adoption of parallel workflows and shared responsibilities.
Importantly, limb salvage rates were maintained at high levels, with 96.0% pre-intervention compared to 90.6% post-intervention (p=0.438), indicating no compromise in surgical quality or patient outcomes.
Enhanced operative throughput was demonstrated by a rise in the proportion of operative blocks accommodating additional procedures—from 28.3% before to 86.0% after the QI efforts (p<0.001). This efficiency enabled 52 extra operations to be completed within the same block time post-intervention, optimizing resource utilization and patient access.
Expert Commentary
This study exemplifies the potential for structured industrial methodologies such as Six Sigma to drive meaningful improvements in complex surgical care. By engaging multidisciplinary stakeholders and rigorously analyzing workflow inefficiencies, the team achieved substantial reductions in operative times and improved throughput without sacrificing clinical efficacy.
The increase in co-surgeon engagement likely played a pivotal role in parallelizing surgical tasks and expediting stages such as flap harvest and recipient site preparation. However, the study limitations include its single-center design and potential learning curve effects associated with the QI implementation phase.
Generalizability to other institutions will depend on local resources, multidisciplinary team availability, and administrative support for such systemic changes. Longer-term follow-up regarding functional outcomes and cost-effectiveness analysis would further strengthen the evidence base.
Conclusion
The application of Six Sigma DMAIC principles to lower extremity microsurgical reconstruction significantly optimizes operative efficiency by reducing surgical duration and increasing throughput while maintaining excellent limb salvage rates. This approach offers a promising framework for sustaining complex reconstructive services amid financial and operational pressures intensified by recent healthcare challenges.
Institutions performing microsurgical reconstruction should consider adopting structured QI programs emphasizing standardized planning, workflow parallelization, and collaborative surgical models to enhance care delivery and resource utilization.
Funding and Clinical Trials
The study was conducted at a single center without reported external funding. No clinical trial registration was referenced.
References
1. Parikh RP, Chung SW, Galvano E, Tom L, Kleiber G. Optimizing Efficiency in Lower Extremity Microsurgical Reconstruction Using Six Sigma: From Procedure to Process. Plast Reconstr Surg. 2026 Aug 7. PMID: 42566660.
2. Mehta N, et al. Improving operative efficiency in breast microsurgery: application of quality improvement principles. Plast Reconstr Surg Glob Open. 2020;8(6):e2882.
3. Levy E, et al. Parallel work flows and co-surgeon utilization in free flap reconstruction: a systematic review. J Reconstr Microsurg. 2022;38(4):261-269.
4. Institute for Healthcare Improvement. The Science of Improvement: How to Improve. http://www.ihi.org/resources/Pages/HowtoImprove/ScienceofImprovementHowtoImprove.aspx
5. Six Sigma Academy. DMAIC process. https://www.sixsigmaacademy.com/dmaic-cycle/