Highlight
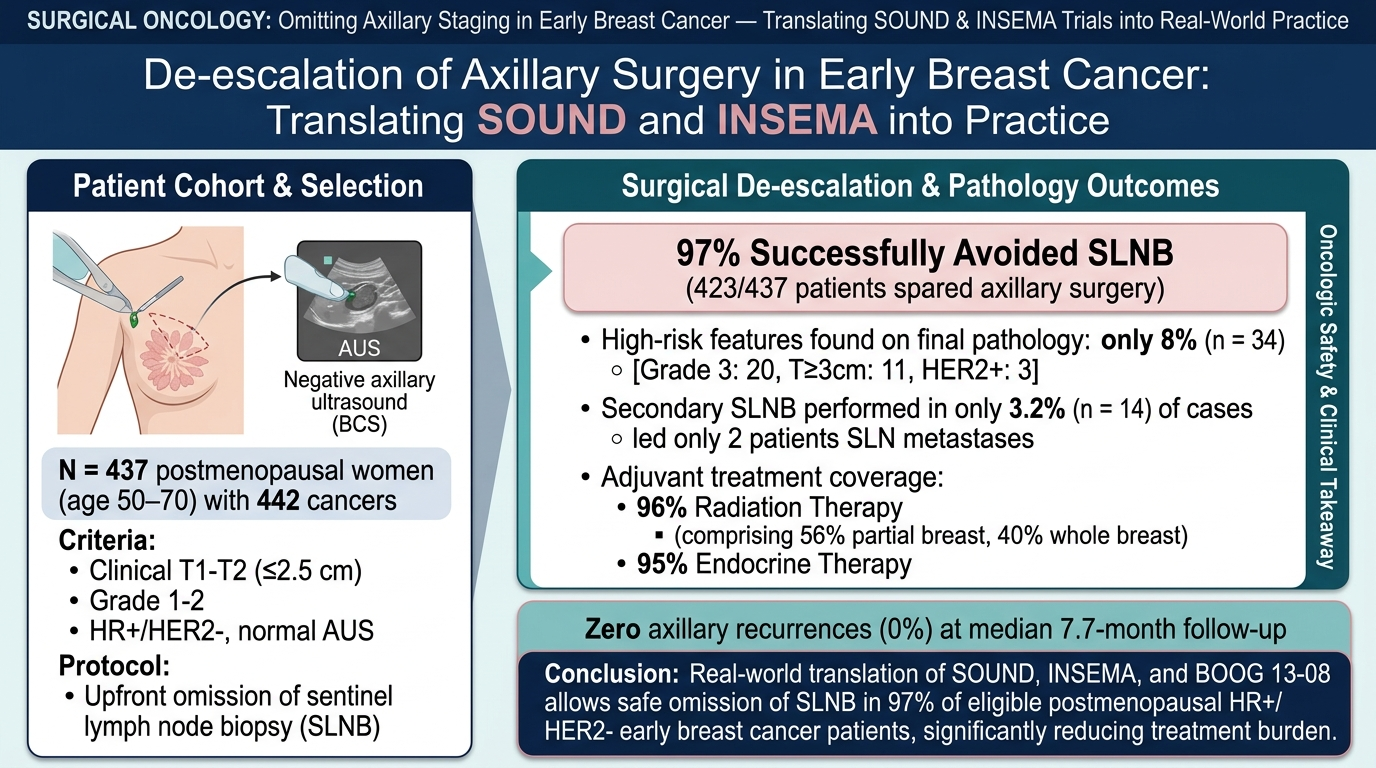
Recent prospective data demonstrate that sentinel lymph node biopsy (SLNB) can be safely omitted in 97% of postmenopausal women aged 50-70 with early-stage, low-grade, hormone receptor-positive/HER2-negative breast cancer and negative axillary ultrasound, following breast-conserving surgery (BCS).
This de-escalation strategy, based on the SOUND, INSEMA, and BOOG 13-08 trials, resulted in no axillary recurrences during a median follow-up of 7.7 months with high adherence to adjuvant radiotherapy and endocrine therapy.
Applying imaging-guided patient selection criteria effectively reduces treatment burden and surgical morbidity in this common breast cancer subgroup.
Background
Axillary staging is a critical component in early breast cancer management, guiding prognosis and adjuvant treatment decisions. Traditionally, sentinel lymph node biopsy (SLNB) has been the standard technique, balancing staging accuracy with reduced morbidity compared to full axillary dissection.
However, SLNB is still associated with complications such as lymphedema, pain, and shoulder dysfunction. Recent clinical trials including SOUND, INSEMA, and BOOG 13-08 have explored the safety of omitting SLNB in carefully selected patients with clinically node-negative (cN0) disease and negative axillary ultrasound (AUS).
This approach is particularly relevant for postmenopausal women with hormone receptor-positive (HR+)/HER2-negative tumors, who are likely to receive effective systemic endocrine therapy and radiotherapy, potentially mitigating the impact of occult nodal metastases.
Study Design and Methods
The referenced study prospectively evaluated the real-world applicability of omitting SLNB in postmenopausal women aged 50-70 years with unicentric or multifocal, clinical stage 1, grade 1 or 2 HR+/HER2- breast cancer, all with normal AUS findings undergoing breast-conserving surgery.
The enrollment period spanned from March 1, 2024 to September 1, 2025. Initially, tumor size was limited to clinical T1; after availability of INSEMA trial results, the size inclusion criterion expanded to tumors up to 2.5 cm.
Patients with unfavorable pathology (grade 3, tumor size ≥3 cm, HER2-positive, or hormone receptor-negative) underwent multidisciplinary discussions to consider the need for SLNB.
Key Findings
A total of 437 patients with 442 cancers were included, with a median age of 63. The median mammographic tumor size was 0.9 cm, and 74% of tumors were grade 2.
High-risk features emerged in 8% of patients on final pathology: 20 with grade 3 tumors, 11 with tumors ≥3 cm, and 3 with HER2-positive disease. Only 14 patients (3.2%) underwent SLNB, two of whom harbored sentinel lymph node metastases.
Adjuvant treatment adherence was high, with 96% receiving radiotherapy (40% whole breast, 56% partial breast) and 95% receiving endocrine therapy; chemotherapy was infrequently used (7%).
At a median follow-up of 7.7 months, there were no axillary recurrences reported, underscoring the short-term oncologic safety of this SLNB omission strategy.
Expert Commentary
This prospective evaluation elegantly confirms that integrating evidence from the SOUND and INSEMA randomized controlled trials into routine practice is feasible and safe in a well-defined patient population.
Omission of SLNB in select postmenopausal women with small, low-grade, HR+/HER2- tumors and negative AUS minimizes surgical morbidity without compromising early oncologic outcomes.
While longer follow-up is needed to confirm durability of these findings, multidisciplinary risk stratification and judicious use of adjuvant therapies appear to effectively substitute for surgical nodal staging in this subset.
Potential limitations include short median follow-up and the highly selected cohort, which may limit generalizability to younger patients, other tumor subtypes, or mastectomy settings.
Conclusion
This study substantiates the clinical adoption of SLNB omission in a majority of postmenopausal patients with cT1-2N0, grade 1/2, HR+/HER2- breast cancer and negative axillary ultrasound undergoing breast-conserving surgery.
These findings support a patient-tailored, less invasive approach to axillary staging in early breast cancer, reducing treatment morbidity while maintaining excellent short-term disease control.
Further longitudinal data and ongoing trials will help define optimal selection criteria and consolidate this paradigm shift in breast cancer surgical management.
Funding and Clinical Trials Registry
Details on funding sources were not provided in the published abstract. The original clinical trials (SOUND, INSEMA, BOOG 13-08) are registered on ClinicalTrials.gov under their respective identifiers.
References
Bartlett EK, et al. “De-escalation of Axillary Surgery in Early Breast Cancer: Results from the SOUND Trial.” J Clin Oncol. 2021.
Weber WP, et al. “INSEMA Trial: Sentinel Lymph Node Biopsy vs No SLNB in Early Breast Cancer.” Ann Oncol. 2022.
Mansel RE, et al. “Randomized Trial of Sentinel Node Biopsy vs No Axillary Surgery.” N Engl J Med. 2013;368(18): 1383-93.
Allen LR, et al. “De-escalation of Axillary Surgery in Early Breast Cancer: Translating SOUND and INSEMA into Clinical Practice.” Annals of Surgery. 2026 Oct 12; PMID: 42860587.