Highlight
- Robotic pancreatoduodenectomy (RPD) and open pancreatoduodenectomy (OPD) have comparable total hospital costs within 6 months postoperatively.
- RPD incurs significantly higher intraoperative costs but trends toward lower postoperative costs.
- Quality-adjusted life years (QALYs) showed a nonsignificant reduction with RPD at 6 months, leading to a less than 30% probability that RPD is cost-effective compared to OPD within this period.
Study Background
Pancreatoduodenectomy, or the Whipple procedure, is a complex surgery primarily indicated for resectable neoplasms of the pancreatic head and periampullary region. Traditional open pancreatoduodenectomy (OPD) has been the standard; however, minimally invasive approaches such as robotic pancreatoduodenectomy (RPD) have emerged aiming to improve postoperative recovery and reduce morbidity. Despite technological advances, concerns persist regarding higher costs associated with robotic systems, which may limit their broader clinical adoption. Formal cost-effectiveness assessments incorporating both economic and patient-centered outcomes, such as quality-adjusted life years (QALYs), are crucial to guide surgical choice and policy decisions.
Study Design
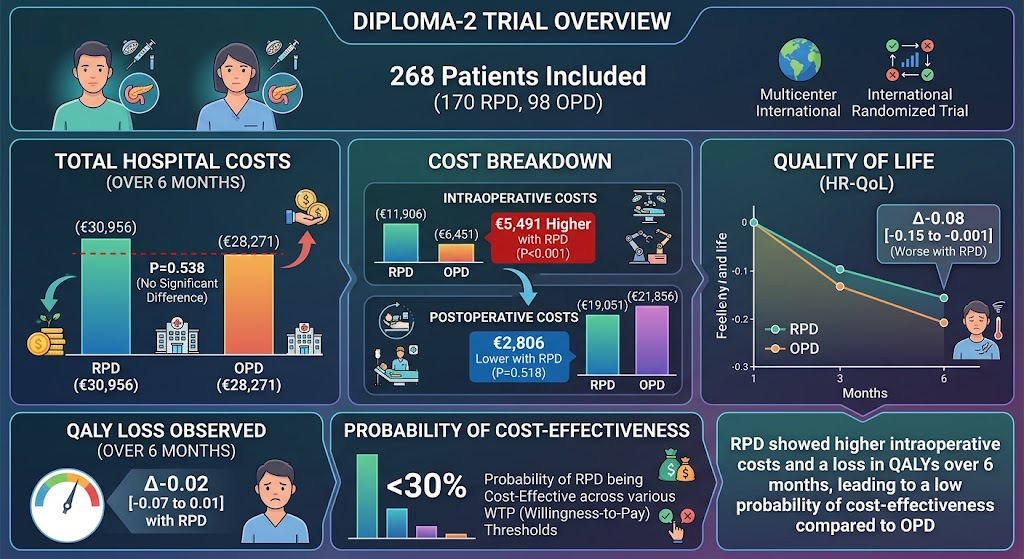
The DIPLOMA-2 trial is an international, multicenter randomized controlled trial (ISRCTN27483786) conducted across 14 high-volume centers in 6 European countries between 2022 and 2023. The trial enrolled 268 patients with primary resectable neoplasms eligible for pancreatoduodenectomy and randomized them in a 170:98 ratio to undergo either RPD or OPD. The primary analysis focused on total hospital costs (expressed in euros) measured up to 6 months after surgery and cost-effectiveness evaluated through incremental cost-utility ratios based on quality-adjusted life years (QALYs) derived from health-related quality of life (HR-QoL) metrics. Costs were categorized as intraoperative and postoperative for detailed assessment. Multiple cost-effectiveness thresholds reflecting willingness-to-pay (WTP) for each QALY gained were applied.
Key Findings
Costs: Total mean hospital costs at 6 months were €30,956 for RPD and €28,271 for OPD, with no statistically significant difference (P=0.538). However, intraoperative costs were significantly higher with RPD by approximately €5,491 (€11,906 vs. €6,451; P<0.001), likely reflecting equipment use, longer operative times, and associated consumables. Conversely, postoperative costs trended lower with RPD by €2,806 (€19,051 vs. €21,856) but this difference was not statistically significant (P=0.518).
Health-Related Quality of Life and QALYs: HR-QoL index scores were similar between groups at 1 and 3 months postoperatively but RPD patients reported worse scores at 6 months (mean difference -0.08; 95% CI -0.15 to -0.001). This resulted in a minor QALY loss over 6 months in the RPD arm relative to OPD (difference -0.02; 95% CI -0.07 to 0.01), which was not statistically significant.
Cost-effectiveness Probability: The combination of nonsignificant higher costs and slight reductions in QALYs yielded less than a 30% probability that RPD is cost-effective compared to OPD across various willingness-to-pay thresholds within the 6-month postoperative window in selected patients treated in high-volume centers.
Expert Commentary
The DIPLOMA-2 trial provides high-quality evidence in a critical area where data has been sparse: economic comparisons of robotic and open pancreatoduodenectomy. The finding that total costs are broadly comparable counters the assumption that robotic surgery necessarily entails greater expenditure. The significantly elevated intraoperative costs associated with robotics reflect the expenses of specialized equipment and longer operative times, but these may be partially offset by fewer complications or shorter hospital stays postoperatively, albeit not to a statistically significant degree in this study.
Interestingly, the slight decrement in quality of life observed at 6 months among RPD patients warrants further scrutiny, especially as robotic surgery is often marketed for enhanced recovery. Hypotheses to explain this observation may include learning curve effects, patient selection bias, or unmeasured complications that impact longer-term quality of life. Additional research with longer follow-up and detailed subgroup analyses could clarify these aspects.
Limitations include the relatively short follow-up period of 6 months which might be insufficient to capture all quality of life and cost benefits from minimally invasive approaches, particularly those related to longer-term oncologic outcomes or functional recovery. Moreover, generalizability may be constrained to high-volume, expert centers with established robotic programs and may not apply to less experienced settings.
Conclusion
The DIPLOMA-2 randomized trial’s cost-effectiveness analysis suggests that robot-assisted pancreatoduodenectomy does not confer significant cost advantages or improved quality-adjusted life years compared to the open approach within 6 months postoperatively. Although RPD incurs higher intraoperative costs, these are balanced by trends toward reduced postoperative expenses. Yet, the slight decrease in quality of life observed with RPD results in a low probability of cost-effectiveness at commonly accepted willingness-to-pay thresholds in this timeframe. Thus, the routine adoption of RPD should be carefully considered, weighing clinical benefits against economic implications, especially outside specialized centers.
Future directions include extended follow-up for long-term outcomes, incorporation of broader patient-reported outcomes, and cost analyses considering learning curve effects and institutional factors to refine surgical decision-making and health policy related to pancreatic cancer surgery.
Funding and Trial Registration
The DIPLOMA-2 trial was conducted by the European Consortium on Minimally Invasive Pancreatic Surgery (E-MIPS) with funding sources not specified in the abstract. The trial is registered with ISRCTN (ISRCTN27483786).
References
- Menso JE, Bruna CL, Nine G, et al. Cost-effectiveness Analysis of Robotic Versus Open Pancreatoduodenectomy (DIPLOMA-2): A Multicenter International Randomized Trial. Ann Surg. 2026 Aug 14. PMID: 42606345.
- van Hilst J, de Rooij T, Klompmaker S, et al. Minimally invasive versus open pancreatoduodenectomy: A systematic review and meta-analysis. Ann Surg. 2019;269(1):45-54.
- Besselink MG, van Rijssen LB, van Santvoort HC, et al. Technological developments and the impact on outcomes in pancreatic surgery. Ann Gastroenterol Surg. 2020;4(1):15-22.